[Pneumonia in clinical practice: diagnosis and therapy]
Related Experiment Video
Updated: Oct 9, 2026
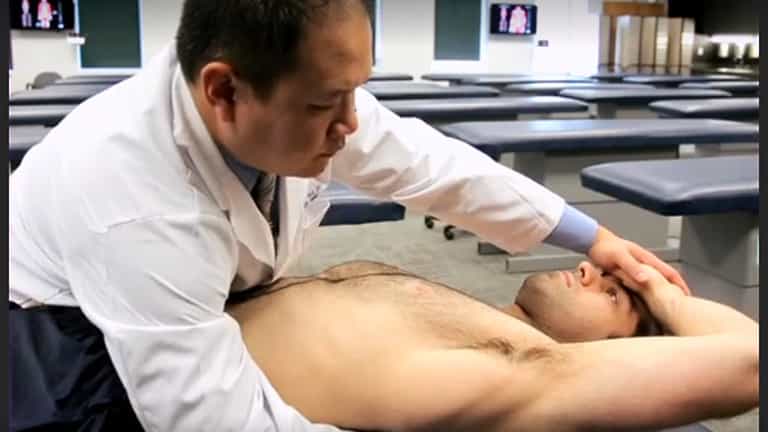
Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
1Departement für Innere Medizin, Universitätskliniken, Kantonsspital Basel.

Abstract:
Outpatients with pneumonia are usually treated empirically. Therefore, the knowledge of the most important causative agents is a prerequisite for the 'educated guess'. With a broad microbiological evaluation, the etiology of a pneumonia can be detected in only half of the cases. In outpatients, 30% of the causative agents are viruses, 45% 'atypical bacteria' such as Mycoplasma sp. and Chlamydia pneumoniae, and 25% pneumococci and Hemophilus. In hospitalized patients, pneumococci and Hemophilus cause 60%, and 'atypical bacteria' only 25% of the community acquired pneumonias. The most relevant microbiological examination in outpatients is the Gram stain of the sputum. The sputum culture is seldom useful and sometimes even misleading, especially if the result is not interpreted in connection with the Gram stain. The most appropriate treatment of outpatients without underlying disease is a macrolide. In patients with chronic bronchitis, alcoholism or preceding influenza infection, amoxicillin/clavulanic acid or a new oral cephalosporin is the best choice. The detection of risk factors for fatal outcome is important for the decision to admit the patient to a hospital.
Insights
Empirical treatment of pneumonia requires knowing common causes. For outpatients, viruses and atypical bacteria are frequent, while hospitalized patients more often have pneumococci and Hemophilus.
Area of Science:
- Infectious Diseases
- Microbiology
- Pulmonology
Context:
- Community-acquired pneumonia (CAP) management relies on empirical treatment due to diagnostic challenges.
- Understanding the specific microbial etiology of pneumonia in outpatients versus hospitalized patients is crucial for effective therapy.
Purpose:
- To delineate the common causative agents of pneumonia in outpatient settings and compare them to hospitalized patients.
- To evaluate the utility of microbiological diagnostic methods, specifically sputum Gram stain and culture, in identifying pneumonia pathogens.
- To provide evidence-based treatment recommendations for outpatients with pneumonia based on likely etiologies and risk factors.
Summary:
- In outpatients, pneumonia is caused by viruses (30%), atypical bacteria (45%), and typical bacteria (25%). Hospitalized patients show a higher prevalence of typical bacteria (60%).
- Sputum Gram stain is the most valuable microbiological test for outpatients; sputum culture is often unreliable.
- Recommended outpatient treatment includes macrolides for healthy individuals and amoxicillin/clavulanic acid or cephalosporins for those with risk factors.
Impact:
- Informed empirical treatment strategies for community-acquired pneumonia.
- Improved diagnostic approaches by highlighting the role of sputum Gram stain.
- Optimized antibiotic selection, potentially reducing resistance and improving patient outcomes.
Related Concept Videos
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 01:30
Pneumonia III: Complications and Assessment
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:29
Pneumonia I: Introduction