Related Experiment Video
Updated: Aug 27, 2026

Pressure Controlled Ventilation to Induce Acute Lung Injury in Mice
Published on: May 5, 2011
Adenosine A1-receptor mechanisms antagonize beta-adrenergic pulmonary vasodilation in hypoxia
R C McIntyre1, A Banerjee, D D Bensard
1Department of Surgery, University of Colorado Health Sciences Center, Denver 80262.

Abstract:
Hypoxic pulmonary vasoconstriction is refractory to beta-adrenergic receptor (beta-AR)-mediated pulmonary vasodilation. We hypothesized that hypoxic pulmonary arteries release adenosine (Ado) that antagonizes beta-AR-mediated pulmonary vasodilation. Using isolated rat pulmonary artery rings, we investigated 1) the effect of hypoxia and exogenous Ado on beta-AR-mediated pulmonary vasodilation, 2) the intracellular site of dysfunctional beta-AR-mediated pulmonary vasodilation in hypoxia, and 3) the Ado receptor subtype responsible for dysfunction of beta-AR-mediated pulmonary vasodilation. Hypoxia attenuated normal beta-AR-mediated pulmonary vasodilation to isoproterenol (97.5 +/- 0.8 vs. 71.5 +/- 2.3%, P < 0.01). In contrast, forskolin induced the same vasorelaxation in hypoxic pulmonary rings as controls (P = 0.09). Incubation of normoxic rings with Ado attenuated the vasorelaxation response induced by beta-AR stimulation (71.5 +/- 5.9%, P < 0.01), similar to the effect observed in hypoxia. Both nonspecific Ado receptor blockade (8-sulfophenyl-theophylline) and specific A1-receptor blockade (8-cyclopentyl-1,3-dimethylxanthine) restored the vasorelaxation response of hypoxic rings induced by beta-AR stimulation (93.3 +/- 2.3 and 92.2 +/- 2.8%, P < 0.01). The effects of hypoxia and Ado were reproduced by a specific A1 agonist (2-chloro-N6-cyclopentyladenosine), demonstrating impaired vasorelaxation induced by beta-AR stimulation in normoxia (70.6 +/- 4.5%, P < 0.01). From these data, we conclude that hypoxia antagonizes beta-AR-mediated pulmonary vasodilation via an Ado A1-receptor mechanism.

Related Concept Videos
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
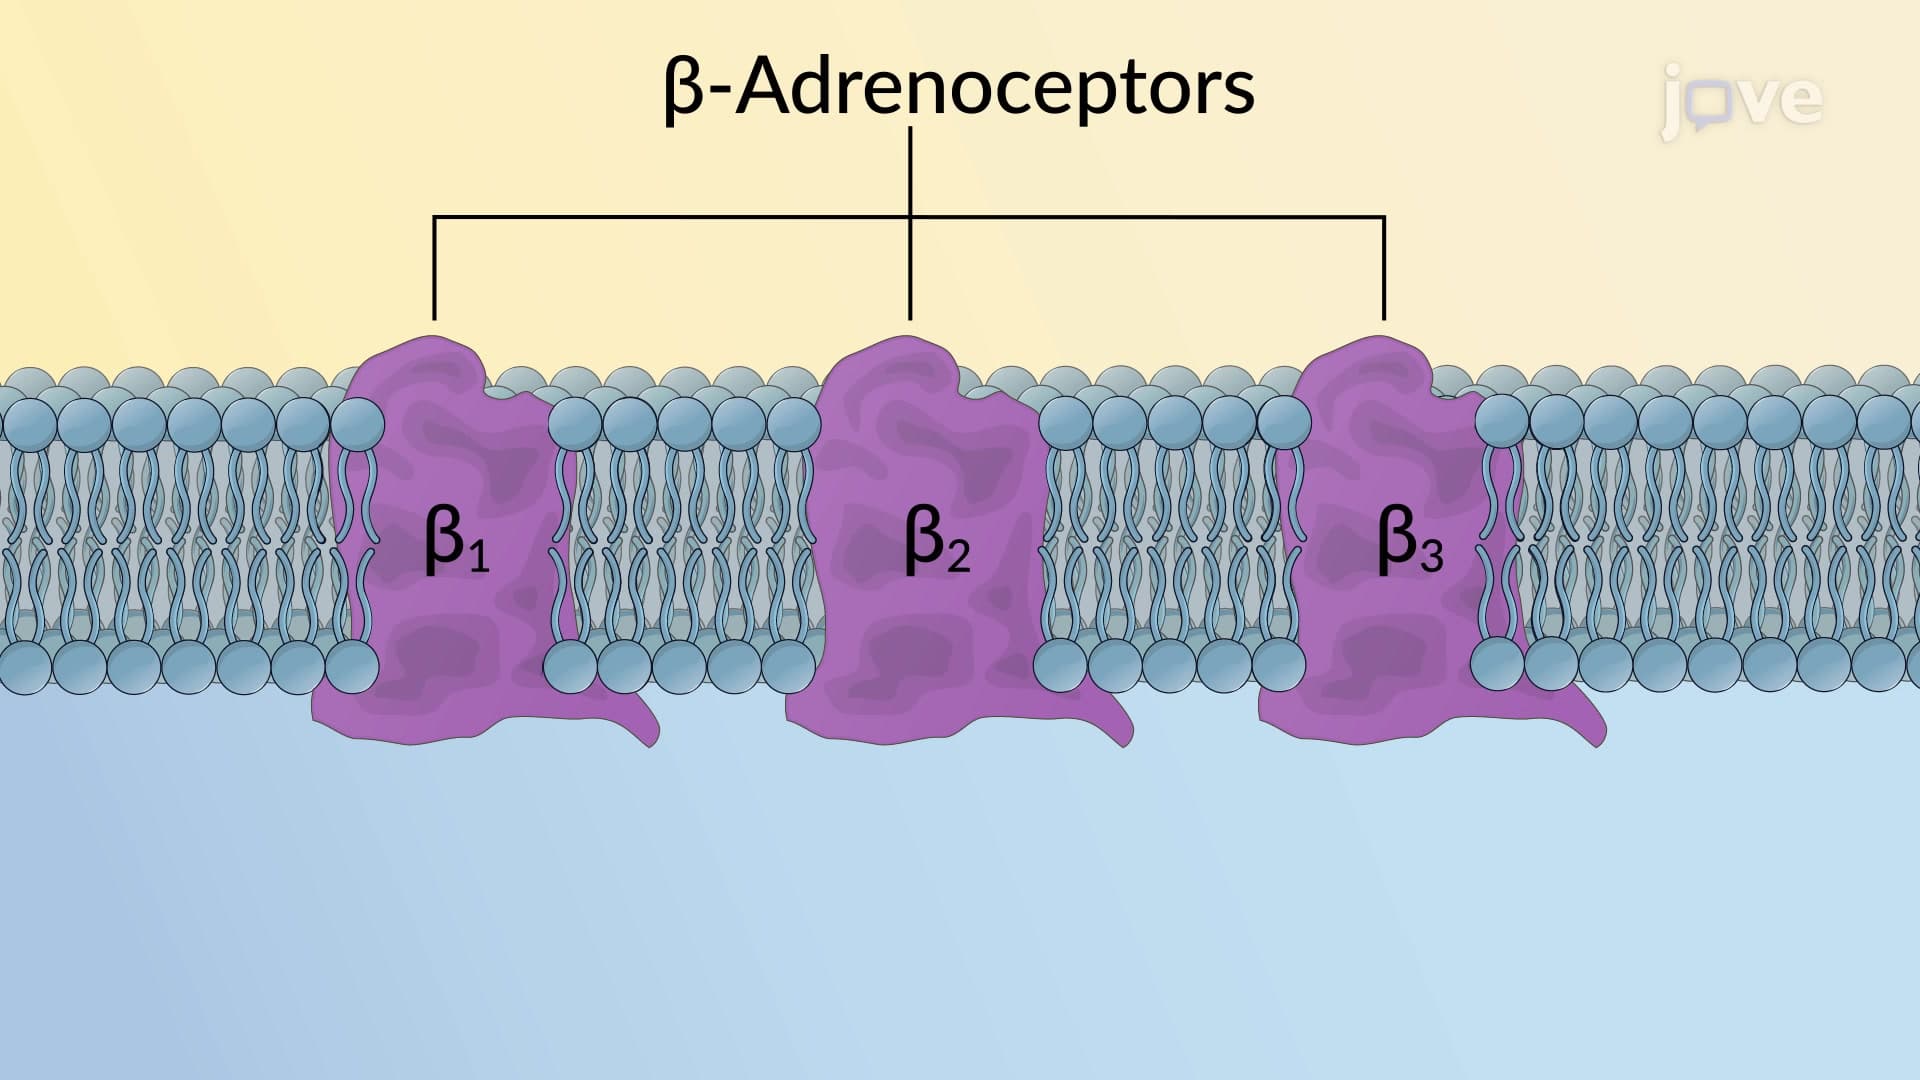
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
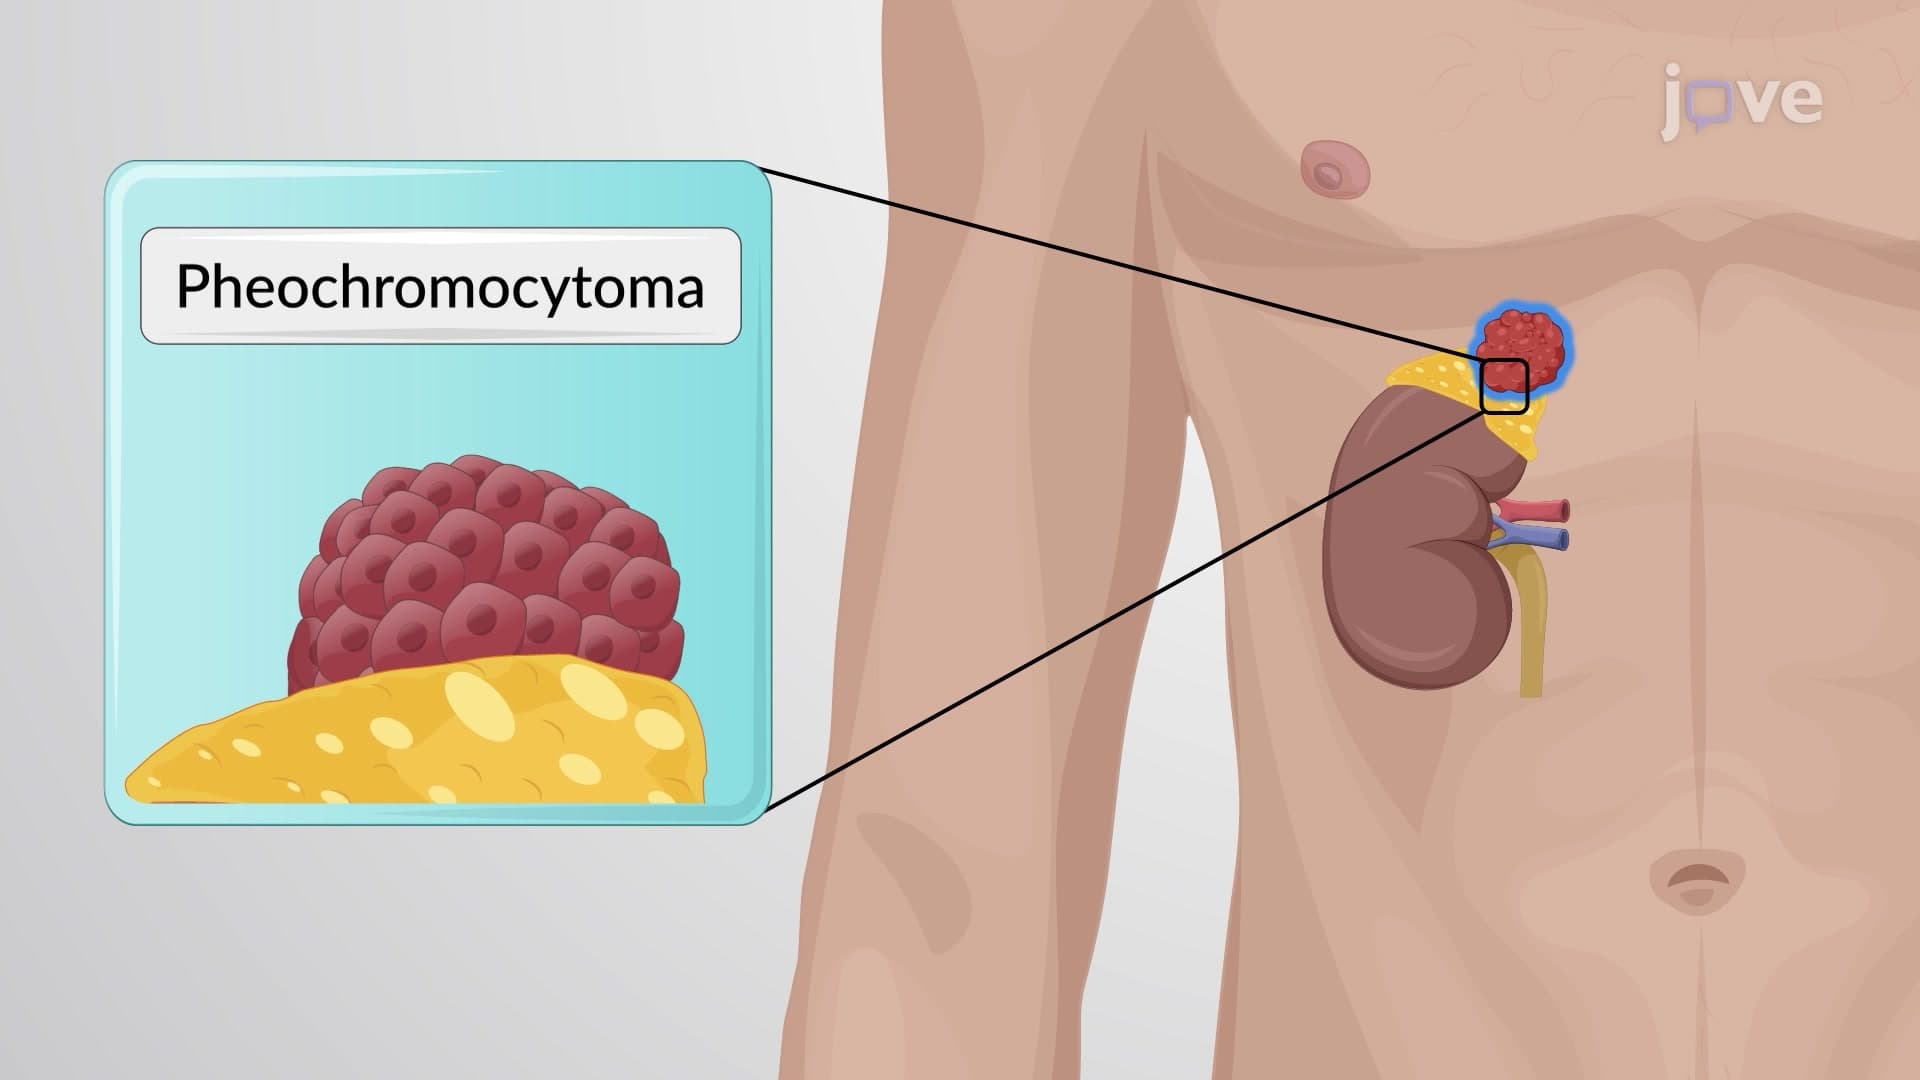 01:22
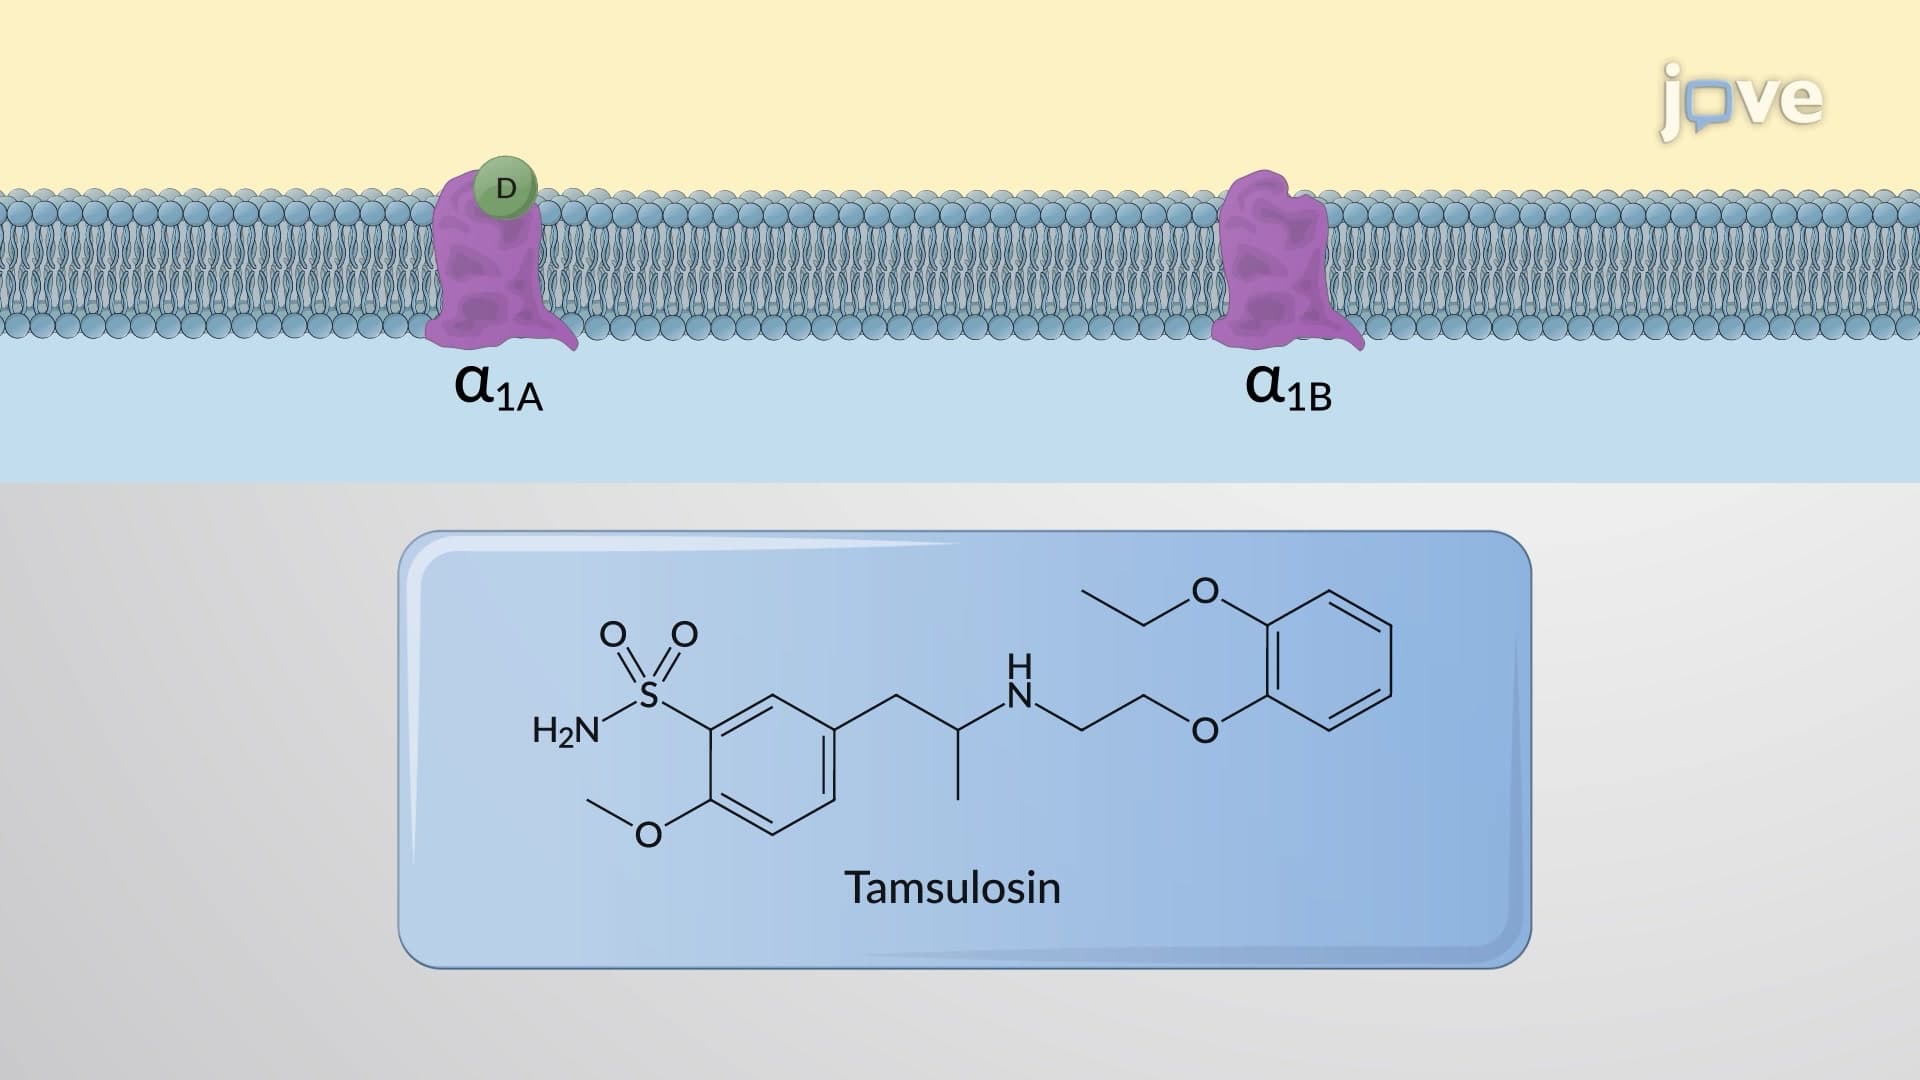
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers