Related Experiment Video
Updated: Jul 30, 2026

Induction and Clinical Scoring of Chronic-Relapsing Experimental Autoimmune Encephalomyelitis
Published on: July 4, 2007
Neurotoxin quinolinic acid is selectively elevated in spinal cords of rats with experimental allergic
E M Flanagan1, J B Erickson, O H Viveros
1Wellcome Research Laboratories, Research Triangle Park, North Carolina 27709.

Abstract:
Experimental allergic encephalomyelitis (EAE) is an autoimmune, animal model of multiple sclerosis (MS) in which demyelination and paralysis are evident. Quinolinic acid (QUIN) is a neurotoxin and endogenous N-methyl-D-aspartate receptor agonist formed from tryptophan. The role of neurotoxins in general and QUIN in particular in EAE or MS is unknown. Lewis rats inoculated with myelin basic protein developed signs of EAE by day 12, were killed, and their tissues assayed for QUIN by gas chromatography with mass spectrometry. QUIN levels were significantly elevated in the more caudal regions of the spinal cords of animals with EAE. Brain, serum, and liver levels of QUIN were not altered. In a similar manner, QUIN in mylin basic protein-injected, asymptomatic animals was not different from control animals. The time course for QUIN was similar to the neurological signs of the disorder; however, the initial elevation in QUIN occurred before the appearance of behavioral signs. Last, treatment with the glucocorticoid dexamethasone prevented both the signs of EAE and the elevation in spinal cord QUIN. It is not known whether QUIN contributes to the paralysis in EAE. However, if QUIN is pathogenic in EAE this finding could have therapeutic implications for MS.
More Related Videos
 09:29
Induction of Paralysis and Visual System Injury in Mice by T Cells Specific for Neuromyelitis Optica Autoantigen Aquaporin-4
Published on: August 21, 2017
 09:46
Rat Model of Widespread Cerebral Cortical Demyelination Induced by an Intracerebral Injection of Pro-Inflammatory Cytokines
Published on: September 21, 2021
Related Concept Videos
 01:22
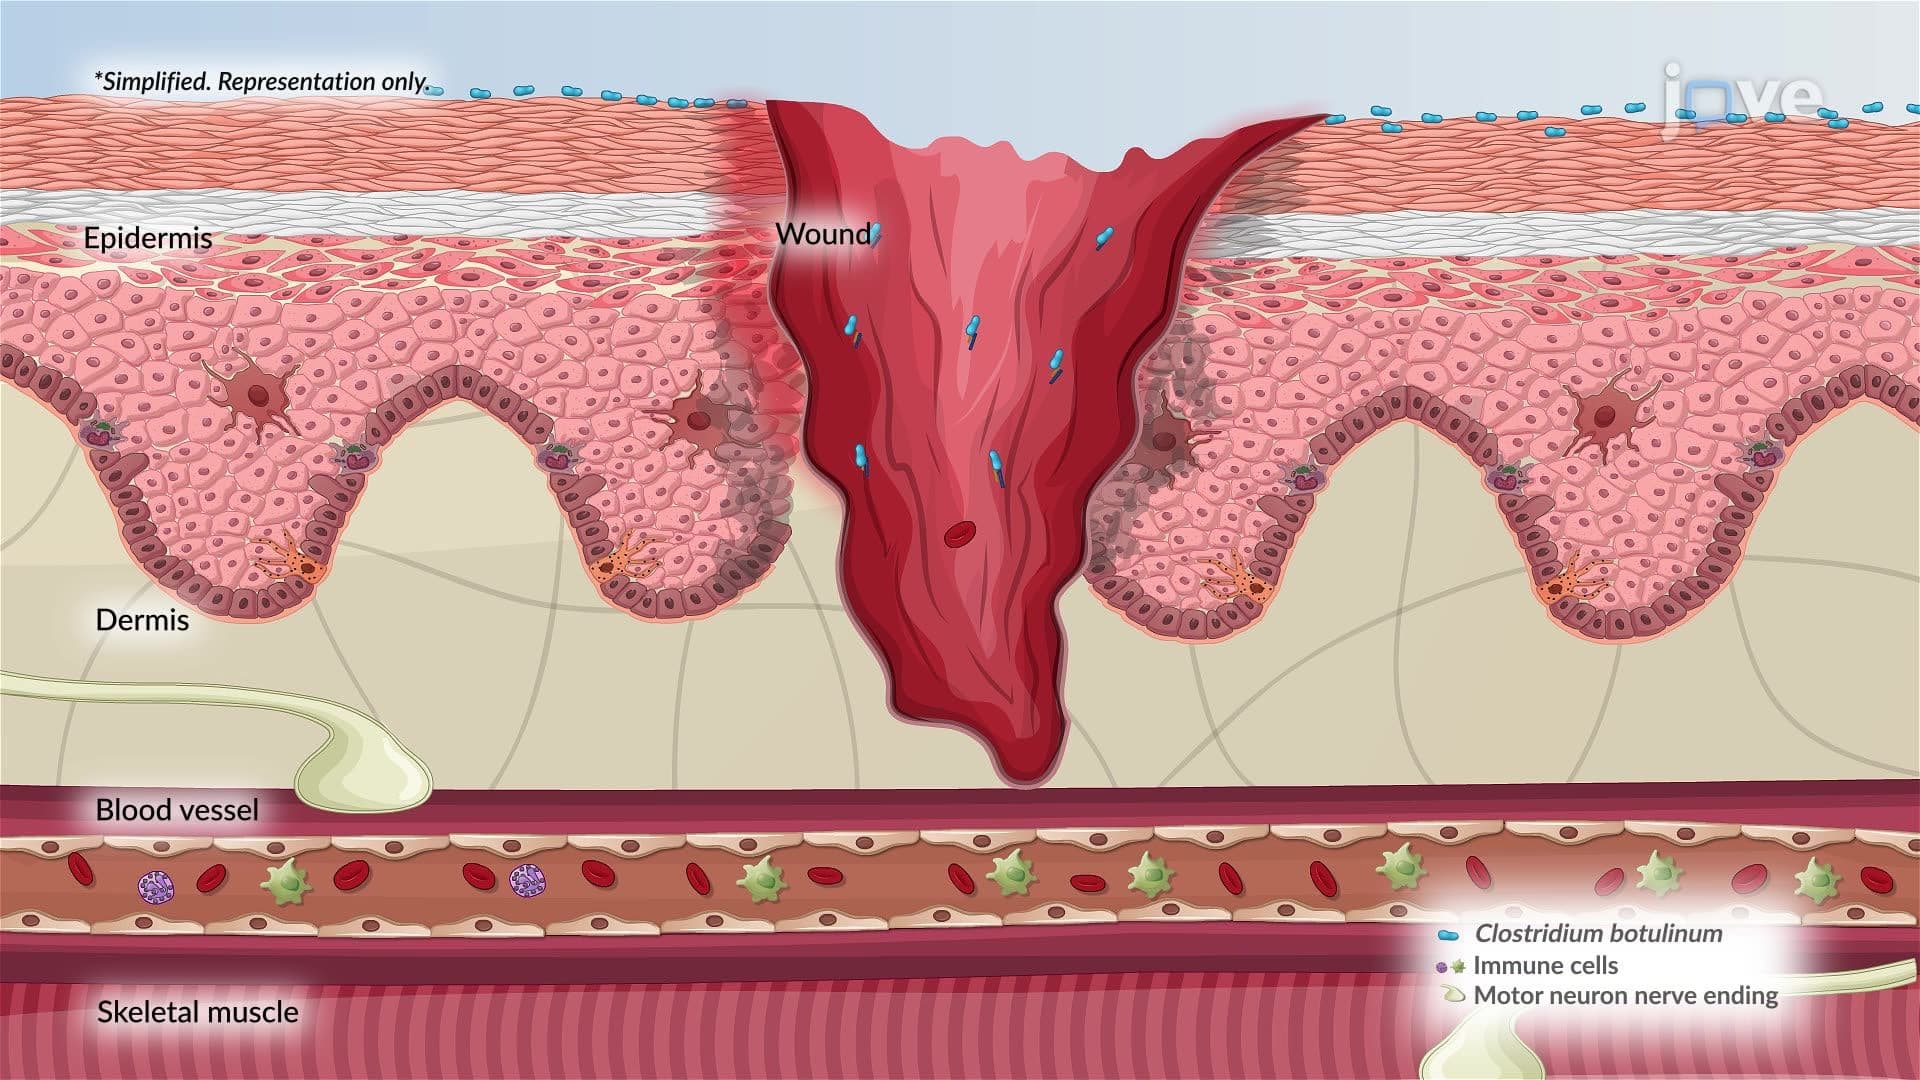
Botulism
 01:26
Encephalitis ll: Pathophysiology