Related Experiment Video
Updated: Aug 18, 2026


Measurement of the Pressure-volume Curve in Mouse Lungs
Published on: January 27, 2015
Increased alveolar/capillary membrane resistance to gas transfer in patients with chronic heart failure
S Puri1, B L Baker, C M Oakley
1Department of Medicine (Clinical Cardiology), Royal Postgraduate Medical School, Hammersmith Hospital, London.

Objective:
To investigate pulmonary diffusive resistance to gas exchange in patients with heart failure and healthy volunteers, assessing the relative contributions of the alveolar/capillary membrane and pulmonary capillary blood.
Setting:
Hospital outpatient department and pulmonary function laboratory.
Patients:
38 patients (mean age 60) receiving treatment with loop diuretics and angiotensin converting enzyme inhibitors for stable symptomatic heart failure of > 6 months duration (New York Heart Association (NYHA) classes II and III). Results were compared with those of 17 healthy volunteers (mean age 52).
Methods:
The alveolar/capillary membrane diffusive resistance and the pulmonary capillary blood volume available for physiological gas exchange were determined by the Roughton and Forster method, which measures the single breath pulmonary diffusing capacity for carbon monoxide at varying alveolar oxygen concentrations.
Results:
Total pulmonary diffusive resistance was higher in patients than controls. Alveolar/capillary membrane resistance formed the main component of this increase, accounting for a mean (SD) of 63% (20%) and 86% (8%) of total pulmonary diffusive resistance in patients in NYHA II and III classes respectively, compared with 53% (10%) in controls. The pulmonary capillary blood volume was not significantly different between controls and patients in NYHA class II (66 (18) ml v 61 (18) ml), but was increased in those in NYHA class III (95(46) ml, P < 0.05).
Conclusion:
This study confirmed impairment of pulmonary diffusion at rest in patients with chronic heart failure and identified impaired alveolar/capillary membrane function as the main factor responsible.
More Related Videos
 07:09
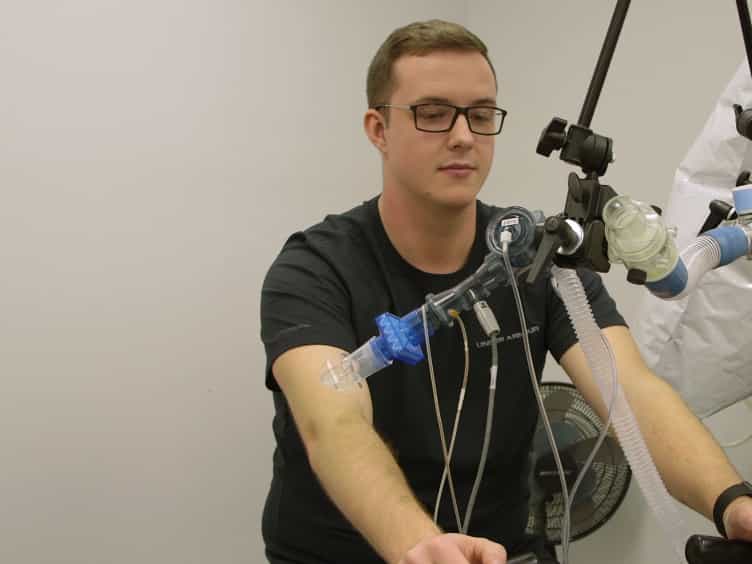
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 08:44
Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
Related Concept Videos
 01:05
Breathing
 01:24
External and Internal Respiration
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Acute Respiratory Failure-III
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:18
Pulmonary Edema II: Pathophysiology