Related Experiment Video
Updated: Aug 15, 2026
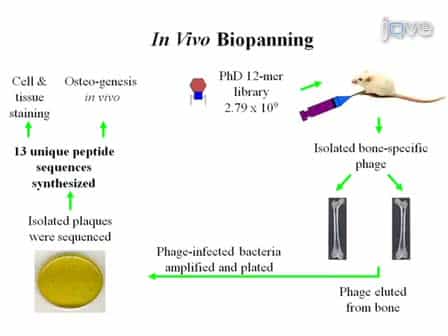

Peptides from Phage Display Library Modulate Gene Expression in Mesenchymal Cells and Potentiate Osteogenesis in Unicortical Bone Defects
Published on: December 10, 2010
The effect of phosphate supplementation on linear growth in children with X-linked hypophosphatemia
M G Seikaly1, R H Browne, M Baum
1Department of Pediatrics, University of Texas Southwestern Medical School, Dallas.

Insights
X-linked hypophosphatemia treatment with vitamin D alone or with phosphate improved growth. Adding phosphate later did not further enhance growth compared to initial combination therapy, suggesting similar linear growth outcomes.
Area of Science:
- Pediatric Endocrinology
- Metabolic Bone Disease
- Genetics
Background:
- X-linked hypophosphatemia (XLH) is the most common inherited cause of rickets.
- Current treatments involve vitamin D and phosphate supplementation.
- Phosphate therapy carries a risk of nephrocalcinosis.
Purpose of the Study:
- To evaluate the impact of oral phosphate therapy on growth in XLH patients.
- To compare growth outcomes between calcitriol and dihydrotachysterol (vitamin D) treatments.
- To assess the effect of adding phosphate to existing vitamin D therapy.
Main Methods:
- Retrospective analysis of prepubertal growth in 36 children with XLH.
- Comparison of height standard deviation scores (Z-scores) between treatment groups.
- Evaluation of growth changes with vitamin D alone versus combined vitamin D and phosphate therapy.
Main Results:
- Vitamin D monotherapy improved Z-scores over time (P < .05).
- Adding phosphate to vitamin D therapy did not significantly improve Z-scores further.
- Initial combined vitamin D and phosphate therapy also improved Z-scores (P < .05).
- The change in Z-score was comparable between vitamin D alone and initial combined therapy groups.
Conclusions:
- Both vitamin D alone and combined vitamin D plus phosphate improve linear growth in XLH.
- Late addition of oral phosphate does not enhance growth compared to initial combined therapy.
- Initial treatment strategies yield similar linear growth outcomes.
Background:
X-linked hypophosphatemia is the most common inherited cause of rickets. Current therapy for this disorder includes vitamin D and phosphate supplementation; however, phosphate therapy has been associated with nephrocalcinosis. The purpose of this study is to evaluate the effect of oral phosphate therapy on growth in patients with X-linked hypophosphatemia treated with either calcitriol or dihydrotachysterol (vitamin D).
Methods:
We retrospectively evaluated the prepubertal growth of 36 children with X-linked hypophosphatemia. The height standard deviation score (Z-score) of patients initially treated with vitamin D alone and the Z-scores of patients treated with vitamin D and phosphate therapy were compared. In addition, the growth of therapy were compared. In addition, the growth of patients treated with vitamin D was compared with that of patients treated with vitamin D and phosphate from the outset of therapy.
Results:
Patients treated with vitamin D alone for 5.36 +/- 2.18 years had an improvement in Z-score from -3.1 +/- 1.10 to -2.49 +/- 0.66 SDS, P < .05. Adding phosphate therapy for patients initially treated with vitamin D alone for 4.83 +/- 2.99 years did not further improve Z-score (-2.49 +/- 0.66 vs -2.35 +/- 0.83). Initial therapy with vitamin D and phosphate for 4.33 +/- 2.19 years also improved Z-score, (-2.84 +/- 1.02 vs -1.98 +/- 0.82, P < .05). The change in Z-score was similar to the group treated with vitamin D alone compared with the group treated initially with vitamin D and phosphate (0.65 +/- 0.54 vs 0.85 +/- 0.65, respectively).
Conclusion:
These data demonstrate that both vitamin D alone and in combination with phosphate improved linear growth. Adding oral phosphate for children initially treated with vitamin D alone did not improve Z-score. Initial therapy with vitamin D and vitamin D plus phosphate produced similar changes in linear growth.


Related Concept Videos
 01:02
Phosphorylation
During phosphorylation, protein kinases transfer the terminal phosphate group of ATP to specific amino acid side chains of substrate proteins. Serine, threonine, and tyrosine are the most commonly...
 01:10
Nature and Nurture
 01:33
Introduction to Electrolytes
Role of Sodium
One...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:27
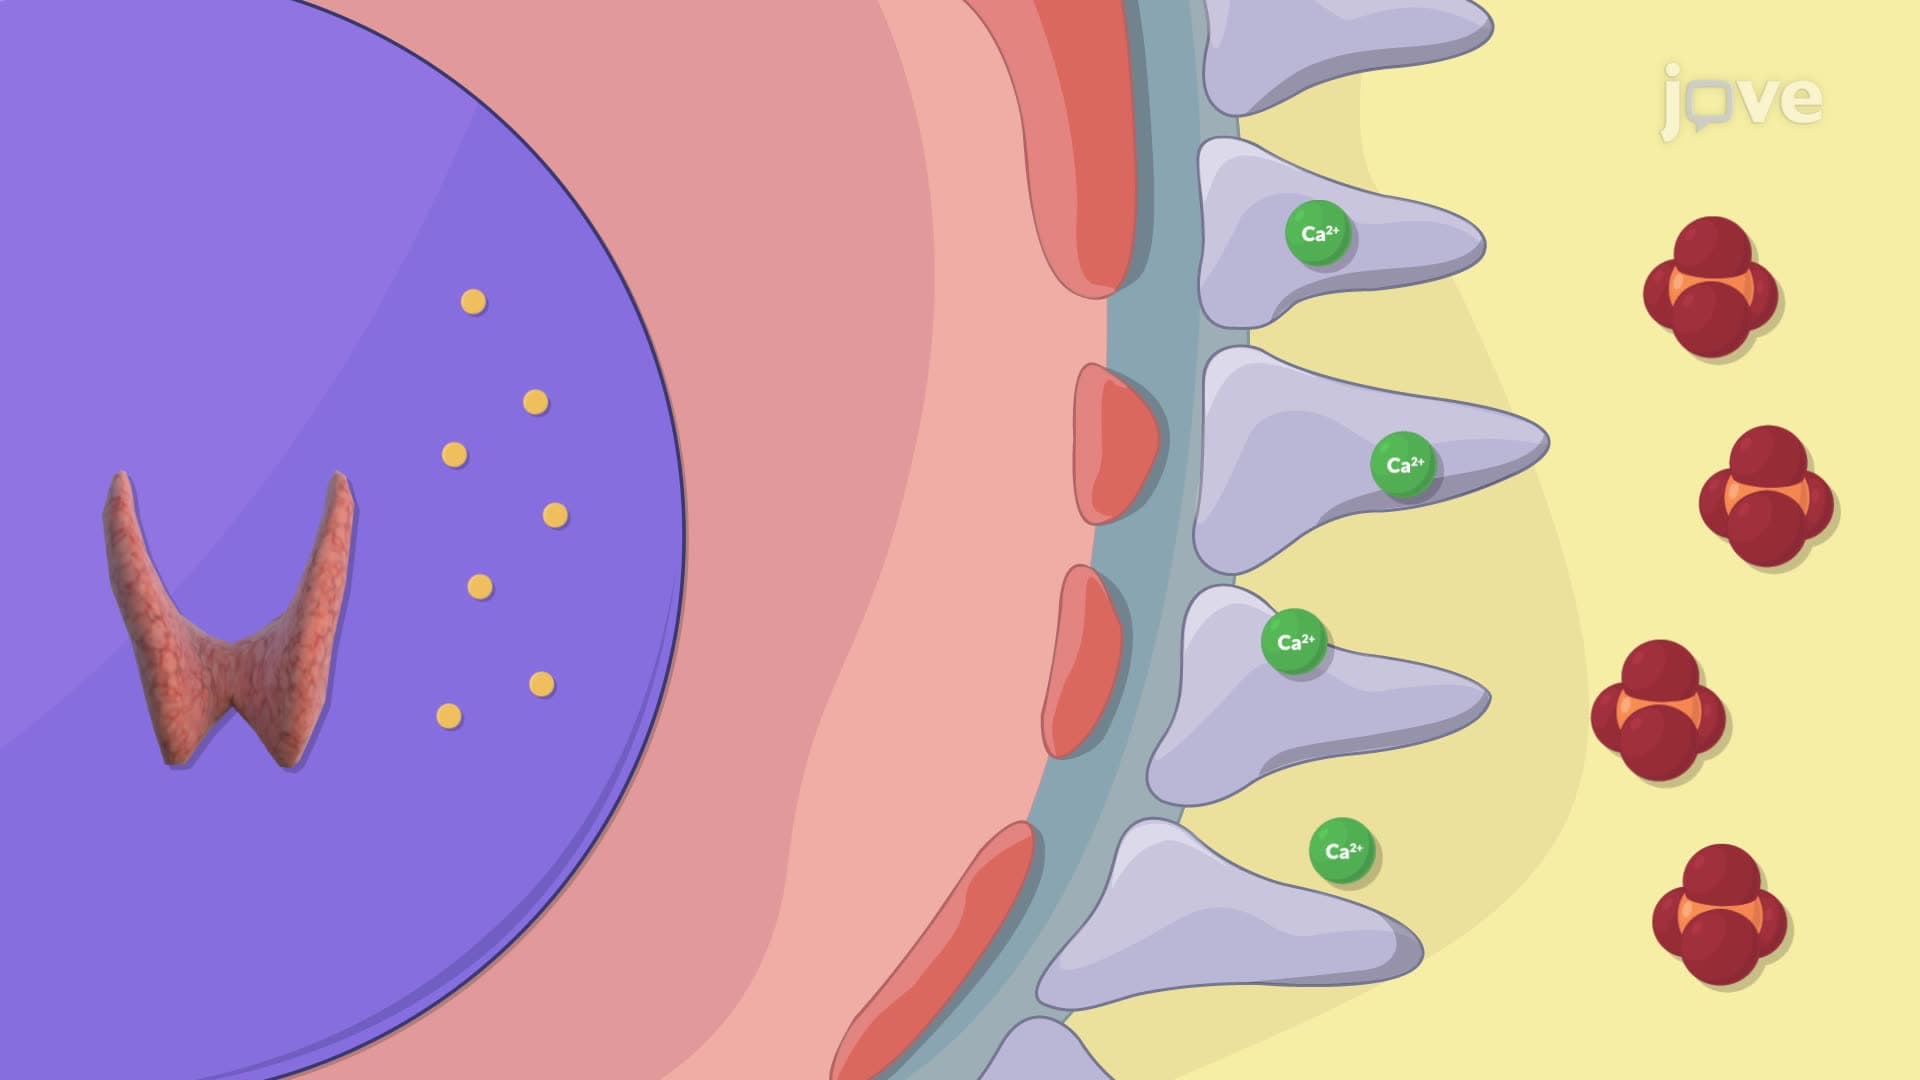
Roles of Electrolytes: Calcium and Phosphate
The calcium concentration in blood plasma is primarily regulated...
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution