Related Experiment Video
Updated: Aug 18, 2026
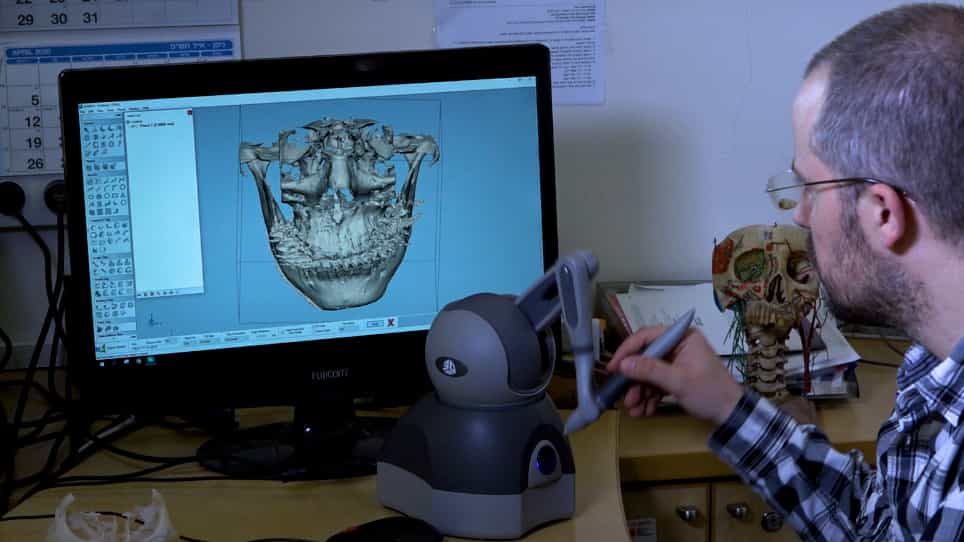

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Osteology of the pediatric skull. Considerations of halo pin placement
1Children's Rehabilitative Services, Phoenix, Arizona.

Insights
Pediatric skull thickness varies significantly, with no consistently safe area for halo pin placement. Preoperative CT scans are recommended to identify optimal pin insertion sites in children.
Area of Science:
- Pediatric neurosurgery
- Craniofacial imaging
- Orthopedic fixation
Background:
- Halo pin placement complications, such as loosening, dislodgement, infection, and penetration, are common in children.
- Understanding pediatric skull anatomy is crucial for safe halo device application.
Purpose of the Study:
- To identify consistently thin areas in the pediatric skull that should be avoided during halo pin placement.
- To guide safe halo pin insertion in pediatric patients.
Main Methods:
- Computed tomography (CT) scans of 48 normal children (10 years and under) were analyzed.
- Skull thickness was measured in five areas at the level of routine halo pin insertion.
- Children were divided into four age groups to assess age-related changes.
Main Results:
- Skull thickness showed a trend of increasing with age, but with significant variation within and between age groups.
- No standard pin site was consistently thicker across all subjects.
- Even in children up to 10 years old, the average thinnest skull area measured only 1.9 mm.
Conclusions:
- There is no universally "safe area" for halo pin placement in the pediatric skull.
- Preoperative CT imaging is recommended to determine individualized safe zones for pin insertion in pediatric patients.
- This approach can help mitigate complications associated with halo fixation in children.
Study Design:
Computed tomography scans of the heads of 48 normal children were measured for skull thickness in areas of routine halo pin placement. The thickest and thinnest areas were noted.
Objectives:
The head computed tomography scans were measured to identify consistently thin areas in the pediatric skull that should be avoided when pins are placed.
Summary Of Background Data:
Complications of halo pin placement in children are common, including loosening and dislodgment, infection and penetration.
Methods:
Normal head computed tomography scans of 48 normal children, 10 years old and under, were divided into four age groups. Total skull thickness was measured in five areas at the level of halo insertion.
Results:
There was a trend toward increasing skull thickness with age. There was a large variation in skull thickness at each area within and between age groups. None of the standard pin sites was consistently thicker. Even up to 10 years of age, the average thinnest area was only 1.9 mm.
Conclusions:
There is no "safe area" for halo pin placement in the pediatric skull. Limited preoperative head computed tomography scans are recommended to determine safe areas for pin placement.
More Related Videos
 06:18
Pedicle Screw Placement Using an Augmented Reality Head-Mounted Display in a Porcine Model
Published on: May 24, 2024
 14:34
Surgical Protocol for a Large, Resealable Cranial Window Enabling Longitudinal, Multi-Modal Electrophysiology Recordings of Mouse Default Mode Network
Published on: May 29, 2026
