Related Experiment Video
Updated: Aug 10, 2026

Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Body electrolytes in bronchopulmonary dysplasia and the effects of diuretic therapy
1Department of Pediatrics, Hahnemann University Hospital, Philadelphia, PA 19102.

Insights
Infants with bronchopulmonary dysplasia (BPD) struggle to dilute urine, leading to water retention. Diuretic therapy and fluid restriction are effective treatments for managing electrolytes and hormones in these preterm infants.
Area of Science:
- Pediatric Nephrology
- Neonatology
- Pulmonology
Background:
- Bronchopulmonary dysplasia (BPD) is a chronic lung disease in preterm infants.
- Electrolyte and hormone imbalances are common in BPD, affecting fluid balance.
- Understanding these imbalances is crucial for effective management.
Purpose of the Study:
- To investigate body electrolytes and regulatory hormones in preterm infants with BPD.
- To compare infants with and without diuretic treatment.
- To compare BPD infants with healthy controls.
Main Methods:
- Studied body electrolytes and regulatory hormones in three groups of infants: healthy controls (Group I), BPD infants not treated with diuretics (Group II), and BPD infants treated with diuretics (Group III).
- Analyzed serum and urinary electrolytes (Na, K), specific gravity, flow rate, and fractional excretion of sodium (FeNa).
- Measured serum aldosterone levels and assessed correlations between electrolytes, hormones, and fluid balance.
Main Results:
- Group II infants showed lower serum Na, higher Na intake needs, higher urinary Na concentration, and higher specific gravity, suggesting impaired urine dilution.
- Group III infants had higher serum Na and lower urinary specific gravity compared to Group II, with values similar to controls.
- Aldosterone levels were highest in Group II, with significant negative correlations between serum Na and aldosterone, and between FeNa and aldosterone in BPD groups.
Conclusions:
- Preterm infants with BPD may have an impaired ability to dilute urine, leading to body water retention.
- Water restriction and diuretic therapy are indicated as reasonable therapeutic approaches for managing fluid balance in BPD.
- Hormonal regulation, particularly involving aldosterone, plays a role in electrolyte and fluid disturbances in BPD.
Abstract:
Body electrolytes and their regulatory hormones were studied in preterm infants who suffered from bronchopulmonary dysplasia under two groups: those who were not treated with diuretics (Group II), and those who were treated with diuretics (Group III). The values were compared with a group of matched healthy controls (Group I). Lower serum Na levels, a need of higher Na intake, and higher urinary Na concentrations and urinary specific gravity were found in Group II infants. FeNa was normal and the urinary flow rate was lower than the controls. These data suggest an inability of these infants to dilute urine. Group III infants who were treated with diuretics showed higher serum Na levels and lower urinary specific gravity than Group II infants. These values, as well as water and Na intake/output ratios, were all similar to the control values. Serum aldosterone level was highest in Group II but did not reach significance. Intracellular K concentration was not different between the groups indicating an optimum total body K balance. A significant negative correlation between serum Na and aldosterone levels was found in Group II infants, which was not noted in the controls. Significant correlations were also found between FeNa and plasma aldosterone level in the BPD groups, unlike the controls. The control group of infants showed significant positive correlation between Na balance and serum Na levels. Our results suggest that inability to dilute urine appropriately might be the reason for the BPD patients to retain body water. Water restriction and diuretic therapy therefore are reasonable therapeutic approaches in such cases.
More Related Videos
 09:36
Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
 03:25
Ginger Moxibustion, A Non-pharmacological Treatment, for Diarrhea in Patients with Chronic Obstructive Pulmonary Disease
Published on: December 27, 2024
Related Concept Videos
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:22
Heart Failure Drugs: Diuretics
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting, or...
 01:22
Acute Kidney Injury VI: Nursing Management
 01:18
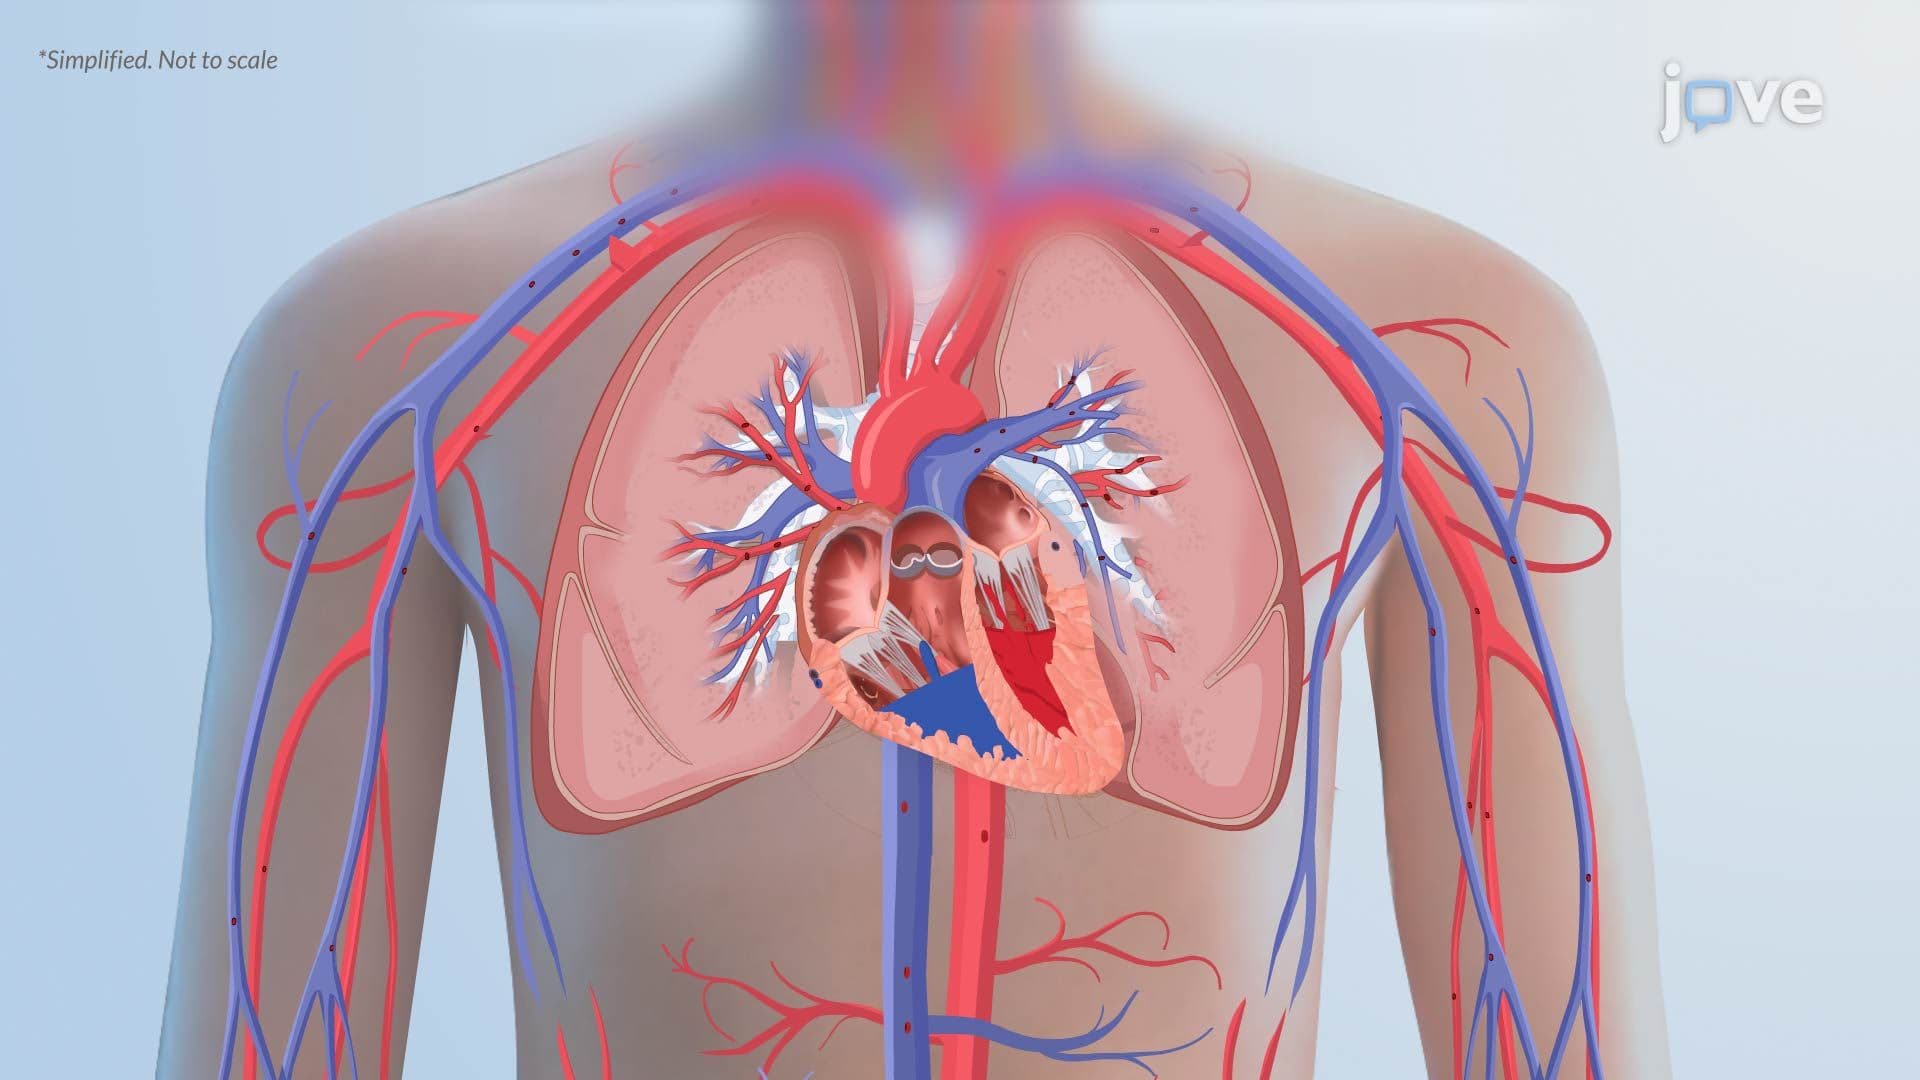
Pulmonary Edema II: Pathophysiology