Related Experiment Video
Updated: Oct 7, 2026


A Hyperandrogenic Mouse Model to Study Polycystic Ovary Syndrome
Published on: October 2, 2018
Long-term gonadotrophin-releasing hormone agonist therapy: the evolving issue of steroidal 'add-back' paradigms
1Department of Obstetrics and Gynecology, University of Maryland School of Medicine, Baltimore 21201.

Abstract:
The introduction of steroid 'add-back' regimens draws on the recognition that several clinical entities targeted for treatment with gonadotrophin-releasing hormone agonist (GnRHa) are not '6-month diseases'. Included under this heading are individuals suffering from symptomatic endometriosis (not desires of pregnancy), uterine fibroids (ineligible or disinterested in definitive surgical therapy), ovarian hyperandrogenism, premenstrual syndrome, menopausal transition, or dysfunctional uterine bleeding. A 6-month course of therapy with a GnRHa does not adversely affect lipoprotein economy and therefore presumably the corresponding cardiovascular risk. A 6-month course of GnRHa therapy appears to be associated with a substantial decrease (of up to 8.2%) in lumbar bone density, a phenomenon which may not be entirely reversible 6 months after discontinuation of therapy. In principle, steroid 'add-back' therapy should diminish some or all of the side-effects associated with GnRHa therapy, may provide a medical treatment option for patients representing a high surgical risk, and may delay surgical intervention if desired. On the other hand, a steroid 'add-back' therapy may delay tissue diagnosis, be associated with a substantial cost as well as with the need for parenteral route of administration. Norethindrone-only (but not medroxyprogesterone acetate-only) 'add-back' regimens have proved promising in the context of endometriosis. Non-concurrent oestrogen/progestin 'add-back' regimens proved promising in the context of uterine fibroids. Substantial additional studies would have to be carried out to validate the utility of steroid 'add-back' regimens. Special emphasis will have to be placed on the evaluation of long-term utility with an eye towards assessing clinical efficacy, impact on lipoprotein economy, impact on bone density, impact on urogenital tissues, and impact on the hot flush. The concurrent or non-concurrent use of non-steroid 'add-back' regimens will also most likely constitute a major component of future studies.

Related Concept Videos
 01:16
TGF - β Signaling Pathway
 01:22
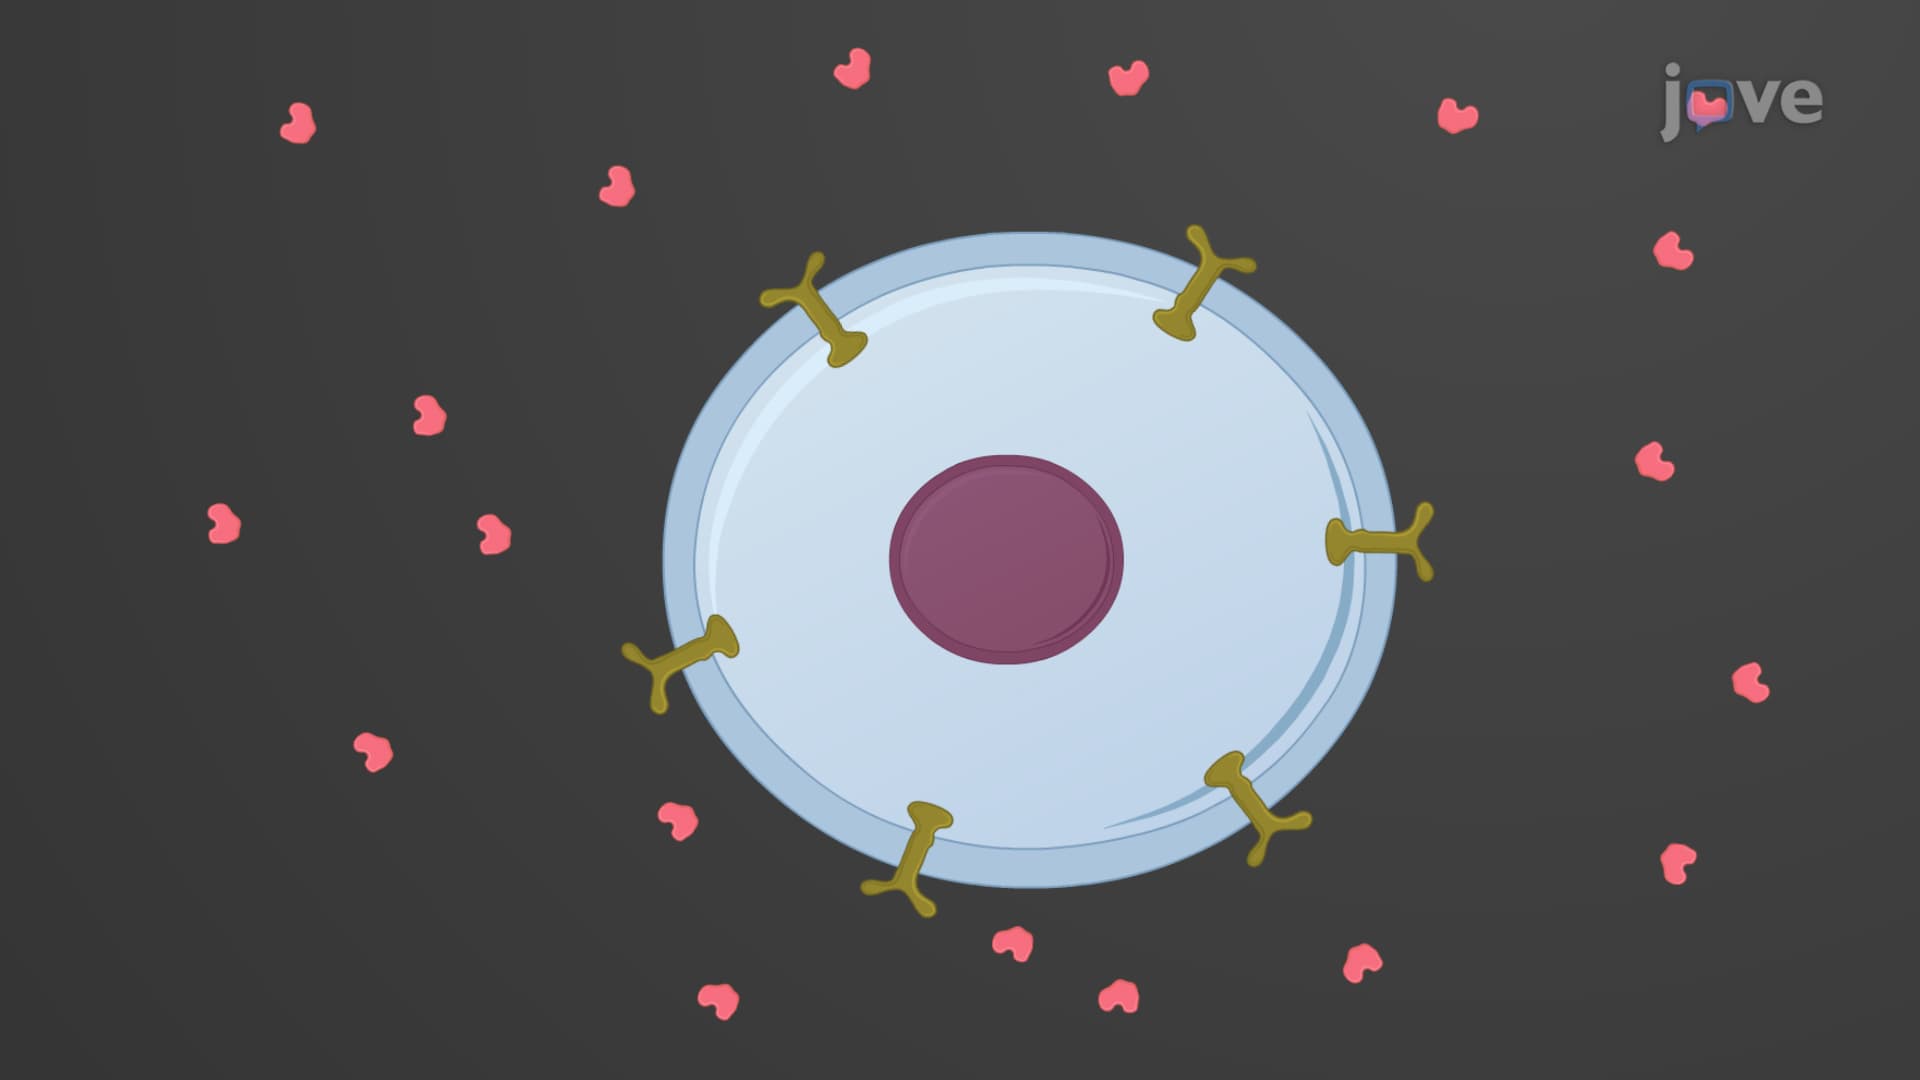
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair growth — and...
 01:26
Drug Administration and Therapy Phases: Overview
The pharmaceutical phase focuses on leveraging the physicochemical properties of the drug to design and manufacture an effective product. Variants include orally administered tablets or capsules, topical creams or ointments, and parenteral-delivery solutions or emulsions.
The pharmacokinetic phase...
 01:21
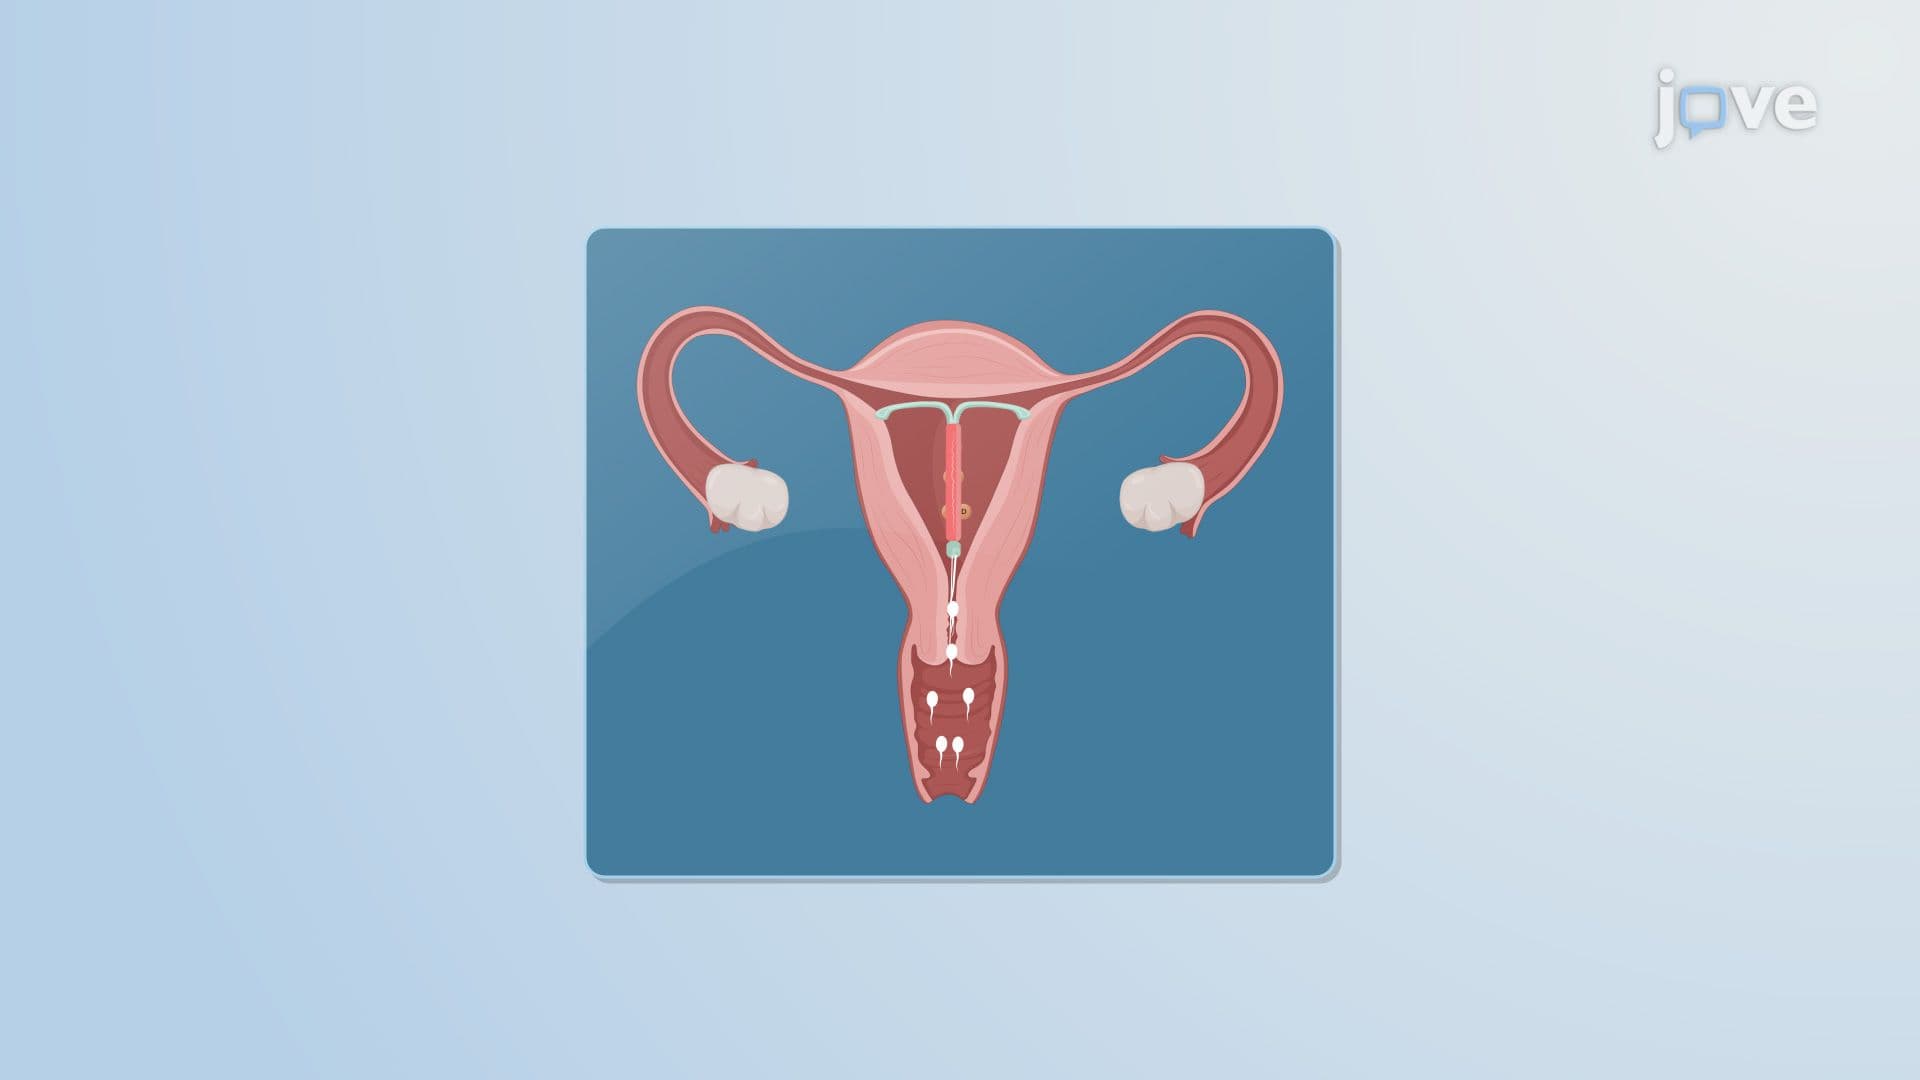
Intrauterine Drug Delivery Systems
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...