Related Experiment Video
Updated: Jun 2, 2026

5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
Pharmacokinetics and pharmacodynamics of lisinopril in advanced renal failure. Consequence of dose adjustment

Abstract:
To prevent drug accumulation and adverse effects the dose of hydrophilic angiotensin-converting enzyme (ACE) inhibitors, e.g. lisinopril, must be reduced in patients with renal failure. To obtain a rational basis for dose recommendations, we undertook a prospective clinical trial. After 15 days of lisinopril treatment pharmacokinetic and pharmacodynamic parameters were determined in patients with advanced renal failure (n = 8; endogenous creatinine clearance [CLCR]: 18 ml.min-1.1.73 m-2) and in healthy subjects with normal renal function (n = 16; CLCR: 107 ml.min-1.1.73 m-2). The volunteers received 10 mg lisinopril once daily, the daily dose in patients (1.1-2.2 mg) was adjusted to the individual CLCR according to the method of Dettli [13]. After 15 days of lisinopril treatment the mean maximal serum concentration (Cmax) in patients was lower than in volunteers (30.7 vs 40.7 ng.ml-1, while the mean area under the concentration-time curve (AUC0-24 h) was higher (525 vs 473 ng.h-1.ml-1). ACE activity on day 15 was almost completely inhibited in both groups. Plasma renin activity, angiotensin I and angiotensin II levels documented marked inhibition of converting enzyme in volunteers and patients. Furthermore, average mean arterial blood pressure in patients decreased by 5 mmHg and proteinuria from 3.9-2.7 g per 24 h after 15 days of treatment with the reduced dose of lisinopril. Adjustment of the dose of lisinopril prevents significant accumulation of the drug in patients with advanced renal failure during chronic therapy. Mean serum levels did not exceed this in subjects with normal renal function receiving a standard dose.(ABSTRACT TRUNCATED AT 250 WORDS)


Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:14
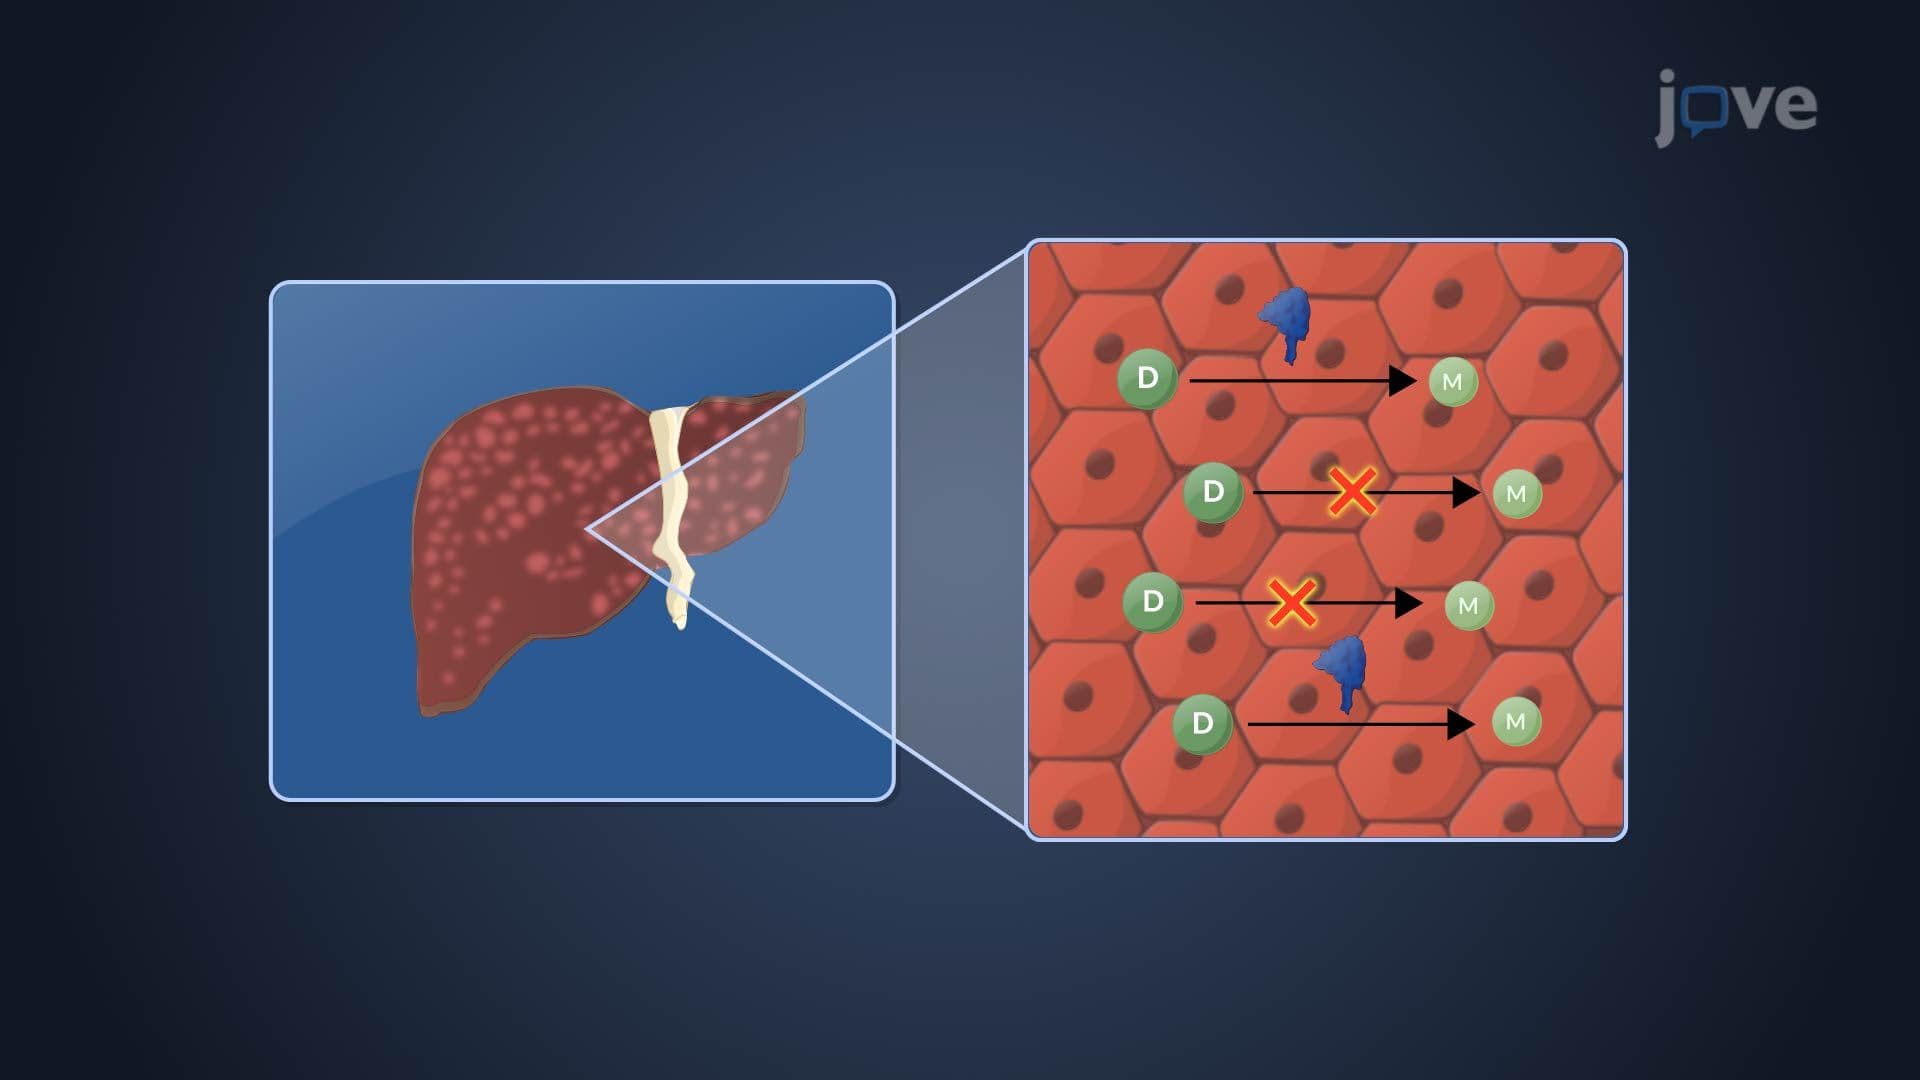
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant