Related Experiment Video
Updated: Aug 9, 2026


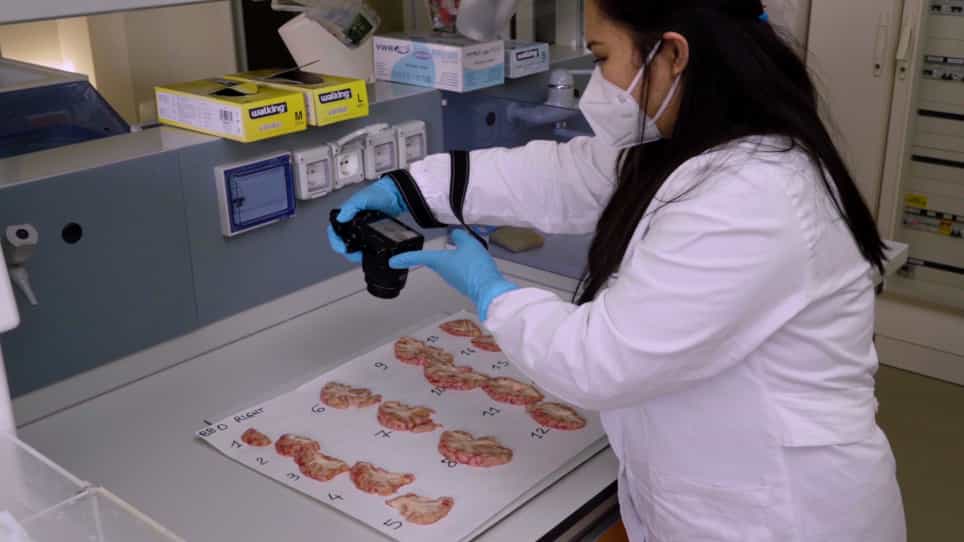
Symmetric Bihemispheric Postmortem Brain Cutting to Study Healthy and Pathological Brain Conditions in Humans
Published on: December 18, 2016
Atheromatous embolism in the brain: a clinicopathologic analysis of 15 autopsy cases

Insights
Cerebral atheromatous embolism, often triggered by cardiovascular procedures, causes brain infarcts. Cholesterol crystal emboli frequently lead to border-zone infarcts by blocking small arteries.
Area of Science:
- Neuropathology
- Cardiovascular Pathology
Background:
- Cerebral atheromatous embolism is a serious complication.
- Cardiovascular interventions can precipitate atheromatous embolism in the brain.
Purpose of the Study:
- To analyze the pathological features of cerebral atheromatous embolism.
- To investigate the triggers and resulting infarct patterns.
Main Methods:
- Autopsy examination of 15 cases with cerebral atheromatous embolism.
- Pathological analysis of brain tissue and occluded leptomeningeal arteries.
Main Results:
- Six cases were linked to cardiovascular surgery or catheterization.
- Nine cases had unclear triggers.
- Cortical border-zone hemorrhagic infarcts were common, caused by emboli in leptomeningeal arteries (50-300 microns).
- Arterial territorial infarcts occurred in six cases, with some showing larger occlusions.
Conclusions:
- Atheromatous embolism frequently causes border-zone infarcts via terminal cortical branch occlusion.
- Large, fibrin-associated emboli can lead to arterial territorial infarcts.
Abstract:
We report 15 autopsy cases with cerebral atheromatous embolism (14 men and one woman, 57 to 76 years of age) and analyze their pathologic features. Cardiovascular surgery or catheterization triggered the atheromatous embolism in the brain in six cases (aortocoronary bypass, two; emergency aortocoronary bypass after percutaneous transluminal coronary angioplasty, one; graft implantation for thoracic aortic aneurysm, two; coronary angiography, one). The events that had triggered embolism were not clear in the remaining nine cases. Pathologic examination of the brains revealed that nine cases had single or multiple cortical hemorrhagic infarcts corresponding to the border zones between two main cerebral arterial territories. Many of the leptomeningeal arteries located in the subarachnoid spaces of cortical sulci and surfaces adjacent to the infarcts were occluded by atheromatous emboli composed mostly of cholesterol crystals. The internal diameters of the occluded arteries ranged from 50 to 300 microns. Arterial territorial infarcts were present in six cases, three of which had thromboemboli containing various amounts of cholesterol crystals occluding the major arteries or their large branches supplying the infarcted areas, which were pale in two cases and hemorrhagic in one. The other three cases had hemorrhagic infarcts in which atheromatous emboli were present only in the small leptomeningeal arteries and were composed mostly of cholesterol crystals. Atheromatous embolism in the brain frequently causes border-zone infarcts by occlusion of the terminal cortical branches, and sometimes causes arterial territorial infarcts if the emboli are associated with fibrin and sufficiently large to occlude the larger arteries.

Related Concept Videos
 01:30
Venous Thrombosis I: Introduction
 01:15
Ischemic Stroke l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology