Related Experiment Video
Updated: Jul 26, 2026
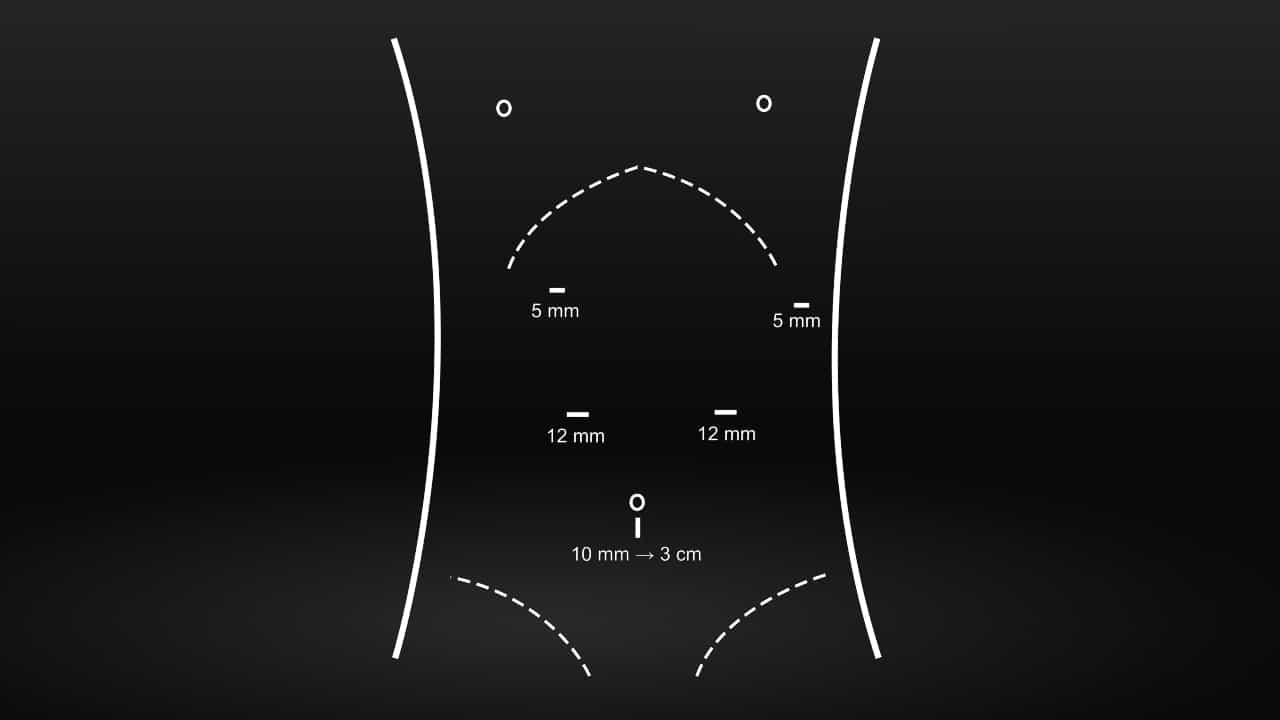

Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Acute variceal hemorrhage: the persistent bleeder. A plea for management
M S Barsoum1, F I Boulos, A M Aly
1Department of Surgery, Kasr El Aini School of Medicine, Cairo University, Egypt.

Abstract:
A group of 1910 patients with acutely bleeding esophagogastric varices were managed in the Kasr El Aini sclerotherapy project; 458 of the patients (24%) were lost to follow-up. The remaining patients were studied in five groups: group I (294/401 patients), rigid versus flexible sclerotherapy; group II (254/336 patients), intravariceal versus paravariceal sclerotherapy; group III (174/227 patients), timing of initial sclerotherapy and the optimum frequency of sclerotherapy sessions; group IV (80/99 patients), splenectomy devascularization operation alone versus combined surgery with sclerotherapy; group V (650/847 patients), management of failures of and recurrences after sclerotherapy. The mean period of follow-up was 72 months. Rigid sclerotherapy was significantly superior to flexible sclerotherapy for emergency control of acute bleeding but was associated with significantly more morbidity. Paravariceal injection achieved insignificantly better initial control of bleeding and had more morbidity than intravariceal injection, which obliterated the varices in a significantly larger proportion of patients. Emergency injection of the acute bleeder should be carried out soon after admission, with sclerotherapy sessions repeated every 2 weeks. Combined sclerotherapy with splenectomy and devascularization was significantly more effective for controlling bleeding than surgery alone. Surgery should be done without delay for continued bleeding after the second attempt of sclerotherapy and in patients who rebleed after their third sclerotherapy session. Survival, however, was not significantly improved by the different modalities of sclerotherapy.


Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:22
Aneurysm IV: Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management