Related Experiment Video
Updated: Aug 10, 2026

Flexible Colonoscopy in Mice to Evaluate the Severity of Colitis and Colorectal Tumors Using a Validated Endoscopic Scoring System
Published on: October 16, 2013
National audit of complicated diverticular disease: analysis of index cases
R G Tudor1, N Farmakis, M R Keighley
1Department of Surgery, Queen Elizabeth Hospital, Birmingham, UK.

Abstract:
Details of 300 patients with complicated diverticular disease from 30 hospitals between 1985 and 1988 were entered into a national audit organized by the Surgical Research Society. Complications present on admission included acute phlegmon (n = 104), pericolic abscess (n = 34), purulent peritonitis (n = 40), large bowel obstruction (n = 31), faecal peritonitis (n = 23), pericolic abscess complicated by fistula (n = 28) and lower gastrointestinal bleeding (n = 40). The overall mortality rate was 11.3 per cent (acute phlegmon, 4 per cent; purulent peritonitis, 27 per cent; pericolic abscess, 12 per cent; faecal peritonitis, 48 per cent; large bowel obstruction, 6 per cent; bleeding, 2 per cent; fistula, 4 per cent). Acute phlegmon was treated without operation in 78 patients (75.0 per cent) and by resection in 24 (23.1 per cent). Management of purulent peritonitis generally involved Hartmann's procedure (62 per cent) or resection and primary anastomosis (15 per cent). Similarly, patients with pericolic abscess usually underwent Hartmann's procedure (38 per cent) or resection and primary anastomosis (35 per cent). The principal operation for faecal peritonitis was Hartmann's resection (83 per cent). Large bowel obstruction was managed conservatively in four patients (13 per cent), by Hartmann's procedure in nine (29 per cent), and by resection and primary anastomosis with or without a proximal stoma in 13 (42 per cent). Most patients (82 per cent) with fistula associated with an abscess were managed by resection and primary anastomosis; 90 per cent with acute gastrointestinal bleeding were treated without operation.

Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:27
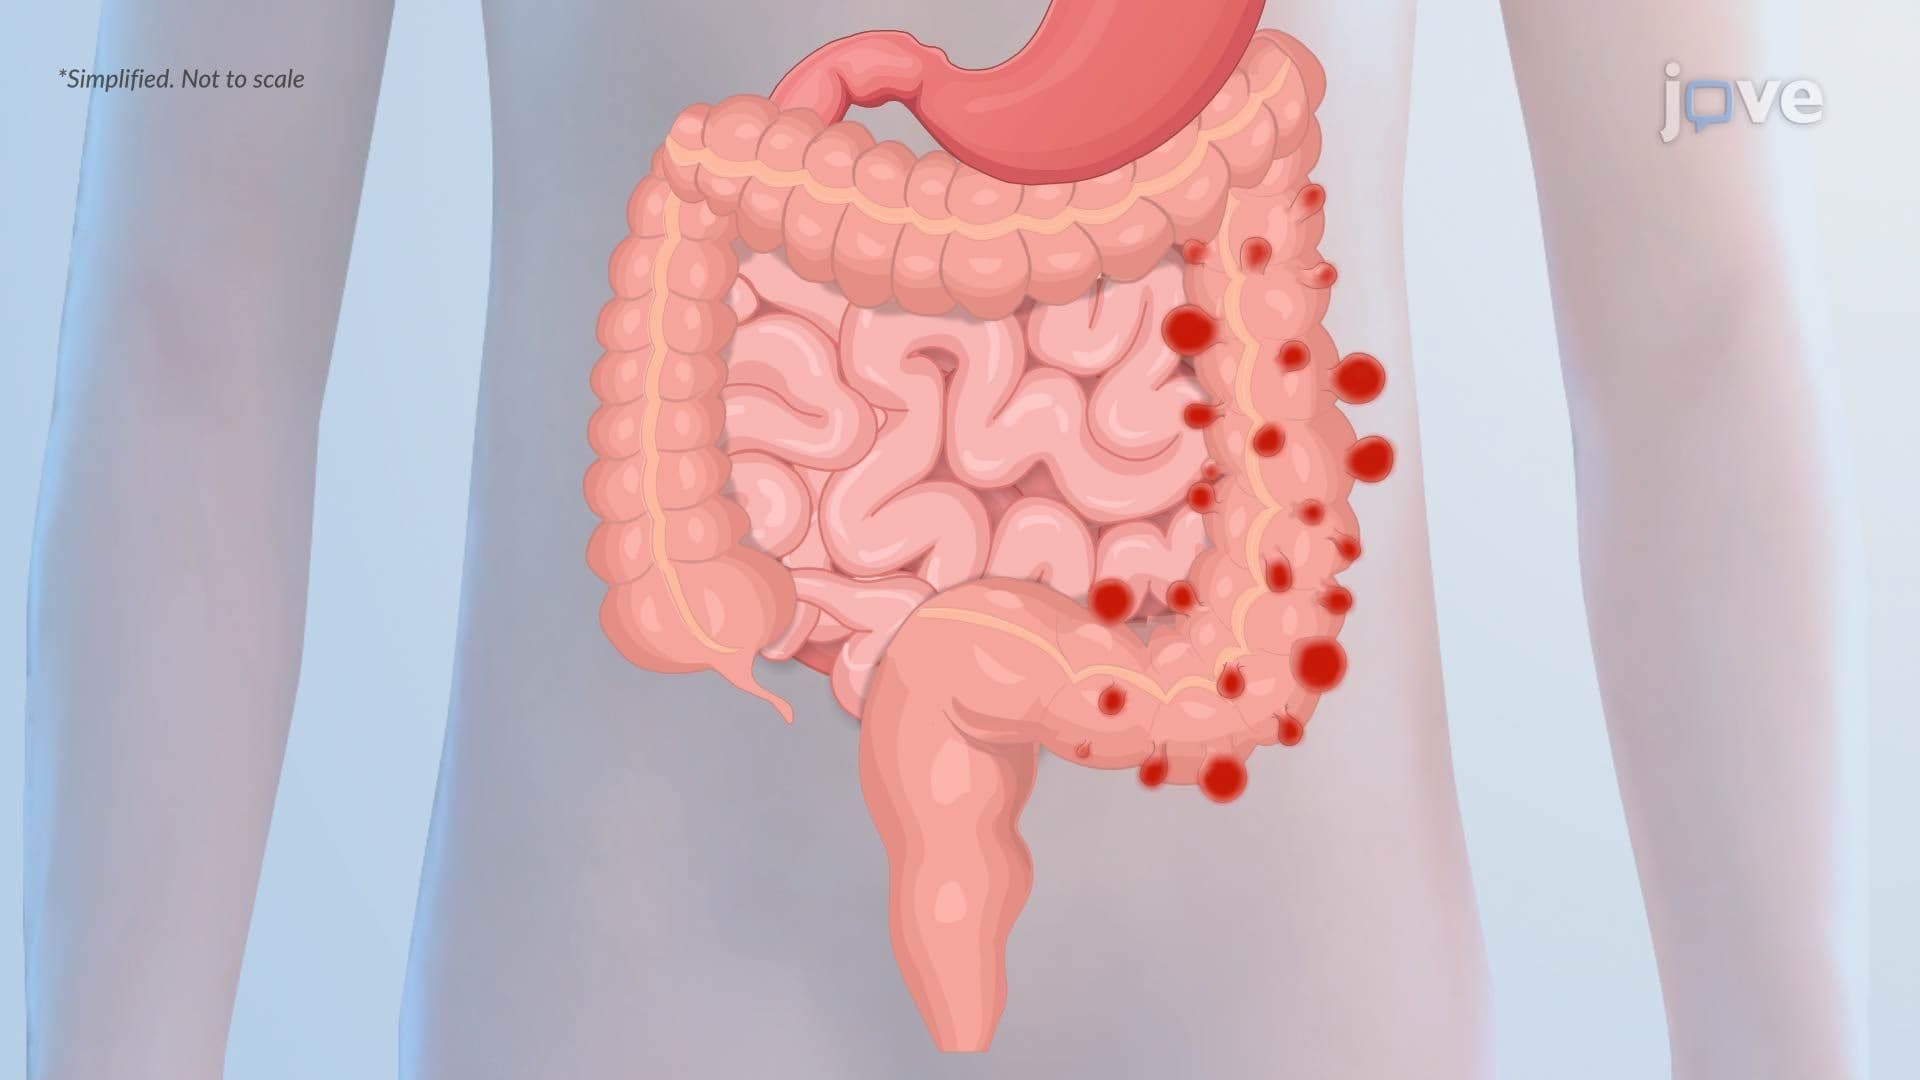
Diverticular Disease of the Colon
 01:19
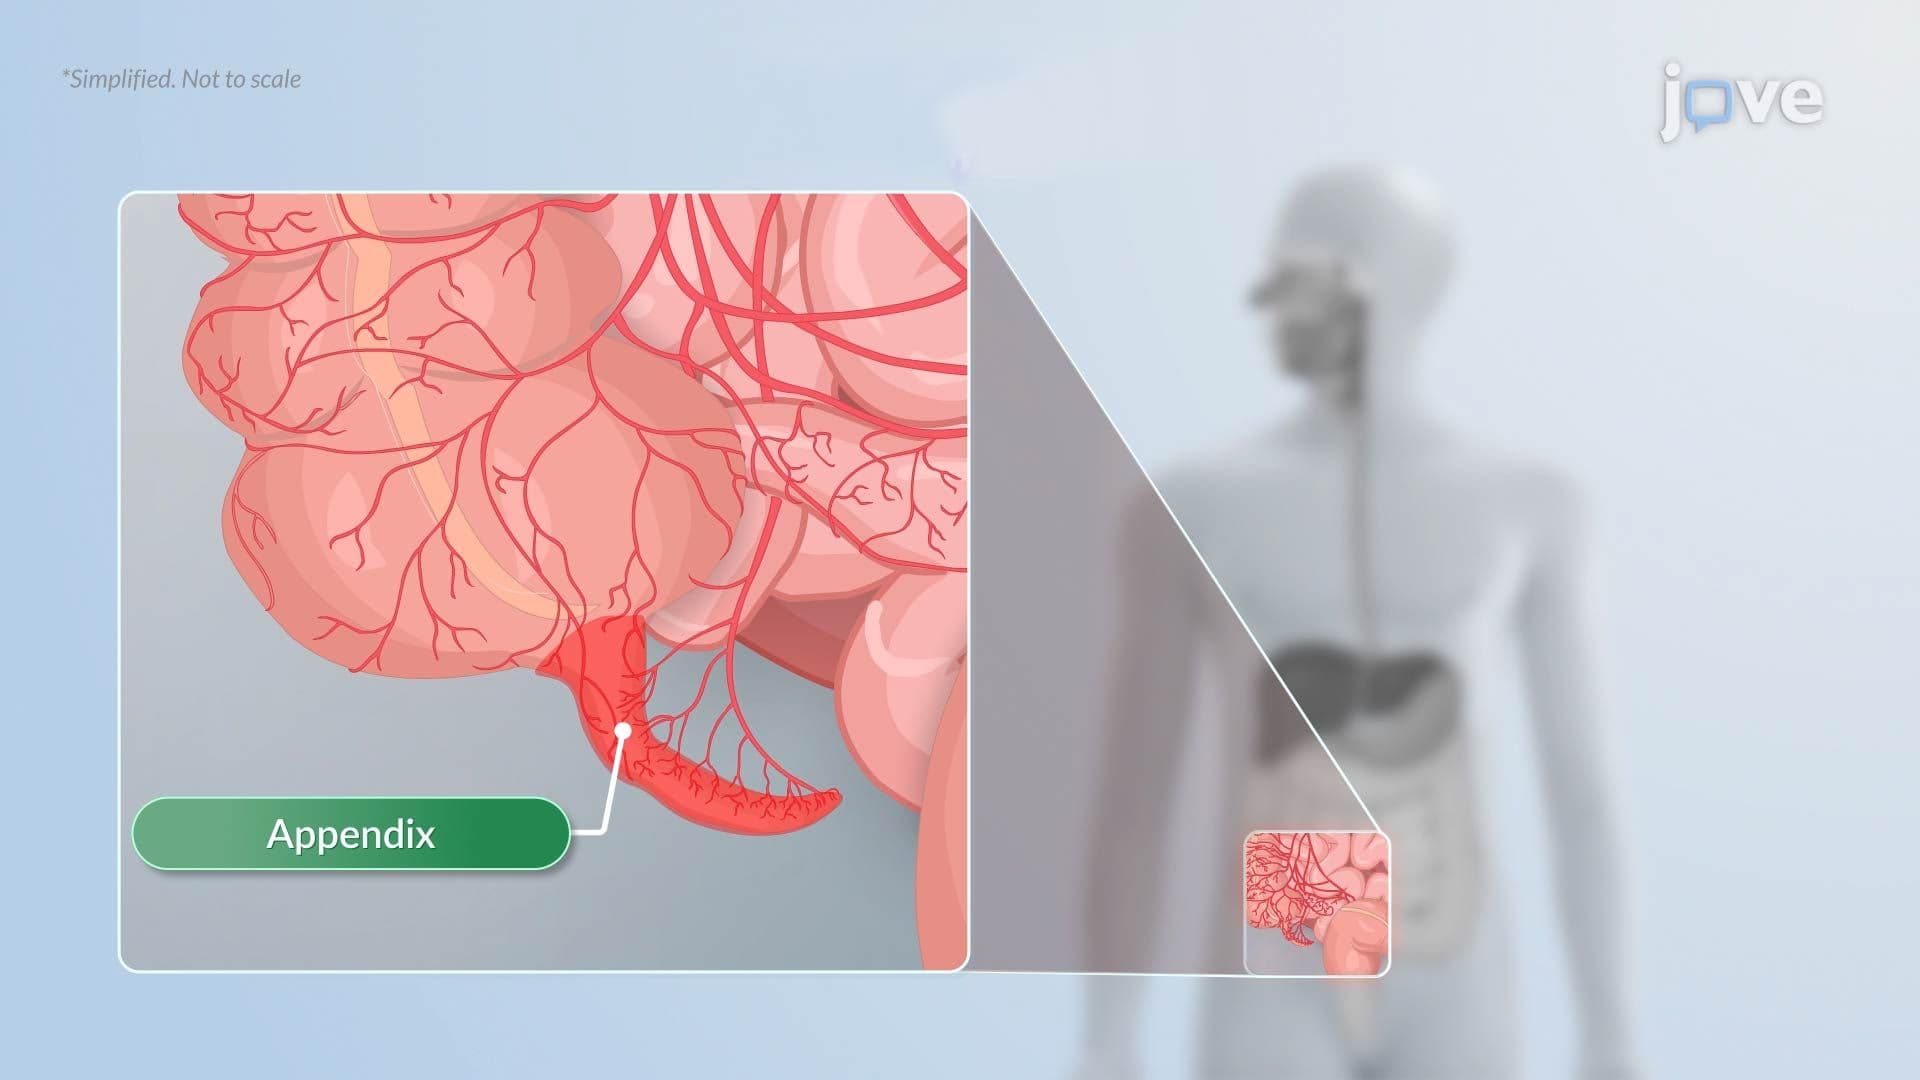
Appendicitis