Related Experiment Video
Updated: Sep 21, 2026


A Battery of Motor Tests in a Neonatal Mouse Model of Cerebral Palsy
Published on: November 3, 2016
BAEPs in infants with myelomeningocele and later development of Chiari II malformation-related brainstem dysfunction
G Worley1, C W Erwin, J M Schuster
1Department of Pediatrics, Duke University Medical Center, Durham, NC 27710.

Insights
Brainstem auditory evoked potentials (BAEPs) in newborns with myelomeningocele can predict future brainstem dysfunction. Abnormal neonatal BAEPs identified infants at higher risk, guiding closer monitoring for early intervention.
Area of Science:
- Neuroscience
- Pediatric Neurology
- Developmental Biology
Background:
- Myelomeningocele is a complex congenital condition affecting neural development.
- Brainstem dysfunction can be a serious complication in infants with myelomeningocele.
- Early identification of neurological risks is crucial for timely intervention.
Purpose of the Study:
- To evaluate the utility of neonatal brainstem auditory evoked potentials (BAEPs) in predicting the subsequent development of brainstem dysfunction in infants with myelomeningocele.
- To determine if abnormal BAEPs in asymptomatic neonates correlate with later neurological complications.
Main Methods:
- Brainstem auditory evoked potentials (BAEPs) were performed on 37 infants with myelomeningocele within the first few days of life.
- Infants were monitored for the development of brainstem dysfunction over a median follow-up period of 30 months.
- BAEP results were analyzed in relation to the subsequent development of clinical symptoms.
Main Results:
- No infant showed brainstem dysfunction at the initial testing.
- 11 out of 12 infants who later developed brainstem dysfunction had abnormal neonatal BAEPs.
- Abnormal BAEPs were observed in 10 out of 25 infants who did not develop brainstem dysfunction, indicating a significant association.
Conclusions:
- Neonatal BAEPs are valuable in identifying asymptomatic infants with myelomeningocele who are at increased risk for developing brainstem dysfunction.
- Abnormal BAEPs, particularly prolonged I-V interpeak latencies, serve as an early indicator for close clinical follow-up.
- This neurophysiological assessment aids in proactive management strategies for infants with myelomeningocele.
Abstract:
Thirty-seven infants with myelomeningocele received brainstem auditory evoked potentials (BAEPs) at a median age of eight days. No infant had brainstem dysfunction at the time of testing. Median follow-up was at 30 months. Of 12 infants who subsequently developed brainstem dysfunction at a median age of three months, 11 had had abnormal neonatal BAEPs. In contrast, only 10 of 25 infants who did not develop brainstem dysfunction had abnormal BAEPs. The mean average I-V interpeak latencies was greater among those who developed symptoms than among those who did not. Neonatal BAEPs can identify a group of asymptomatic infants with myelomeningocele who need close follow-up for the subsequent development of brainstem dysfunction.
More Related Videos


Related Concept Videos
 01:30
Neurulation
 01:19
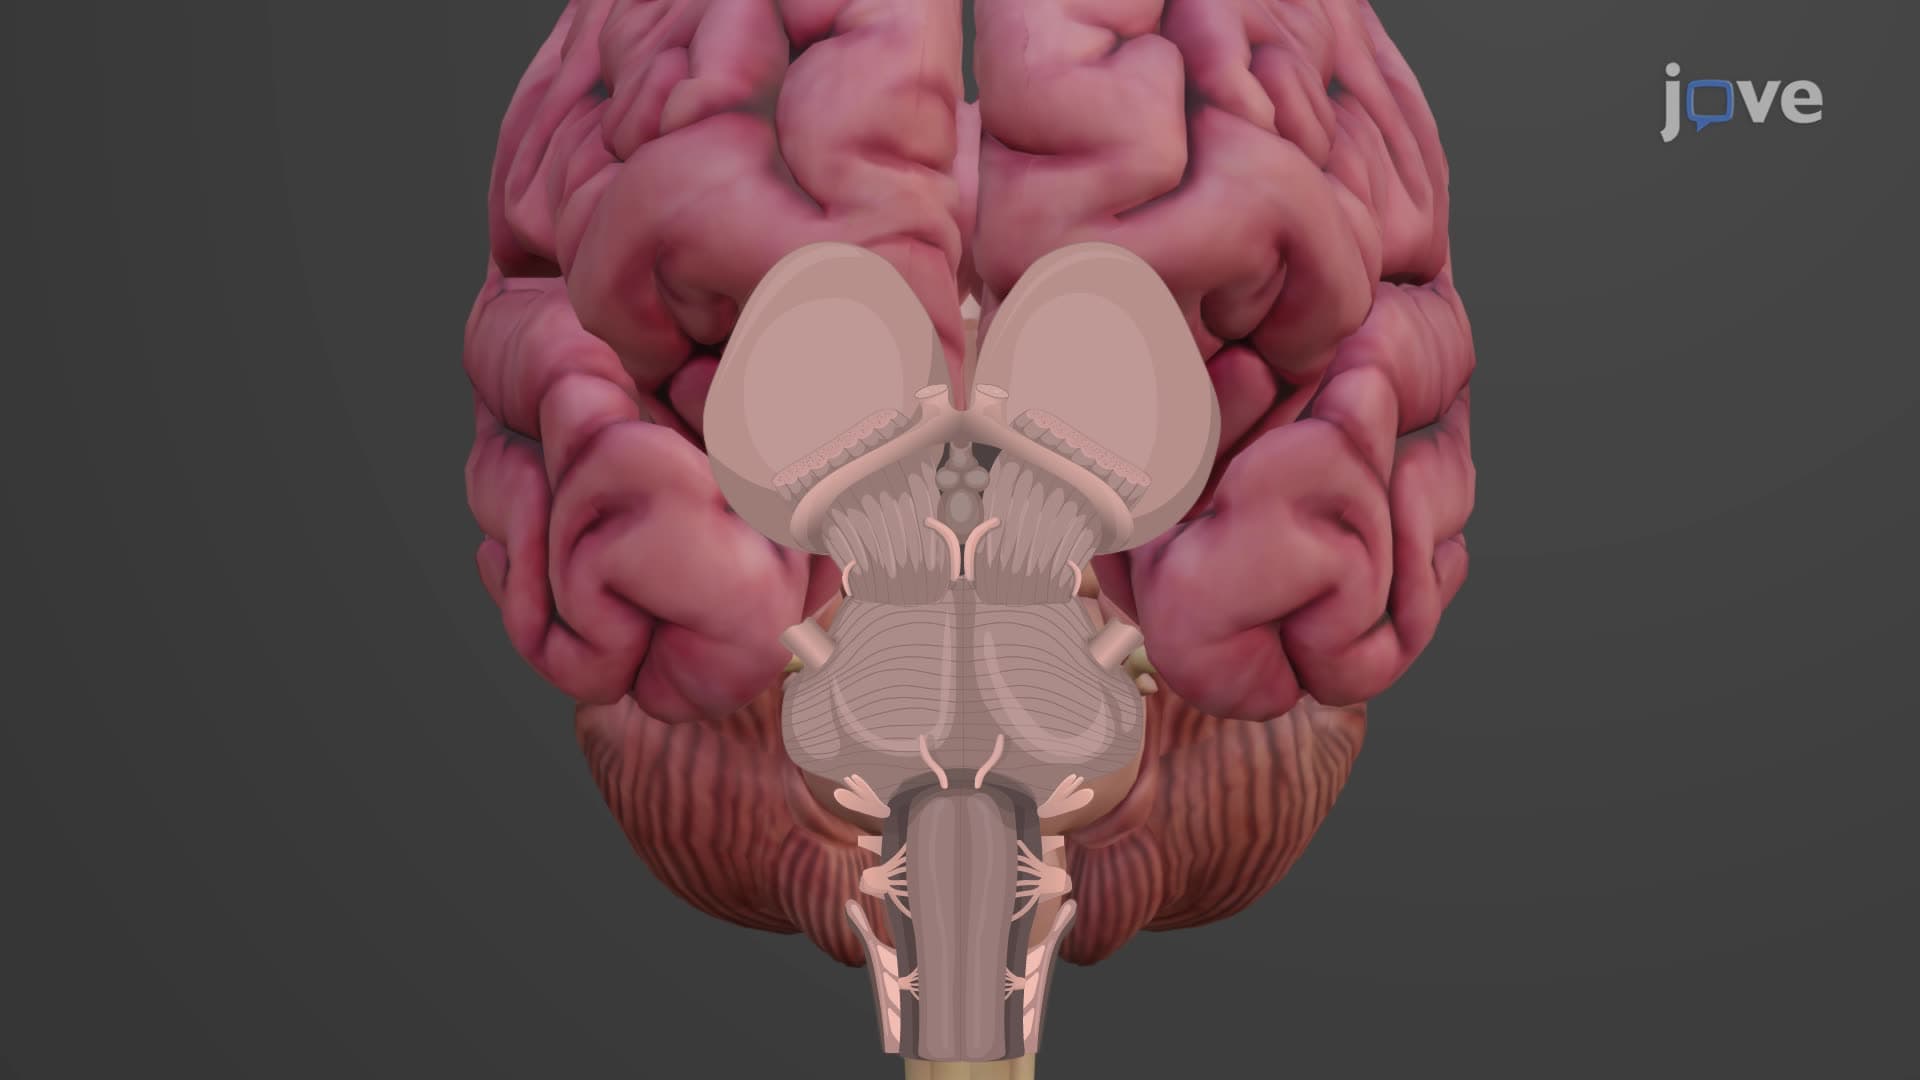
Brainstem
The Midbrain
The midbrain is located beneath the diencephalon and connects the cerebrum with the lower parts of the brain. The cerebral peduncles are prominent midbrain structures that house the...
 01:26
Brain Abscess l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology