Related Experiment Video
Updated: Aug 7, 2026


Electrochemiluminescence Assays for Human Islet Autoantibodies
Published on: March 23, 2018
Serum enzymes in hypothyroidism
J R Burnett1, M J Crooke, J W Delahunt
1Division of Chemical Pathology, Wellington Hospital.

Aim:
To report three cases of hypothyroidism detected because of unexplained elevation of serum enzyme levels on biochemical testing.
Methods:
Clinical details and serum enzyme results were obtained before and after L-thyroxine (T4) replacement therapy.
Results:
The three patients all had serum creatine kinase (CK) levels > 2000 U/L, aspartate aminotransferase (AST) > 90 U/L, and lactate dehydrogenase (LD) > 300 U/L at presentation, with these levels being 10-15, 2-6, and 2-3 times the upper reference limits respectively. CK isoenzyme determination was consistent with skeletal muscle origin. Thyroid function tests performed after consultation with the clinical biochemist confirmed the biochemical diagnosis of primary hypothyroidism. A rapid fall toward normal serum enzyme levels occurred in response to T4 replacement therapy.
Conclusions:
Although serum enzymes are an integral part of both the liver and cardiac profiles provided by laboratory, they are not organ specific, and changes may reflect dysfunction elsewhere in the body. Elevations of serum CK (and other muscle enzymes) may occur in hypothyroid subjects, the cause of which has not been established. The clinical diagnosis of hypothyroidism requires a high index of suspicion and should be considered in patients with unexplained persistent elevations of serum muscle enzymes.


Related Concept Videos
 01:20
Synthesis and Regulation of Thyroid Hormones
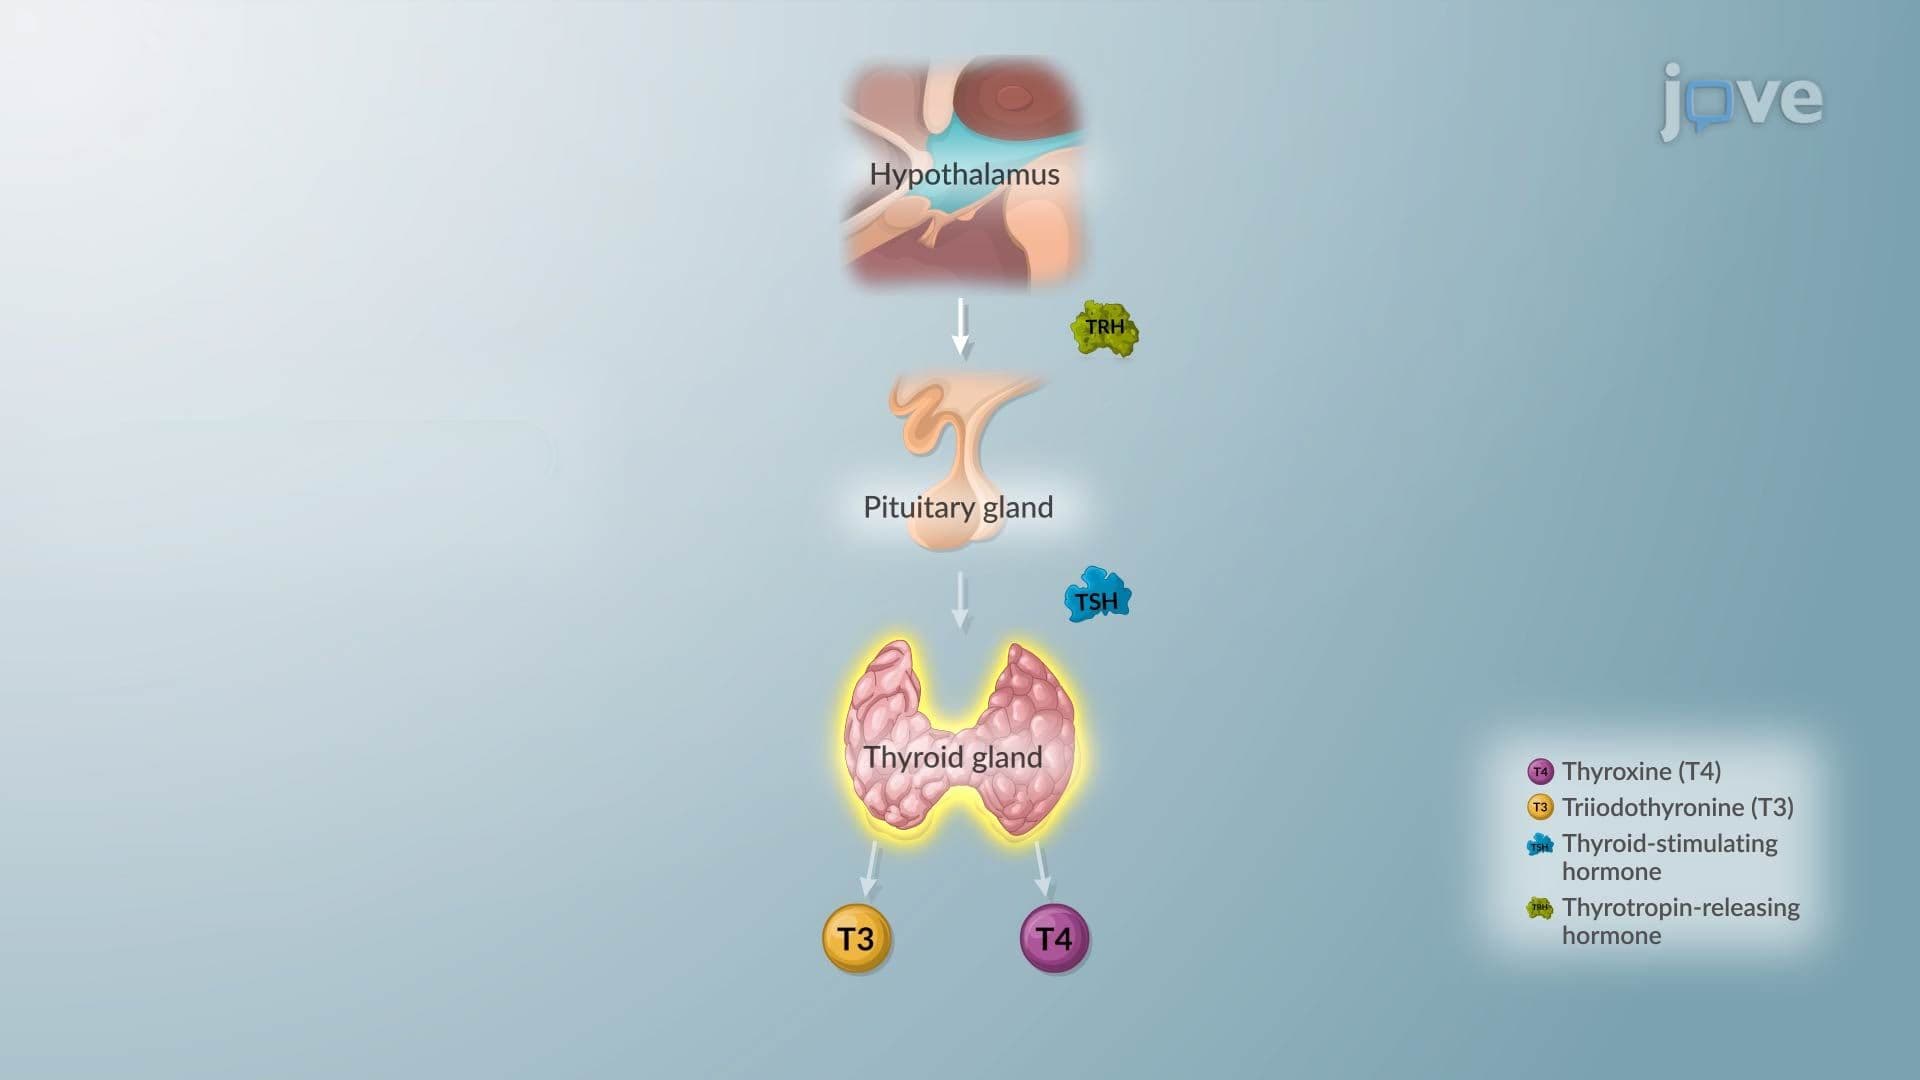
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:24
Serum Studies: Renal Function Tests
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology