Related Experiment Video
Updated: Jul 26, 2026
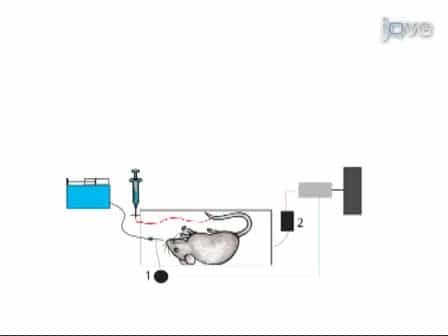
A Reversible, Non-invasive Method for Airway Resistance Measurements and Bronchoalveolar Lavage Fluid Sampling in Mice
Published on: April 14, 2010
The effect of increasing doses of beta-agonists on airflow in patients with chronic airflow limitation
R Jaeschke1, G H Guyatt, D Cook
1Department of Medicine, McMaster University, Hamilton, Ontario, Canada.

Objective:
To determine the increase in FEV1 associated with increasing doses of inhaled terbutaline and salbutamol, the reproducibility of the increase in FEV1, and the reproducibility of the associated optimal bronchodilator dose, in patients with chronic airflow limitation (CAL).
Design:
Double-blind, randomized, controlled trial examining spirometric response to cumulative doses of bronchodilators.
Patients And Setting:
Patients with clinical diagnosis of CAL, FEV1 below 70% predicted, and FEV1 to FVC ratio less than 0.7 after administration of bronchodilator recruited from secondary care respirology practices.
Measures Of Outcome:
The estimates of maximum and optimal bronchodilation, as well as the associated drug dosages, were established in each patient on three occasions (twice on terbutaline and once on salbutamol). The 'optimal' drug dose was defined as the lowest dose associated with an FEV1 not exceeded by 50 ml on any other dose.
Main Results:
Thirty-five patients completed the trial. FEV1 improved from 0.93 to a maximum of 1.191 with terbutaline (average of the two administrations) and from 0.951 to 1.141 with inhaled salbutamol (difference in increase in FEV1 between terbutaline and salbutamol P = 0.006). In less than 50% of cases administration of more than four puffs of bronchodilator resulted in FEV1 increase by more than 50 ml. The average dose of salbutamol and terbutaline associated with optimal bronchodilation were 430 micrograms and 1160 micrograms respectively. Patients varied widely in the optimal dose. Estimates of optimal dose were not reproducible (intraclass correlation coefficient < 0.5).
Conclusion:
Substantial incremental increase in FEV1 in response to increasing doses of beta-agonists beyond those commonly used in clinical practice is restricted to a minority of patients. Lack of reproducibility limits the clinical usefulness of establishing the optimal dose of beta-agonist for a given patient.

Related Concept Videos
 01:17
Drugs Used in Lower Respiratory Disorders: Overview
Bronchodilators, the first step of respiration enhancement, come in various forms, each with its own mechanism...
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features