Related Experiment Video
Updated: Aug 14, 2026

Long-term Behavioral and Reproductive Consequences of Embryonic Exposure to Low-dose Toxicants
Published on: March 6, 2018
Dose-effect and dose-response relationships for lead in children

Insights
Chelatable lead levels, not blood lead, better predict adverse effects on hemoglobin synthesis in children. Erythrocyte protoporphyrin is a practical indicator for monitoring lead poisoning risk.
Area of Science:
- Toxicology
- Environmental Health
- Pediatrics
Background:
- Lead absorption can cause serious health effects, particularly in children.
- Understanding dose-effect and dose-response relationships is crucial for lead poisoning prevention.
- Identifying the critical organ and critical effect guides early intervention strategies.
Purpose of the Study:
- To re-examine lead absorption and prevention strategies using critical organ and clinical effect concepts.
- To evaluate the predictive value of blood lead levels versus chelatable lead for adverse effects.
- To assess the utility of dose-response relationships in understanding lead toxicity.
Main Methods:
- Analysis of dose-effect and dose-response relationships in lead absorption.
- Evaluation of blood lead values as predictors of critical effects.
- Assessment of chelatable lead and its correlation with hemoglobin synthesis indicators.
- Comparison of dose-response concepts with traditional screening test evaluations.
Main Results:
- Blood lead levels (50-80 mug/dl) are poor predictors of critical effects in pediatric lead absorption.
- Chelatable lead shows a significant linear relationship with critical effects on bone marrow hemoglobin synthesis.
- Erythrocyte protoporphyrin, delta-aminolevulinic acid, and urinary coproporphyrin indicate these critical effects.
- The dose-response concept offers a superior framework for understanding lead's adverse effects compared to sensitivity/specificity metrics.
Conclusions:
- Chelatable lead is a more reliable indicator than blood lead for assessing lead's impact on hemoglobin synthesis.
- Erythrocyte protoporphyrin is a practical biomarker for monitoring children at risk of lead poisoning (plumbism).
- The dose-response model better accounts for individual variability in lead toxicity.
Abstract:
Lead absorption and prevention of the serious effects of lead re-examined from the viewpoints of the critical organ and clinical effect concepts and the associated dose-effect and dose-response relationships. If the critical organ is the first affected and the critical effect is the first measurable adverse effect, intervention on this basis should prevent the occurrence of later, more serious effects. In the range of lead absorption of greatest current pediatric concern (blood lead in the range of 50 to 80 mug/dl), blood lead values are not a good predictor of critical effect, whereas chelatable lead is significantly and linearly related to evidence of critical effect on hemoglobin synthesis in the bone marrow. Erythrocyte protoporphyrin and delta-aminolevulinic acid and coproporphyrin in urine are indicators of this effect. The dose-response concept provides a better way of viewing the relationship between blood lead and measures of adverse effect than do the classifications of "sensitivity," "specificity", "false negatives," and "false positives," which are often employed in the evaluation of screening tests. The dose-response concept recognizes the uniqueness of the individual and the presence of susceptible and resistant individuals in heterogeneous population groups. With the dose-response concept, individuals may be identified as reactors or nonreactors, according to whether they exhibit a particular effect. Among the various indicators of lead's critical (or first) effect on hemoglobin synthesis, erythrocyte protoporphyrin potentially is the most practical for monitoring children at high risk for plumbism.
More Related Videos


Related Concept Videos
 01:21
Factors Affecting Drug Response: Overview
 01:03
Dose-Response Relationship: Overview
 01:29
Drug Dosing: Infants and Children
 01:14
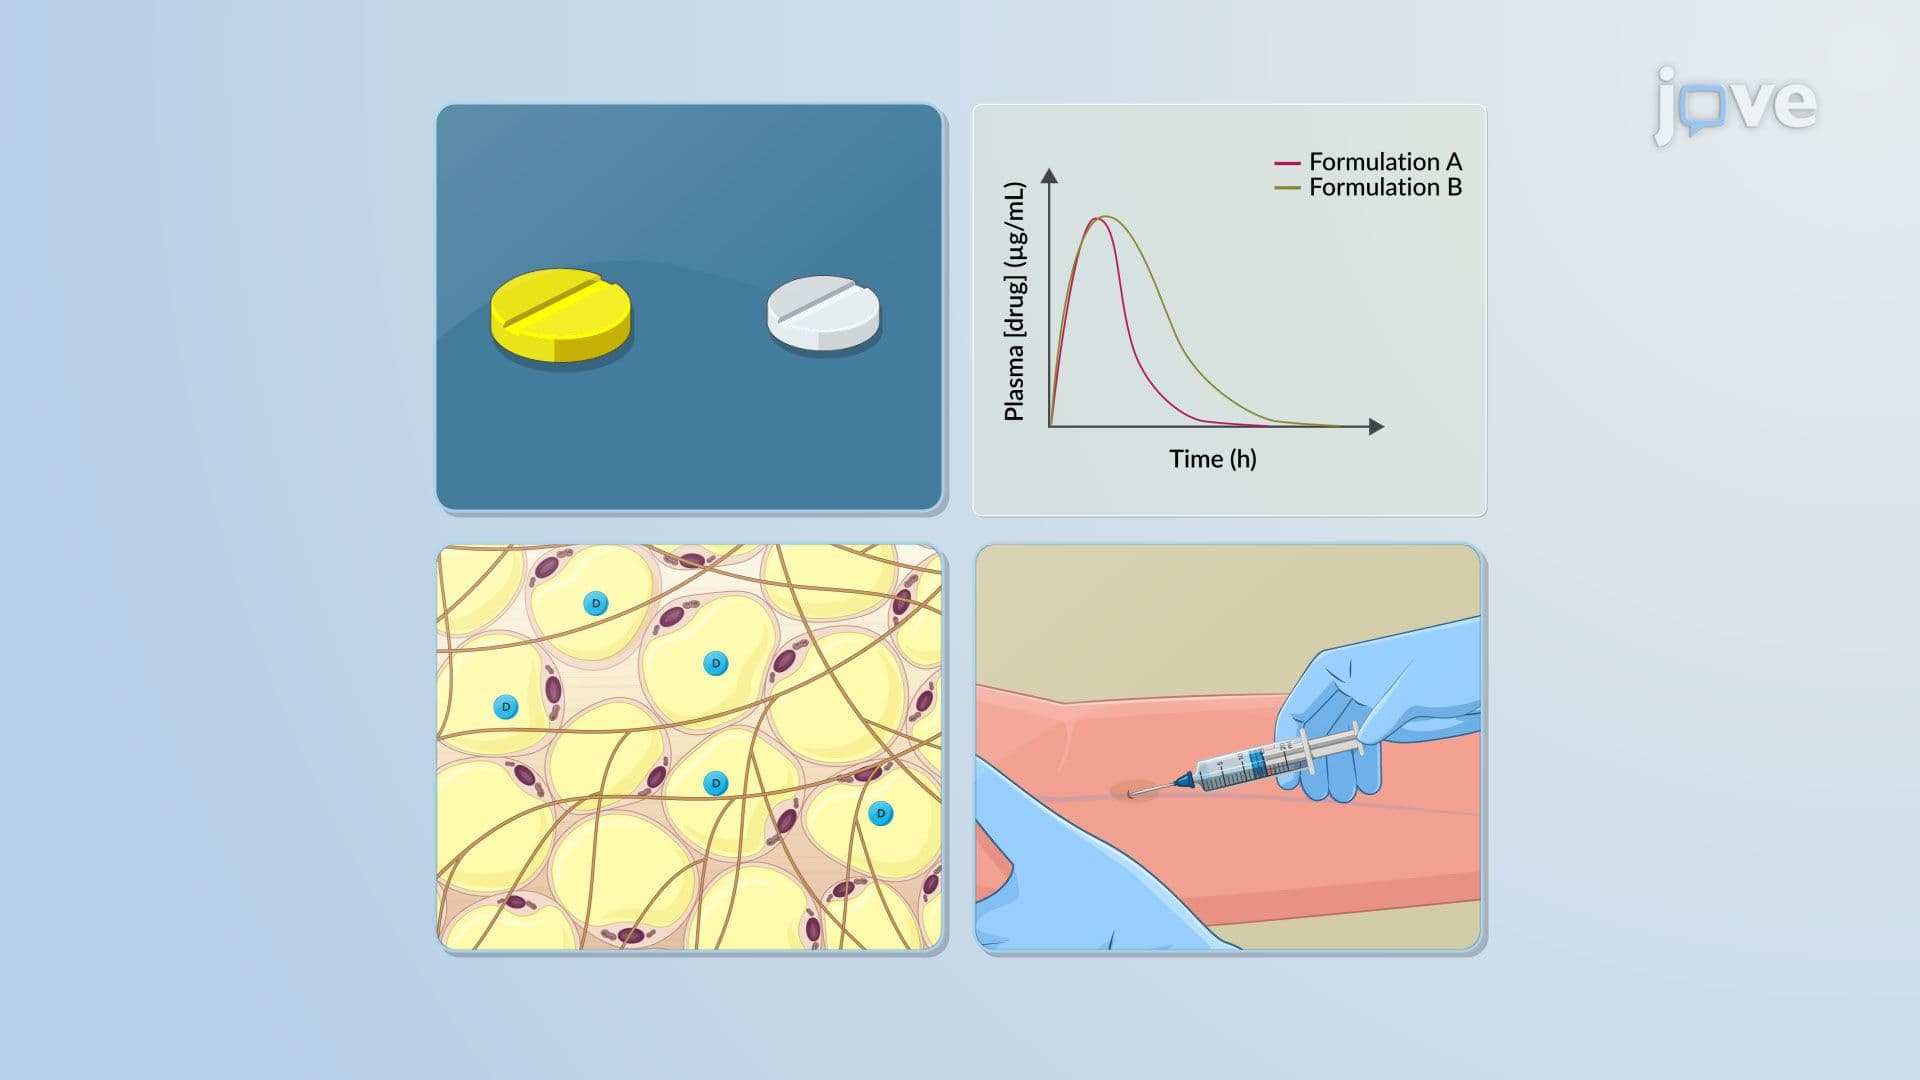
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship
 01:23
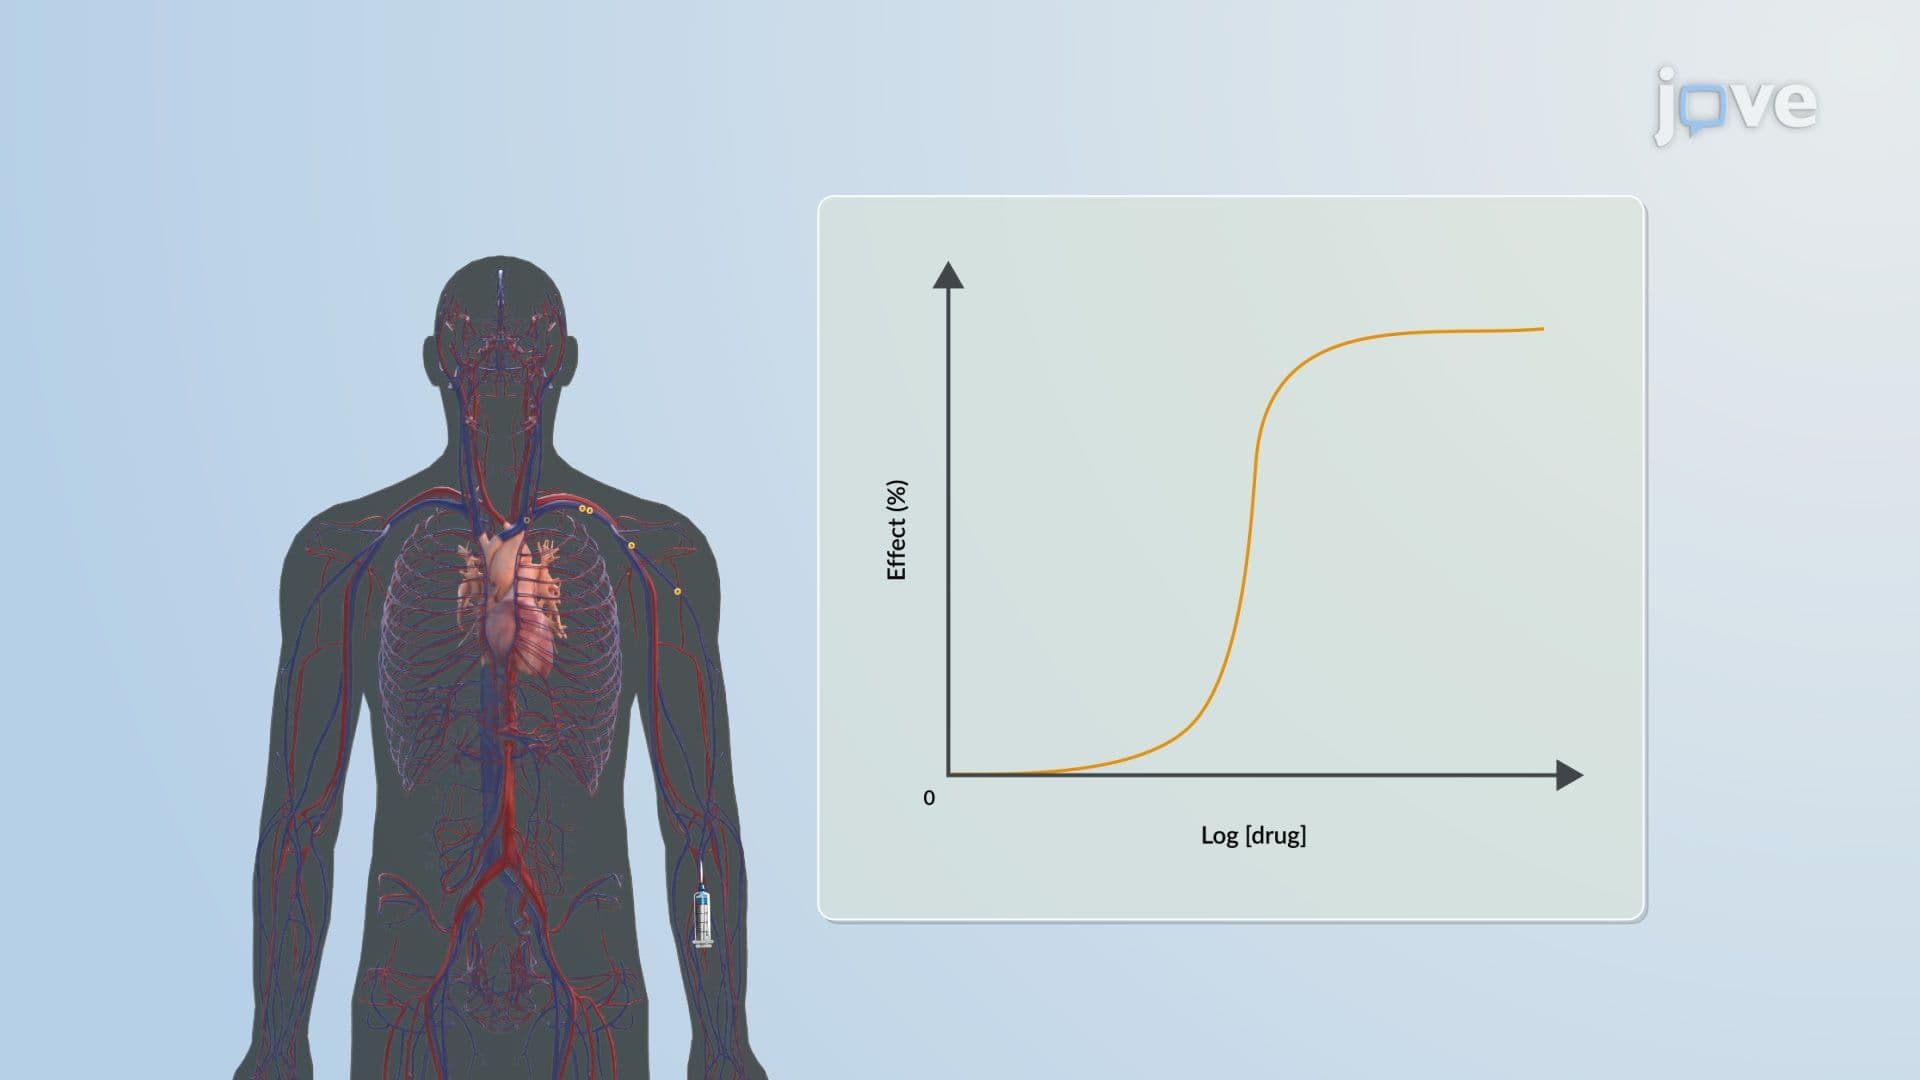
Pharmacokinetic–Pharmacodynamic Relationship: Intensity of Dose-Effect Relationship
 01:21
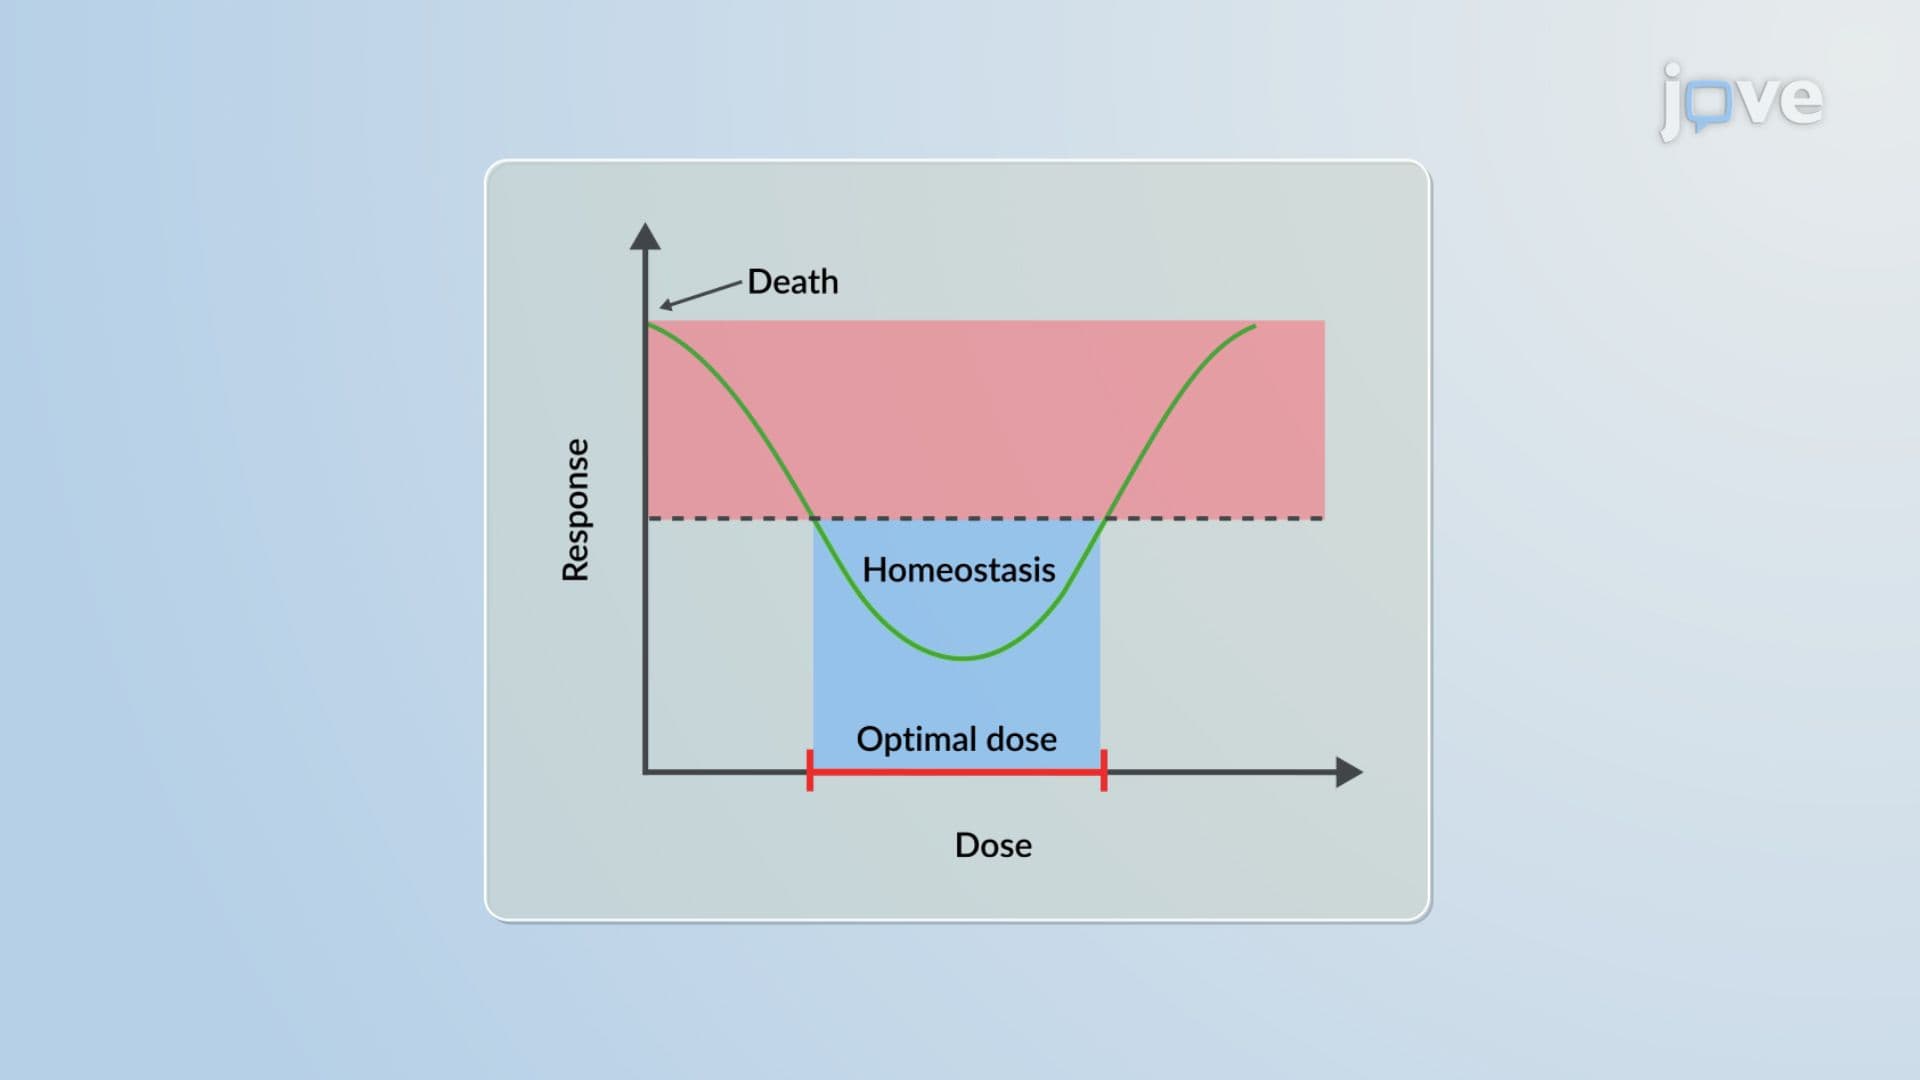
Dose Response Curve: Conventional Versus Nonmonotonic