Related Experiment Video
Updated: Sep 24, 2026
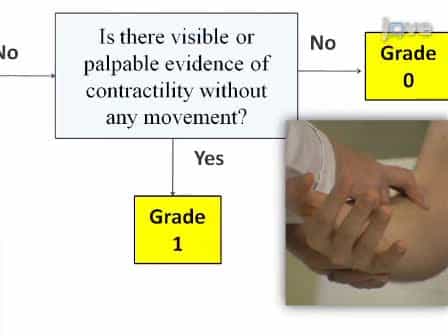

Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
The use of neuromuscular blocking drugs in the intensive care unit: a US perspective
M J Murray1, R A Strickland, C Weiler
1Mayo Clinic, Rochester, Minnesota.

Surprisingly little is known about the use of neuromuscular blockers (NMBs) in intensive care units (ICUs) in the USA. Recently, Klessig et al. surveyed anesthesiologists/intensivists in the USA and found that the 55% who responded used NMBs in the ICU in an average of 10 patients per ICU per month. Anxiolytics and analgesics were administered concomitantly with NMBs, but a majority of respondents did not use electrophysiologic measures of the degree of blockade. Another survey of predominantly medical ICUs also demonstrated widespread use of NMBs, but internists did not use sedation/analgesia as frequently as anesthesiologists for patients receiving NMBs, and infrequently monitored the degree of neuromuscular blockade. Because these were retrospective surveys, we decided to monitor prospectively the use of NMBs in our ICUs. The use of NMBs was ascertained by daily review of pharmacy records and, when use was documented, the patients' hospital records were reviewed. Where information was missing or not found, attending physicians were interviewed. On average, one patient per month per ICU received NMBs. Approximately 5% of neonatal and pediatric, and 1% of adult, ICU patients received NMBs. Eighty-three percent of patients received NMBs to facilitate mechanical ventilation, and mortality was high (51%) in those critically ill patients. More than half the patients were treated for < or = 24 h, the remainder for 2 days to > 3 weeks. Twitch monitors were used for monitoring the degree of neuromuscular blockade in adult patients, and all patients received sedatives/analgesics. We estimated that the risk of clinically significant, prolonged neuromuscular blockade following the discontinuation of NMBs was 5% per year.(ABSTRACT TRUNCATED AT 250 WORDS)
Surprisingly little is known about the use of neuromuscular blockers (NMBs) in intensive care units (ICUs) in the USA. Recently, Klessig et al. surveyed anesthesiologists/intensivists in the USA and found that the 55% who responded used NMBs in the ICU in an average of 10 patients per ICU per month. Anxiolytics and analgesics were administered concomitantly with NMBs, but a majority of respondents did not use electrophysiologic measures of the degree of blockade. Another survey of predominantly medical ICUs also demonstrated widespread use of NMBs, but internists did not use sedation/analgesia as frequently as anesthesiologists for patients receiving NMBs, and infrequently monitored the degree of neuromuscular blockade. Because these were retrospective surveys, we decided to monitor prospectively the use of NMBs in our ICUs. The use of NMBs was ascertained by daily review of pharmacy records and, when use was documented, the patients' hospital records were reviewed. Where information was missing or not found, attending physicians were interviewed. On average, one patient per month per ICU received NMBs. Approximately 5% of neonatal and pediatric, and 1% of adult, ICU patients received NMBs. Eighty-three percent of patients received NMBs to facilitate mechanical ventilation, and mortality was high (51%) in those critically ill patients. More than half the patients were treated for < or = 24 h, the remainder for 2 days to > 3 weeks. Twitch monitors were used for monitoring the degree of neuromuscular blockade in adult patients, and all patients received sedatives/analgesics. We estimated that the risk of clinically significant, prolonged neuromuscular blockade following the discontinuation of NMBs was 5% per year.(ABSTRACT TRUNCATED AT 250 WORDS)
More Related Videos
 06:04
Objective Nociceptive Assessment in Ventilated ICU Patients: A Feasibility Study Using Pupillometry and the Nociceptive Flexion Reflex
Published on: July 4, 2018
 09:36
Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
Related Concept Videos
 01:17
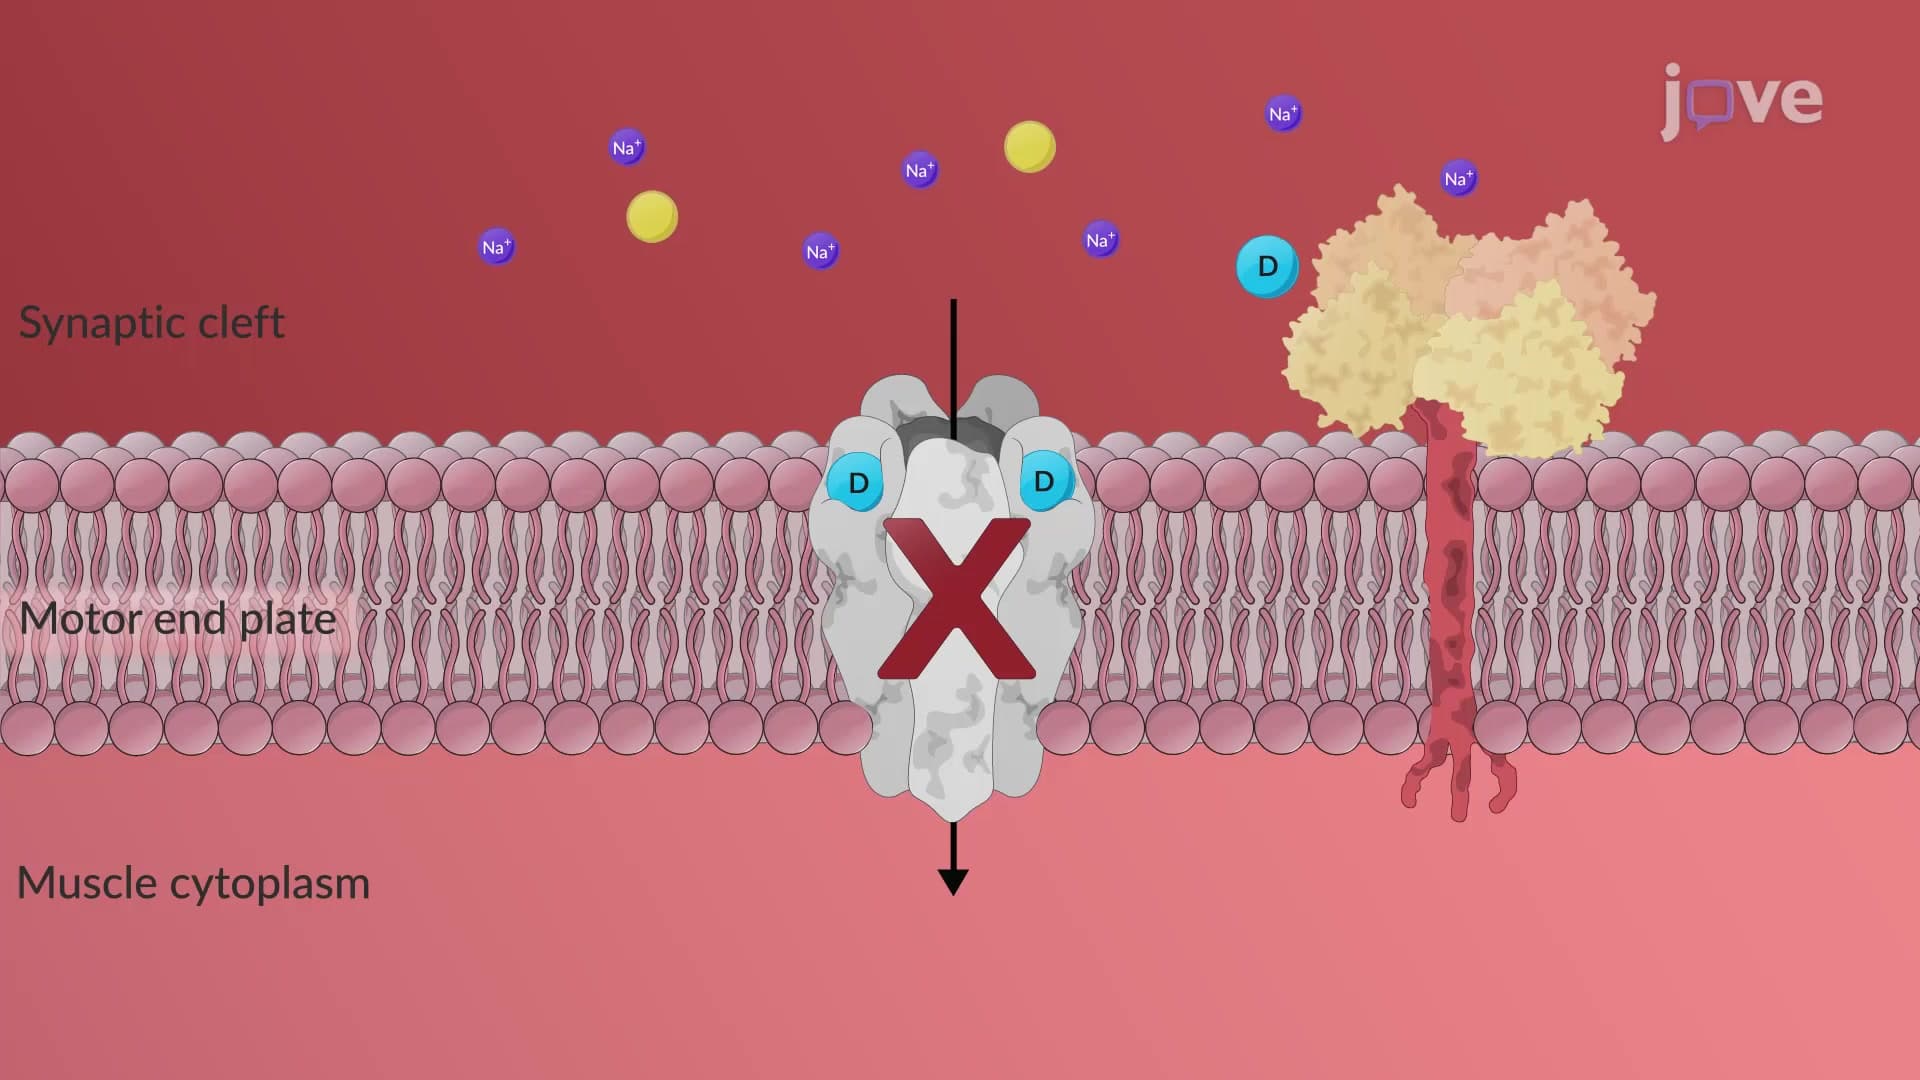
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:11
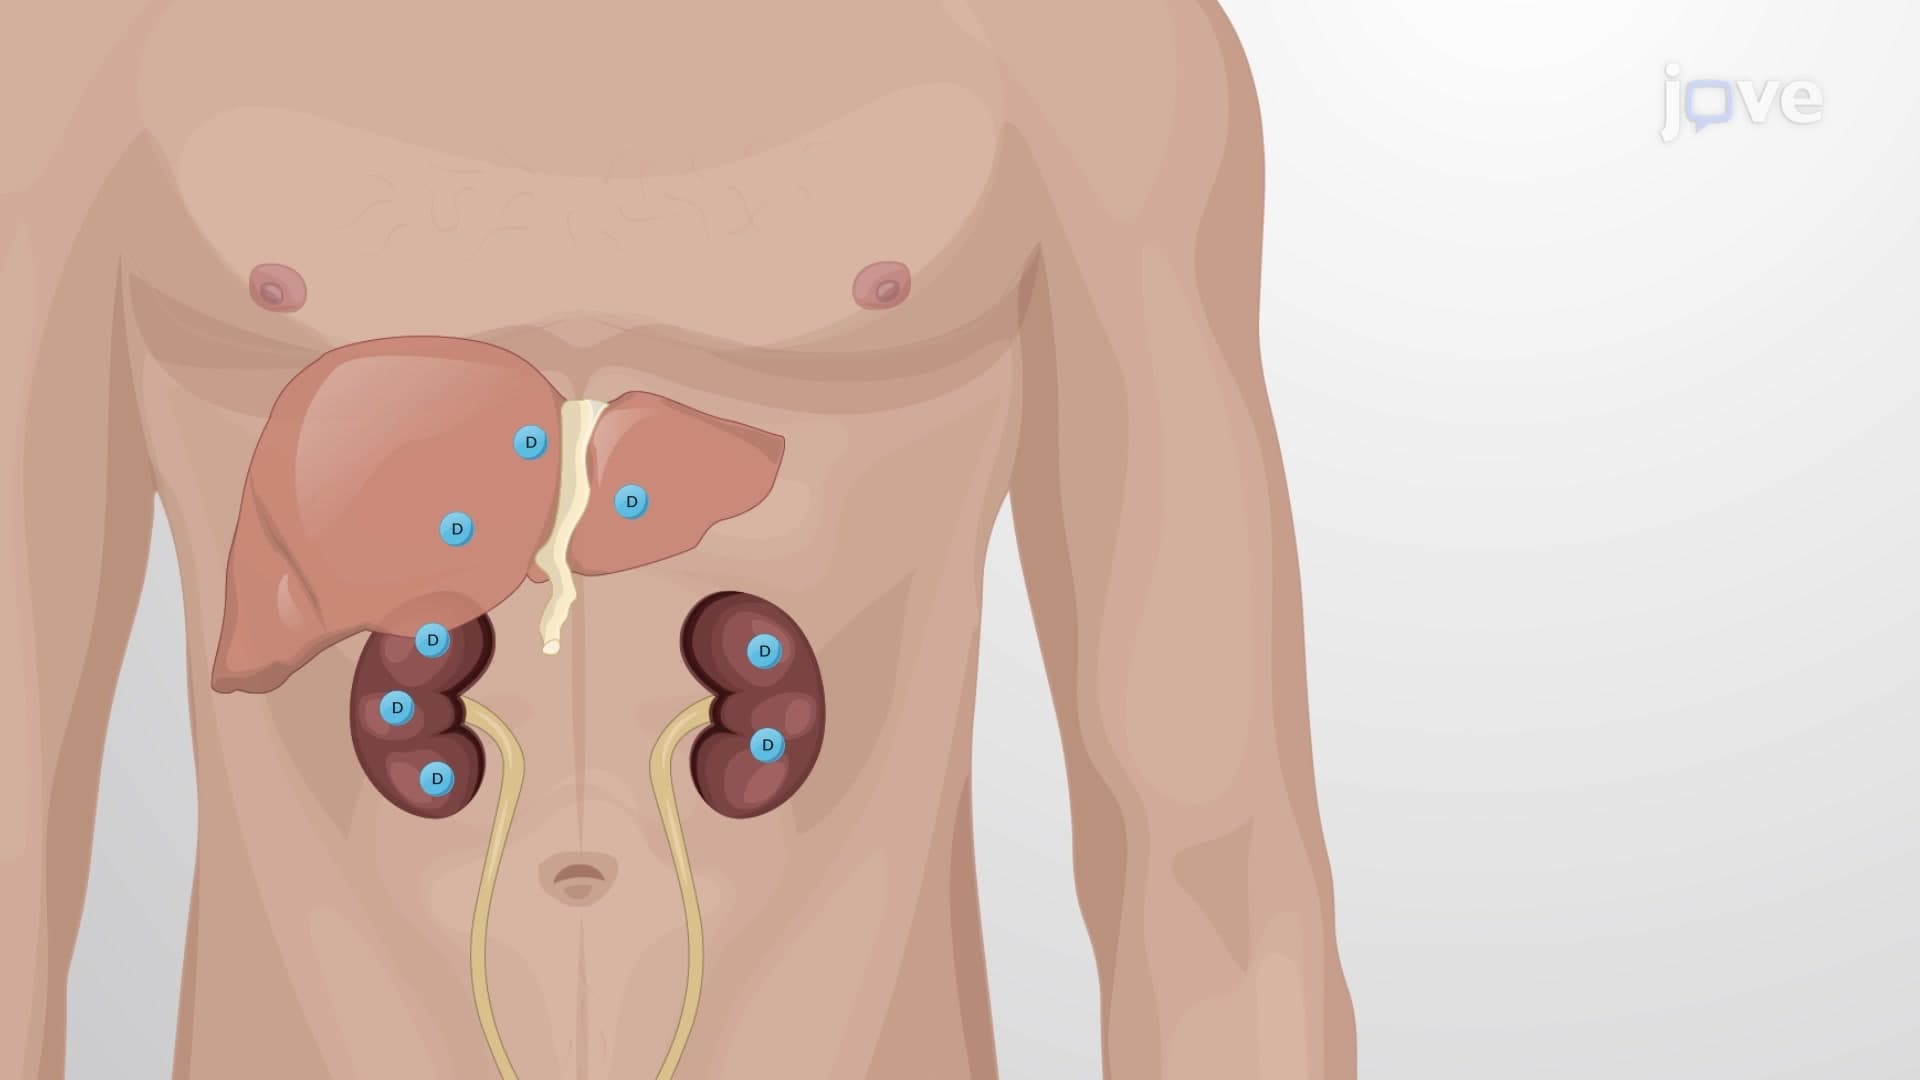
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:28
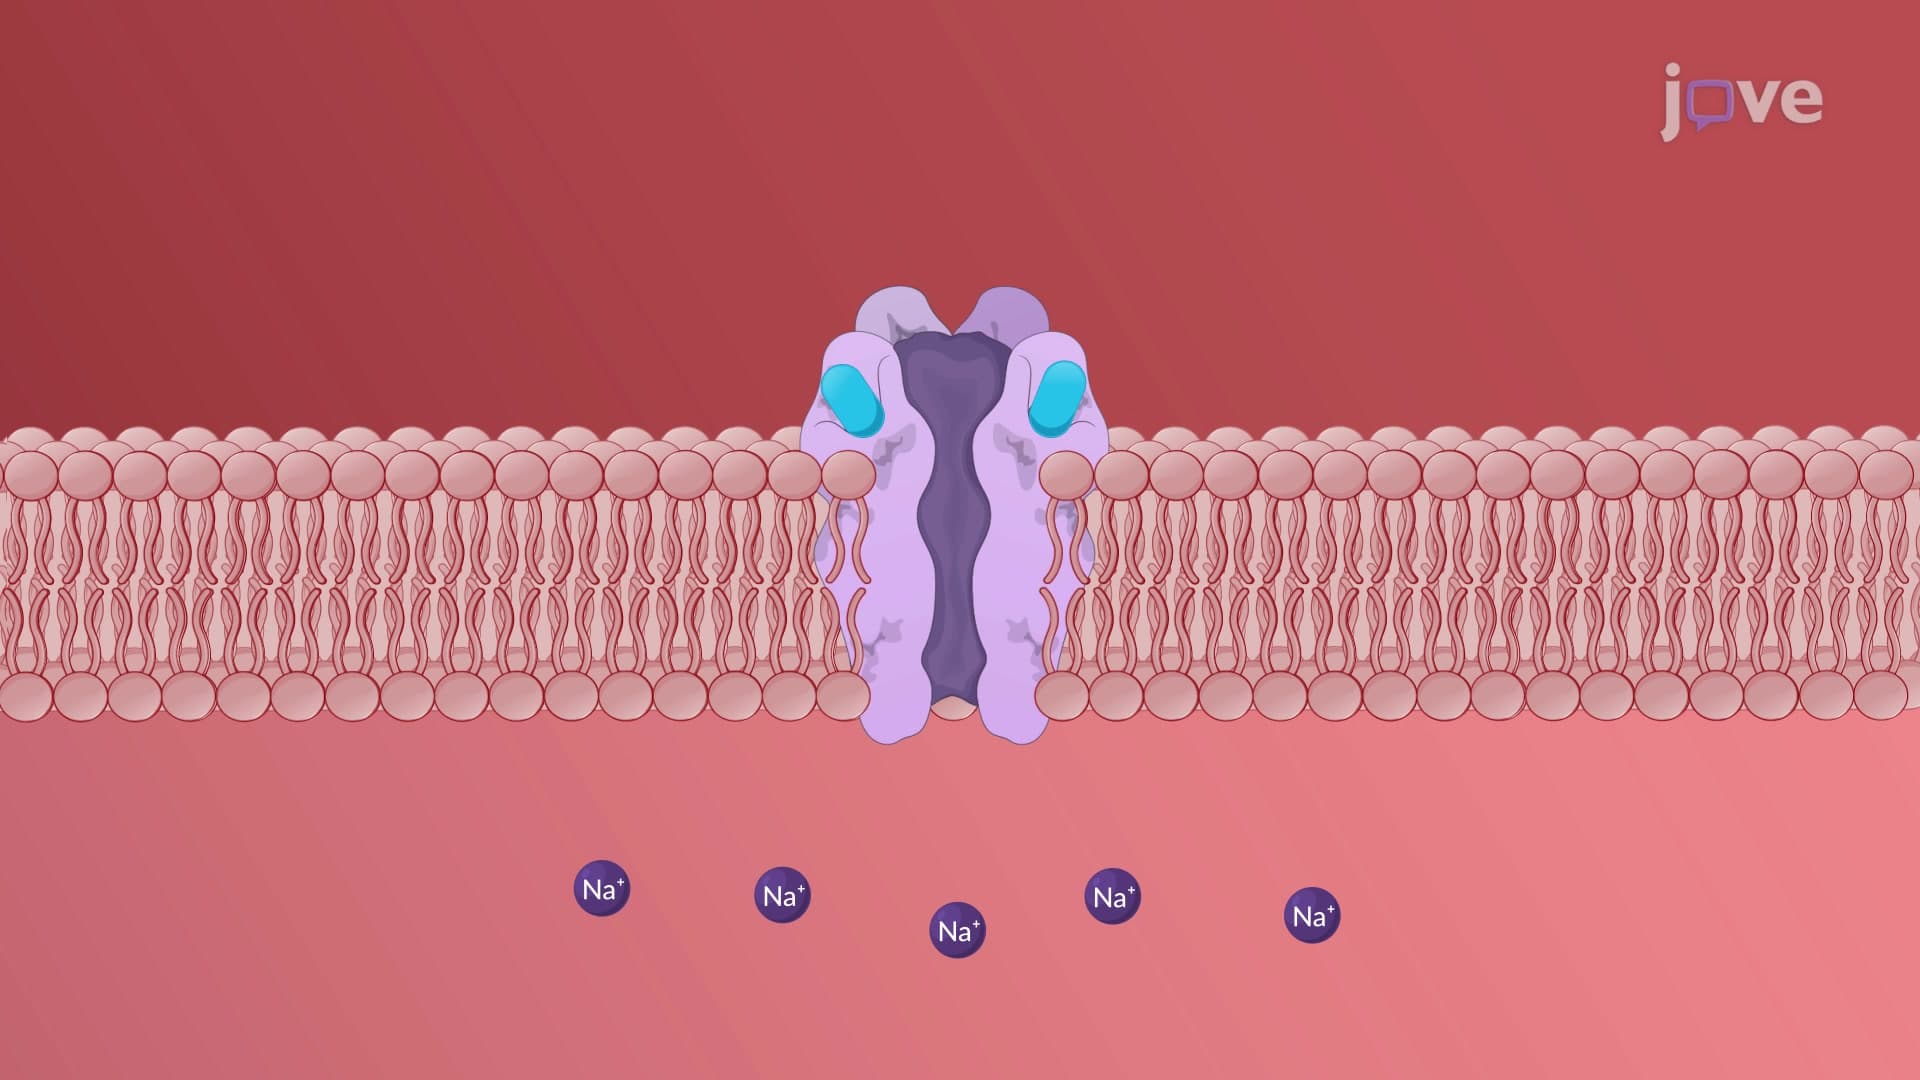
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses