Differential excretion of urinary proteins in children with vesicoureteric reflux and reflux nephropathy
Related Experiment Video
Updated: Aug 12, 2026
A Modified Precipitation Method to Isolate Urinary Exosomes
Published on: January 16, 2015
P A Tomlinson1, J M Smellie, N Prescod
1Evelina Children's Unit, Guy's Hospital, United Medical and Dental School, London, UK.

Insights
Children with renal scarring show elevated urine retinol-binding protein (RBP) and N-acetyl-beta-D-glucosaminidase (NAG) levels, indicating tubular dysfunction. This dysfunction is more common in bilateral scarring and may precede glomerular damage.
Area of Science:
- Pediatric Nephrology
- Urology
- Biochemistry
Background:
- Vesicoureteric reflux (VUR) is a common condition in children.
- Renal scarring can result from VUR and may lead to long-term kidney damage.
- Biomarkers for early detection of kidney damage in VUR are needed.
Purpose of the Study:
- To investigate urinary biomarkers for renal tubular and glomerular dysfunction in children with VUR.
- To correlate biomarker levels with the presence and severity of renal scarring.
Main Methods:
- Measured urine retinol-binding protein (RBP), albumin, and N-acetyl-beta-D-glucosaminidase (NAG) in children with and without VUR-related renal scarring.
- Analyzed biomarker levels in relation to VUR history, presence of renal scarring (unilateral vs. bilateral), and severity of reflux.
- Assessed glomerular filtration rate (GFR) and its correlation with RBP excretion.
Main Results:
- Urinary RBP and NAG levels were significantly elevated in children with renal scarring (P < 0.001).
- Elevated RBP was more frequent in bilateral scarring (51%) than unilateral scarring (7%).
- Tubular dysfunction markers (RBP, NAG) were elevated, particularly in bilateral scarring and severe reflux, often preceding albuminuria.
Conclusions:
- Tubular dysfunction is common in children with bilateral renal scarring due to VUR.
- Elevated urinary RBP and NAG suggest tubular damage that may precede glomerular dysfunction.
- These biomarkers could aid in monitoring kidney health in children with VUR and renal scarring.
Abstract:
We studied 40 children with a history of vesicoureteric reflux (VUR) without evidence of renal scarring, 93 children with a history of VUR and renal scarring and 10 children with previous urinary tract infections in whom the urinary tract was radiologically normal. Urine retinol-binding protein (RBP), albumin and N-acetyl-beta-D-glucosaminidase (NAG) were measured in each child. All were free from infection at the time of the analysis. Urinary RBP and NAG levels were significantly elevated (P < 0.001) in the group of children with renal scarring. Elevated RBP levels were detected in 51% of children with bilateral renal scarring compared with 7% of children with unilateral scarring. Urine RBP excretion increased progressively according to the type of scarring, best determined by the type of scarring of the less affected kidney. In children with renal scarring, elevated NAG levels were seen mostly in the 65 children with bilateral scarring and severe reflux. Urine albumin excretion was elevated in 10 children, 9 with bilateral scarring, all of whom had elevated RBP excretion. Urine protein excretion was unaffected by the presence or absence of persisting VUR. There was a strong negative correlation between glomerular filtration rate and RBP excretion (r = -0.69). We conclude that evidence of tubular dysfunction is common in children with bilateral renal scarring and usually precedes any glomerular protein leak. Tubular dysfunction may be the consequence of relative nephron hyperperfusion in the presence of bilateral scarring.

Related Concept Videos
 01:32
Filtration and Urine Formation
 01:02
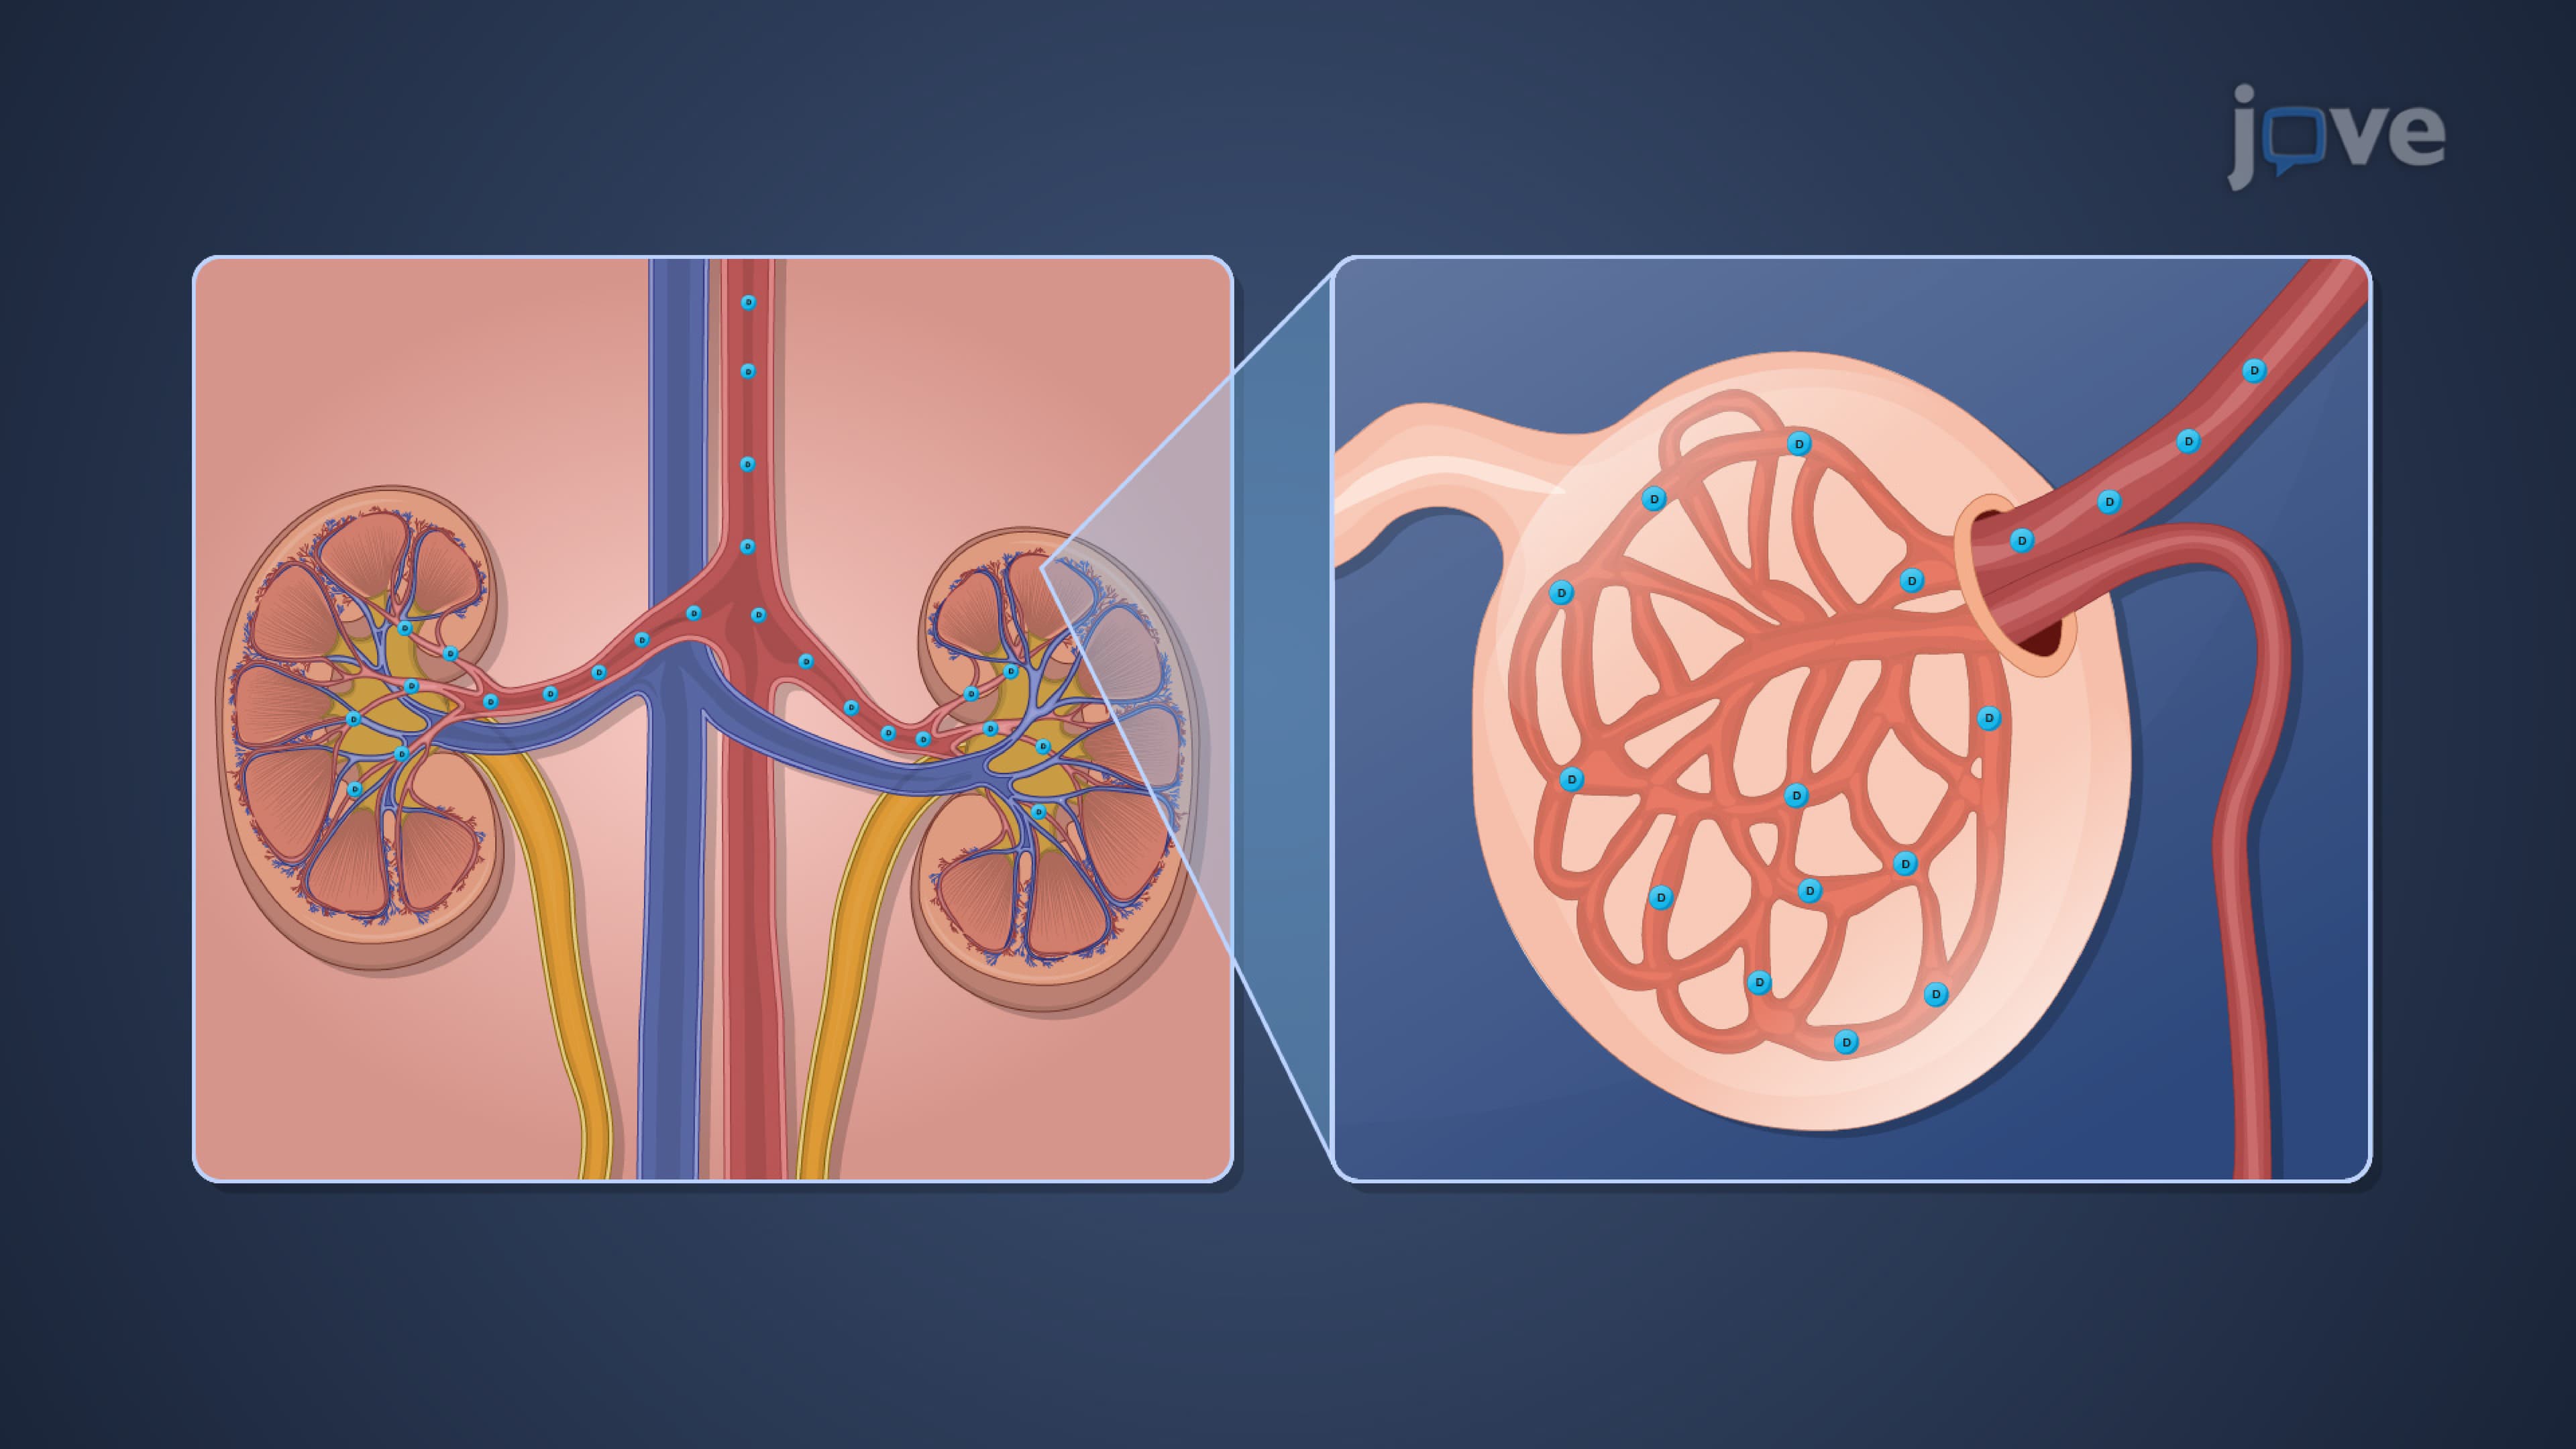
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles.
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:29
Physiology of the Genitourinary System I: Renal Blood Flow and Glomerular Filtration
 01:22
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion
 01:26
Nephrotic Syndrome II : Assessment and Medical Management