Severe hyponatraemia in a quadriplegic

C J Gibbs1, H A Lee

  • 1Department of Renal Medicine (University of Southampton), St Mary's Hospital, Portsmouth.

The British Journal of Clinical Practice
|January 1, 1994
PubMed

Related Concept Videos

Increased Intracranial Pressure l: Introduction01:14

Increased Intracranial Pressure l: Introduction
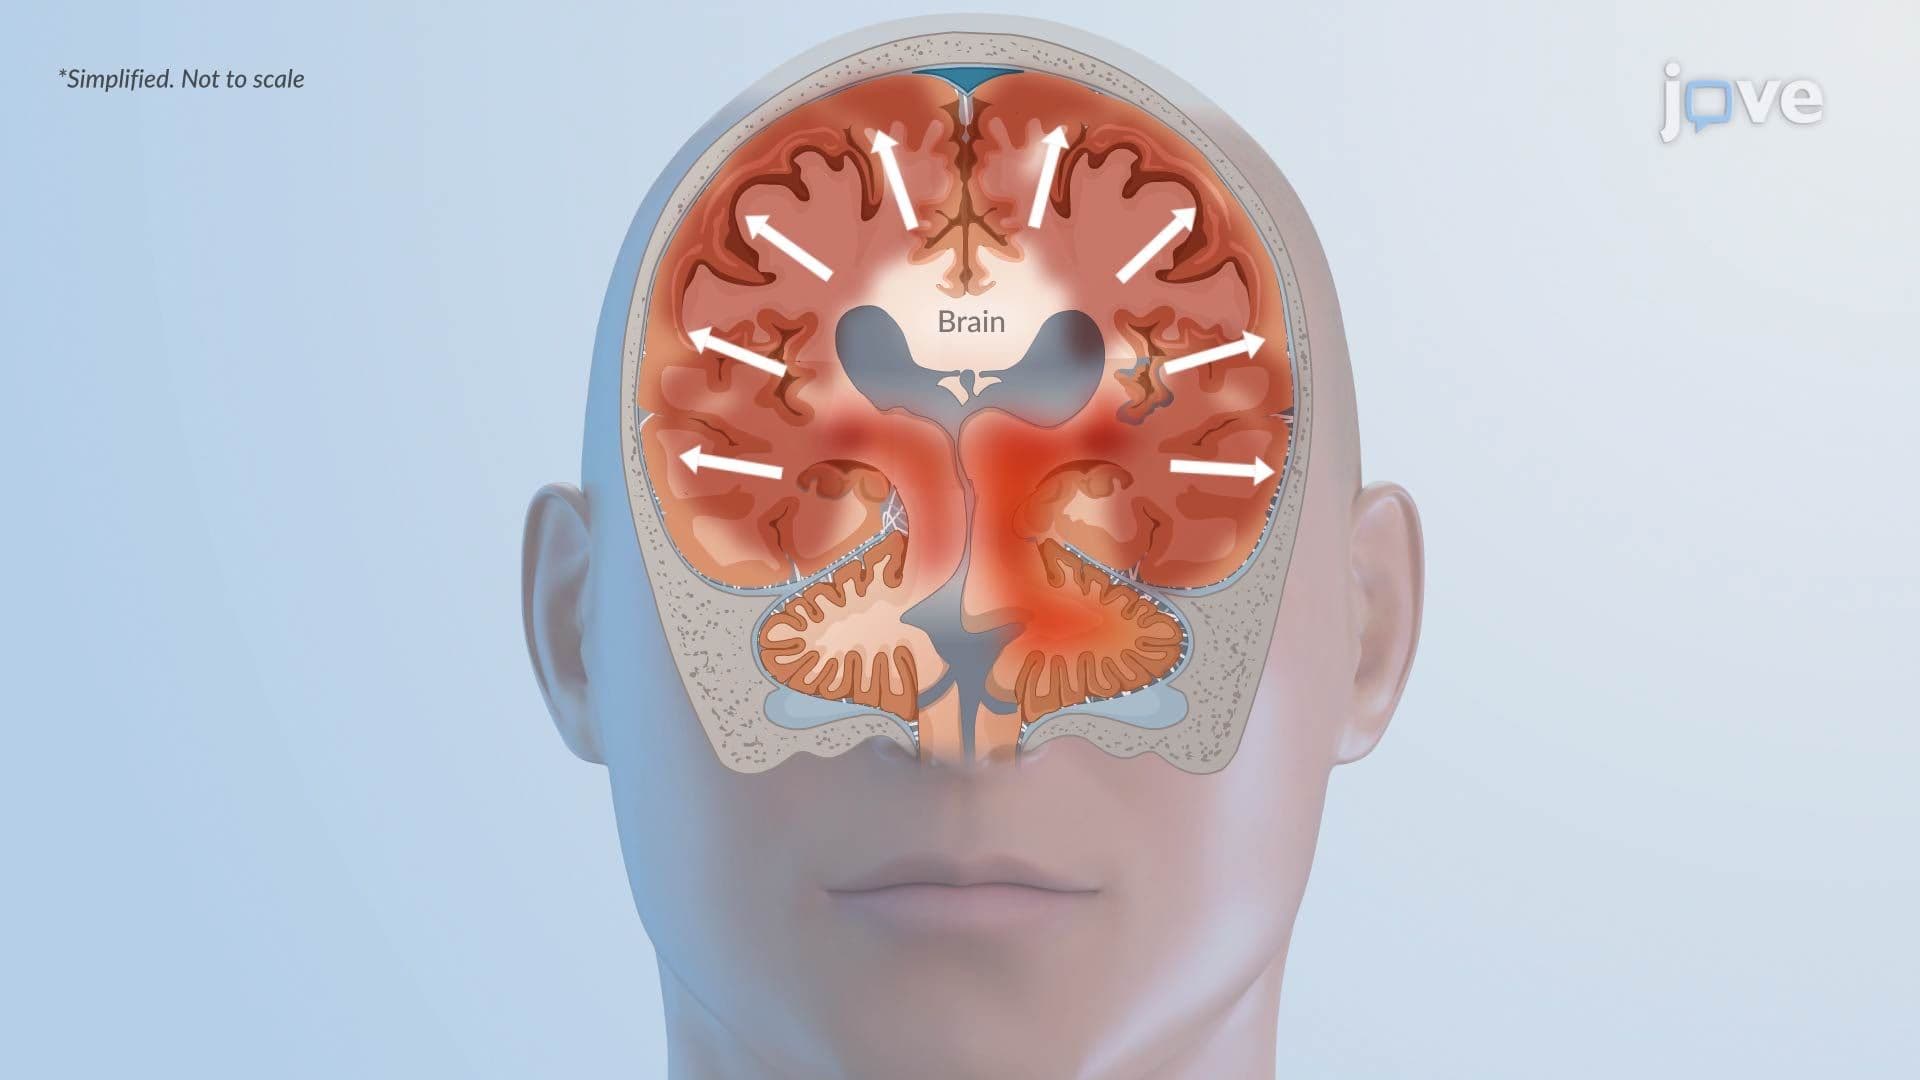
Intracranial hypertension is a sustained elevation of intracranial pressure (ICP) above 22 mm Hg. In supine adults, normal ICP is ~7–15 mm Hg.The rigid, nonexpandable cranium contains three components—brain tissue, blood, and cerebrospinal fluid (CSF)—that total ~1,700 mL in a typical adult: 1,400 mL brain (~80%), 150 mL blood (~10%), and 150 mL CSF (~10%). According to the Monro–Kellie doctrine, total intracranial volume is effectively fixed. When one component expands, CSF and venous blood...
Cytotoxic Edema: Pathophysiology01:21

Cytotoxic Edema: Pathophysiology

Cytotoxic edema is a form of cerebral edema characterized by intracellular swelling of neurons, astrocytes, and other glial cells. It develops when the mechanisms responsible for maintaining ionic gradients across the cell membrane become impaired. Under normal physiological conditions, the sodium–potassium ATPase actively transports sodium ions out of the cell and potassium ions into the cell, preserving osmotic balance and enabling electrical signaling. This pump requires a continuous supply...
Hepatic Encephalopathy01:29

Hepatic Encephalopathy

DefinitionHepatic encephalopathy is a reversible neurologic syndrome that results from advanced liver dysfunction or portosystemic shunting. It leads to disturbances in cognition, behavior, and motor function due to the brain’s exposure to gut-derived toxins that the liver fails to detoxify.EtiologyThis condition develops either in the setting of acute fulminant hepatitis or progressively during chronic liver disease, such as cirrhosis and portal hypertension. Portosystemic shunting—including...
Secondary Spinal Cord Injury llI: Pathophysiology01:25

Secondary Spinal Cord Injury llI: Pathophysiology

Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...