Congenital pulmonary lymphangiectasis presenting as a unilateral hyperlucent lung

C W Verlaat1, H M Peters, B A Semmekrot

  • 1Department of Paediatrics, University of Nijmegen, The Netherlands.

Related Concept Videos

Gross Anatomy of the Lungs01:17

Gross Anatomy of the Lungs

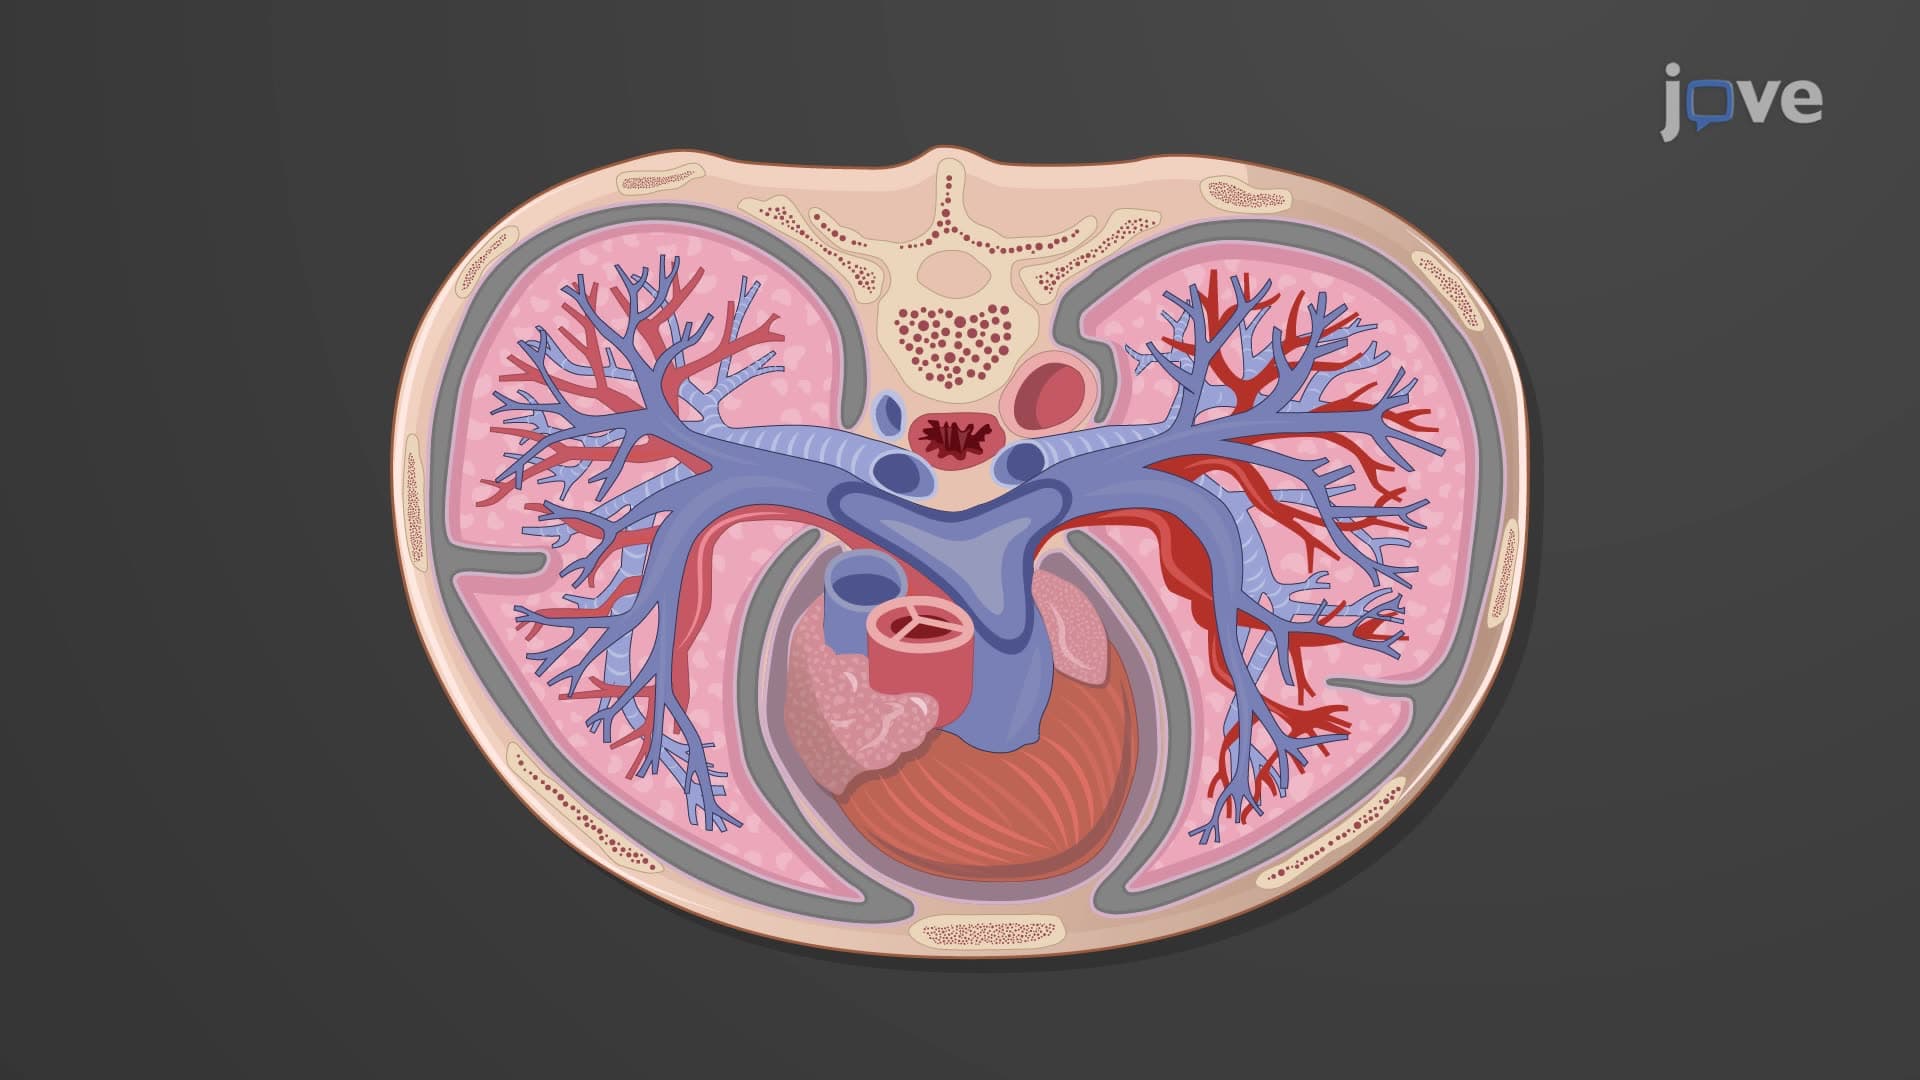
The lungs are a pair of vital organs connected to the trachea via the left and right bronchi. The base of these organs meets the dome-shaped muscle known as the diaphragm. Encased by the pleurae, the lungs contact the mediastinum. The right lung is shorter yet wider, and has a larger volume than the left lung. The left lung has an indentation known as the cardiac notch. The superior region of the lungs is referred to as the apex, whereas the base is the lower region near the diaphragm. The...
Pneumothorax-I01:26

Pneumothorax-I

A pneumothorax is a condition where air builds up in the space between the lung and the chest wall, causing the lung to collapse. This condition arises when air enters the space between the parietal and visceral pleura, disrupting the negative pressure essential for lung inflation. This can lead to a partial or complete collapse of the lung.
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
Pneumothorax II: Pathophysiology01:08

Pneumothorax II: Pathophysiology

Pneumothorax means the presence of air in the pleural space — the thin potential gap between the visceral and parietal pleura. This condition disrupts the normal pressure balance that keeps the lungs inflated, leading to partial or complete collapse of the affected lung.Normal physiologyUnder normal conditions, the pleural space maintains a slightly negative intrapleural pressure, which keeps the lungs expanded against the chest wall. This negative pressure creates a delicate balance between...
Chronic Obstructive Pulmonary Disease II: Emphysema01:23

Chronic Obstructive Pulmonary Disease II: Emphysema
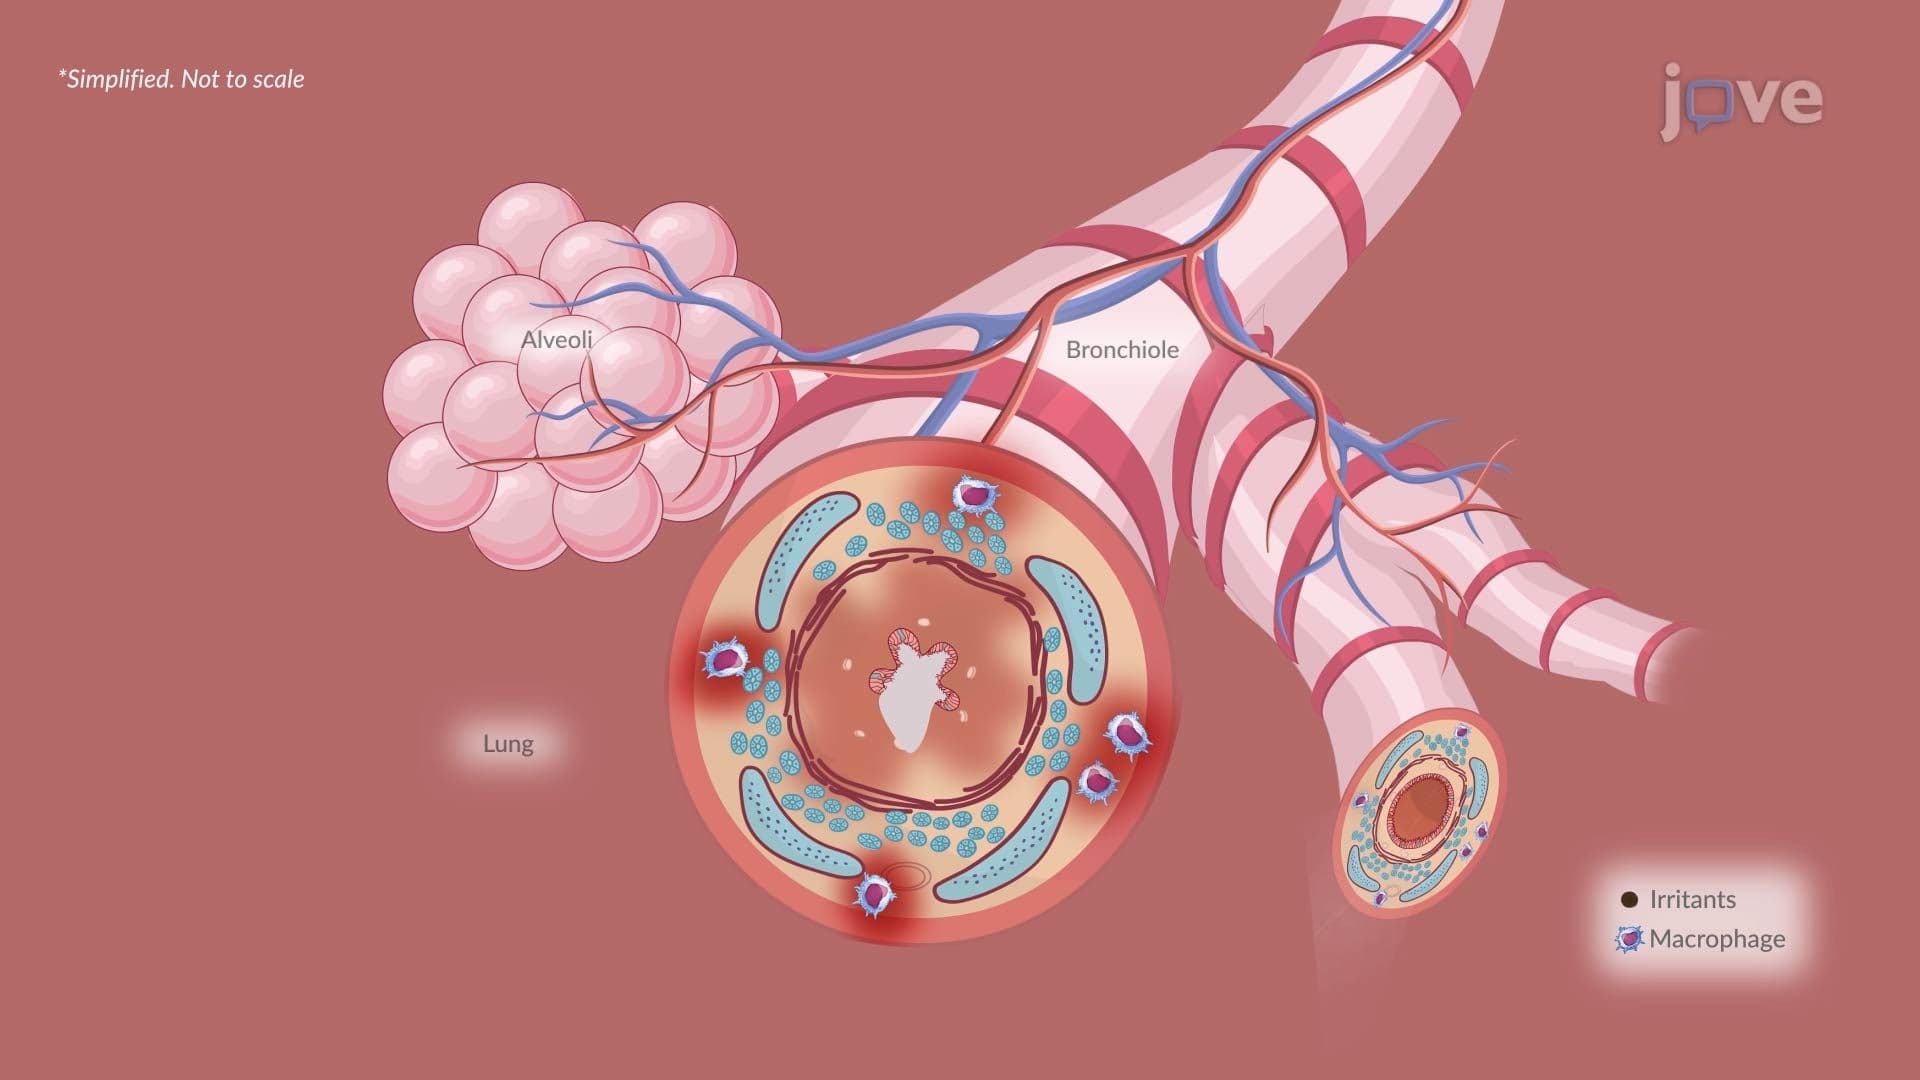
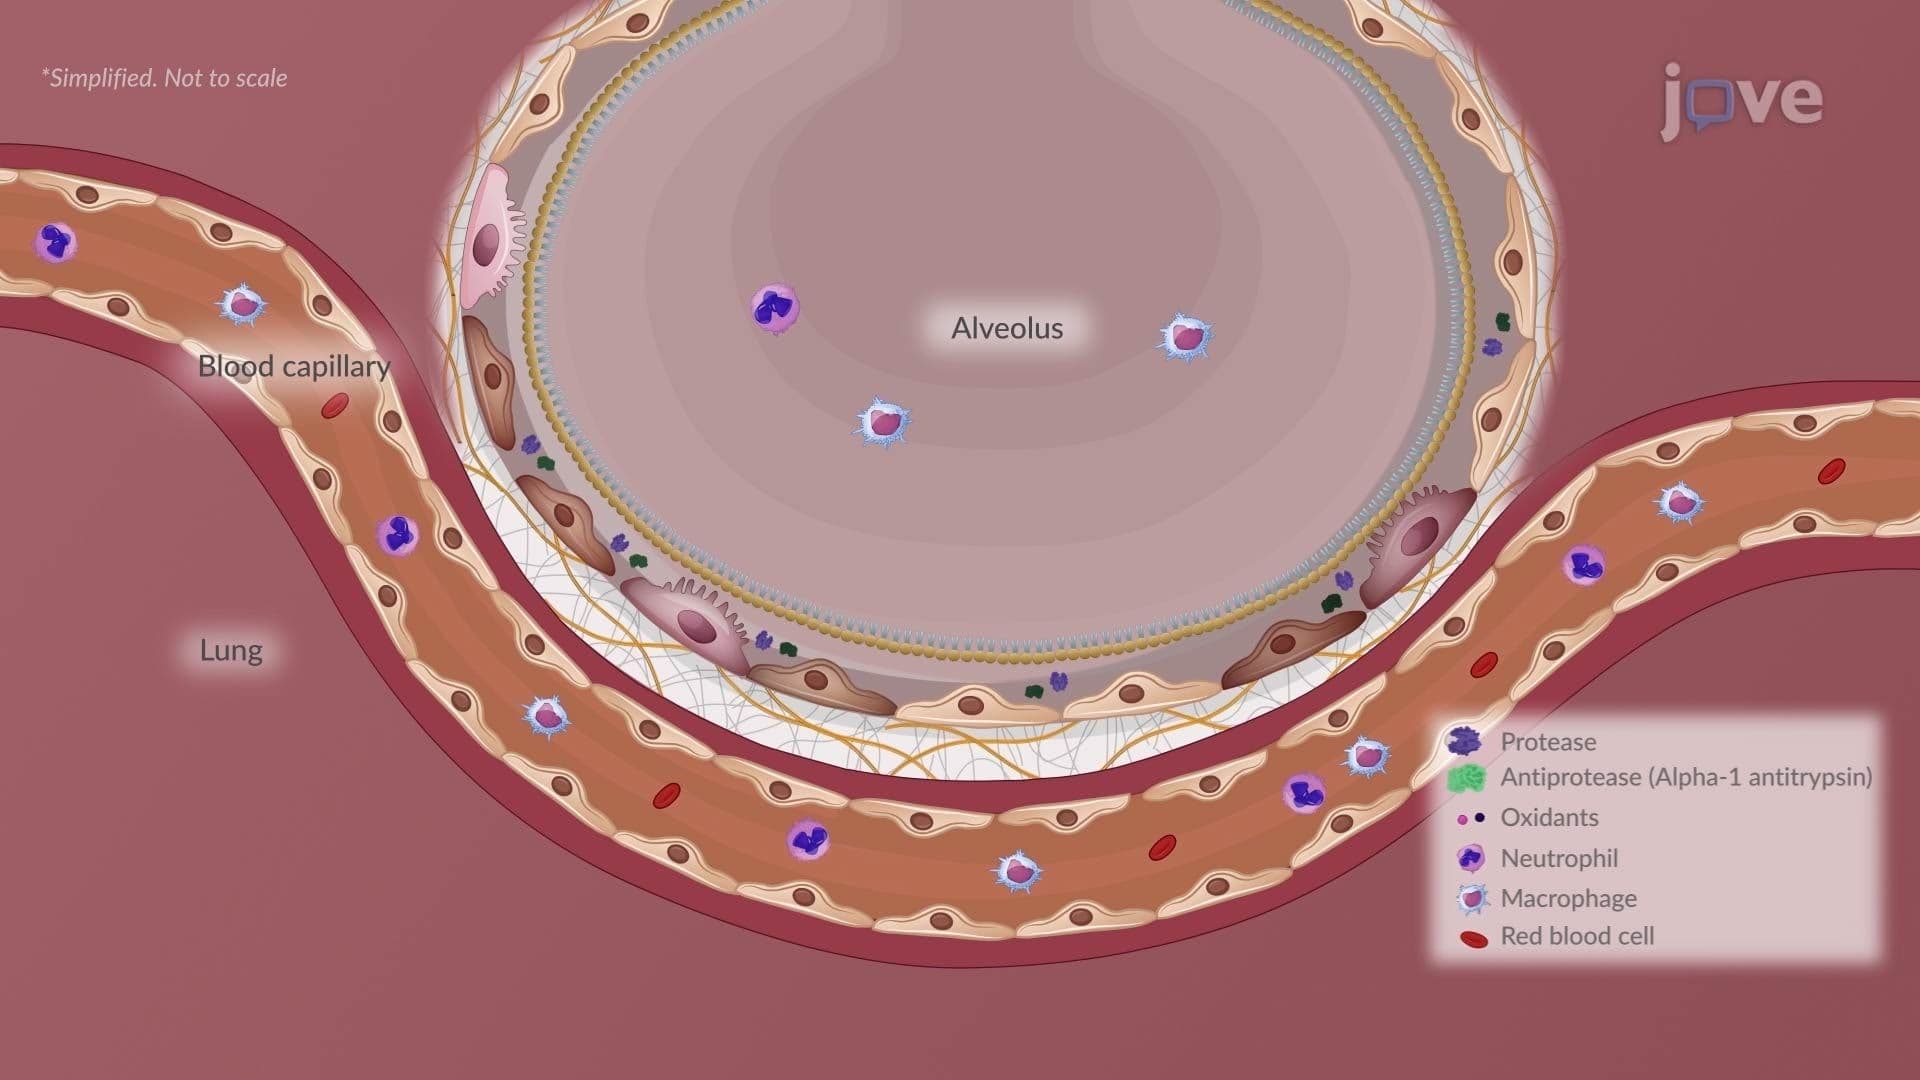
Emphysema, a major phenotype of chronic obstructive pulmonary disease (COPD), is characterized by irreversible destruction of alveolar walls and permanent enlargement of distal airspaces. Unlike chronic bronchitis, which primarily affects the airways, emphysema predominantly involves the lung parenchyma, where structural damage leads to airflow limitation.PathophysiologyIt most commonly results from prolonged exposure to cigarette smoke and other toxic gases, particularly cigarette smoke.
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features01:24

Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features

Chronic bronchitis is a key phenotype of chronic obstructive pulmonary disease (COPD), characterized by airway-centered inflammation and mucus overproduction. It develops from long-term exposure to harmful particles or gases, most commonly cigarette smoke, which triggers a persistent inflammatory response.Cellular and Structural ChangesInflammation initially affects the large bronchi and later the smaller airways, with infiltration by immune cells, including neutrophils, macrophages, and...
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations01:19

Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations

Chronic Obstructive Pulmonary Disease, or COPD, is a long-term condition marked by persistent and only partially reversible airflow limitation. It involves two overlapping conditions—chronic bronchitis and emphysema—which often co-appear but differ in dominant symptoms and underlying mechanisms.Chronic Bronchitis FeaturesChronic bronchitis presents with a persistent productive cough and thick, sometimes purulent mucus due to airway inflammation, enlarged mucus glands, and goblet cell...