Related Experiment Video
Updated: Sep 24, 2026


Double-barreled and Concentric Microelectrodes for Measurement of Extracellular Ion Signals in Brain Tissue
Published on: September 5, 2015
Acidemia and hypernatremia enhance postischemic recovery of excitation-contraction coupling
K Harada1, A Franklin, R G Johnson
1Charles A. Dana Research Institute, Beth Israel Hospital, Boston, MA 02215.

Abstract:
The purpose of the present study was to determine whether Na(+)-H+ and Na(+)-Ca2+ exchanges modulate postischemic recovery of excitation-contraction coupling. Experiments were performed in 43 isolated isovolumic dog hearts perfused with blood (pH 7.40, 141 mmol/L Na+, 34 degrees C, paced at 2 Hz). A 3 x 3-mm region at the left ventricular (LV) apex was loaded with aequorin for monitoring [Ca2+]i simultaneously with LV pressure. No-flow ischemia for 2 to 3 minutes was followed by 20 minutes of aerobic reperfusion with (1) unmodified control blood (141 mmol/L Na+, pH 7.40), (2) acidemic blood (141 mmol/L Na+, pH 6.60, at 0 to 3 minutes of reperfusion), (3) hypernatremic blood (149 or 157 mmol/L Na+, pH 7.40, at 0 to 20 minutes of reperfusion), or (4) hyperosmotic blood (141 mmol/L Na+ + 30 mmol/L mannitol, pH 7.40, at 0 to 20 minutes of reperfusion). Reperfusion with unmodified control blood was immediately followed by an increase in [Ca2+]i and LV systolic and diastolic pressure that persisted for 2 to 3 minutes before returning to or below baseline. Ventricular arrhythmia occurred during this period (> 80%). This transient increase of [Ca2+]i was attenuated by acidemic or hypernatremic perfusate. With acidemic or hypernatremic reperfusion, recovery of LV developed pressure at 20 minutes was more complete than with unmodified control reperfusion: acidemic blood (n = 7), 93 +/- 3% (P < .01); hypernatremic blood (149 mmol/L Na+, n = 7), 89 +/- 2% (P < .02); hypernatremic blood (157 mmol/L Na+, n = 4), 91 +/- 2% (P < .01); and unmodified control blood (n = 17), 80 +/- 2%. With hyperosmotic reperfusion, recovery of LV developed pressure at 20 minutes was not improved (82 +/- 3%). From these results we conclude that (1) an increase in intracellular Ca2+ occurs transiently after no-flow ischemia and may cause arrhythmia and decreased Ca2+ responsiveness of the contractile elements, (2) acidemic and hypernatremic reperfusion ameliorates postischemic dysfunction by preventing the increase in intracellular Ca2+, suggesting that (3) Na(+)-H+ and Na(+)-Ca2+ exchange may play important modulatory roles during reperfusion.
More Related Videos
 09:51
Recording Synaptic Plasticity in Acute Hippocampal Slices Maintained in a Small-volume Recycling-, Perfusion-, and Submersion-type Chamber System
Published on: January 1, 2018
 05:26
Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Related Concept Videos
 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:29
Relaxation of Skeletal Muscles
When an action potential reaches the axon terminal, it depolarizes the membrane and opens voltage-gated sodium channels. Sodium ions enter the cell, further depolarizing the presynaptic membrane. This depolarization causes voltage-gated calcium channels to open.
 01:24
Muscle Recovery and Fatigue
 01:28
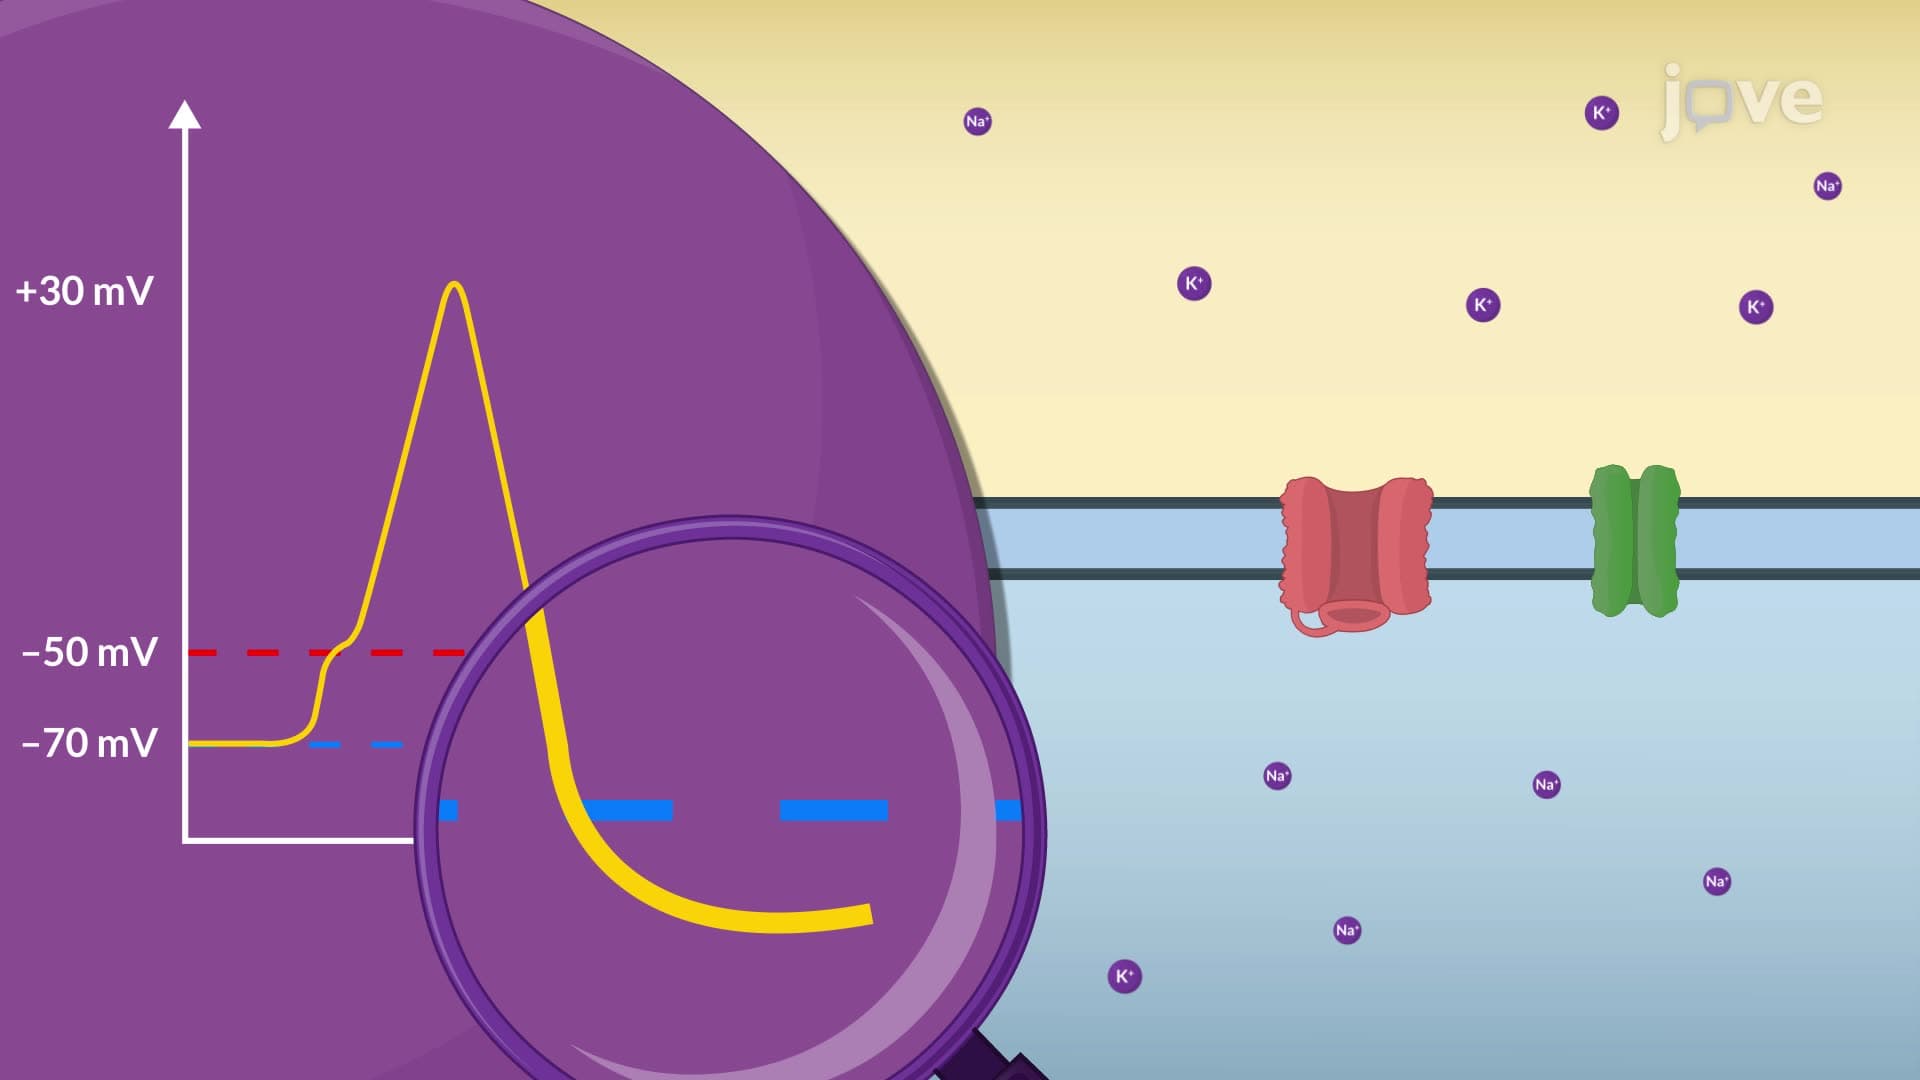
Action Potential: Phases of Stimulation
Resting Phase:
In this phase, the cell's membrane is at its resting potential, typically around -70 millivolts (mV) for neurons. Inside the cell, there is a higher concentration of potassium ions (K+) and a lower concentration of sodium ions (Na+). Voltage-gated sodium channels are closed, and...
 01:26
Heart Failure Drugs: Inotropic Agents
 01:21
Cytotoxic Edema: Pathophysiology