Selection of optimal prophylactic aminoglycoside dosage in cancer patients: population pharmacokinetic approaches
Related Experiment Video
Updated: Oct 17, 2026

Evaluating the Effectiveness of Cancer Drug Sensitization In Vitro and In Vivo
Published on: February 6, 2015
J P Ordovás1, C L Ronchera, J L Poveda
1Pharmacy Service, Hospital Dr Peset, Valencia, Spain.

Abstract:
We report an alternative dose-finding approach for the selection of optimal prophylactic aminoglycoside dosage in specific (sub)populations of patients. Relative a priori utility of several intervals of gentamicin or tobramycin (AMG) peak and trough serum levels were assigned by a group of pharmacokinetics experts, assuming prophylactic administration for laryngectomy interventions. A group of 27 adult patients, with normal renal function, undergoing elective surgery for laryngeal problems and treated prophylactically with gentamicin (80 mg t.i.d.) or tobramycin (100 mg t.i.d.) was studied. Two blood samples (peak and trough) were drawn at steady-state for AMG assay. Three different methods, standard two-stage (STS), extended least-squares non-linear regression [MULTI(ELS)] and non-parametric expected maximization (NEPM), were used to estimate the pharmacokinetic (PK) population parameters. PK simulations were applied to estimate the AMG steady-state concentrations from the PK population parameters. From these data, relative utility values were calculated, allowing the selection of the optimal dosage schedule for this group of patients. There were no statistically significant differences between the PK population estimates as generated by the three methods. Using the STS estimates, the simulation of several dosages indicated that the optimal dosage is 170 mg every 8 h. Conversely, using the individual PK parameters and the mean AMG levels simulated from them, the dose with best relative utility is 130 mg every 8 h. This important difference points out the relevance of the use of relative utilities for the AMG serum concentrations in the selection of optimal a priori dosage. We propose the use of 120 mg every 8 h as the safer dose for our population. Further studies are needed to validate this proposal in patients similar to ours.
More Related Videos
 09:17
A Robust Pneumonia Model in Immunocompetent Rodents to Evaluate Antibacterial Efficacy against S. pneumoniae, H. influenzae, K. pneumoniae, P. aeruginosa or A. baumannii
Published on: January 2, 2017
 08:57
Sample Extraction and Simultaneous Chromatographic Quantitation of Doxorubicin and Mitomycin C Following Drug Combination Delivery in Nanoparticles to Tumor-bearing Mice
Published on: October 5, 2017
Related Concept Videos
 01:28
Dosage Regimens: Designs and Approaches
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:23
Dosage Regimen Designs: Nomograms and Tabulations
 01:15
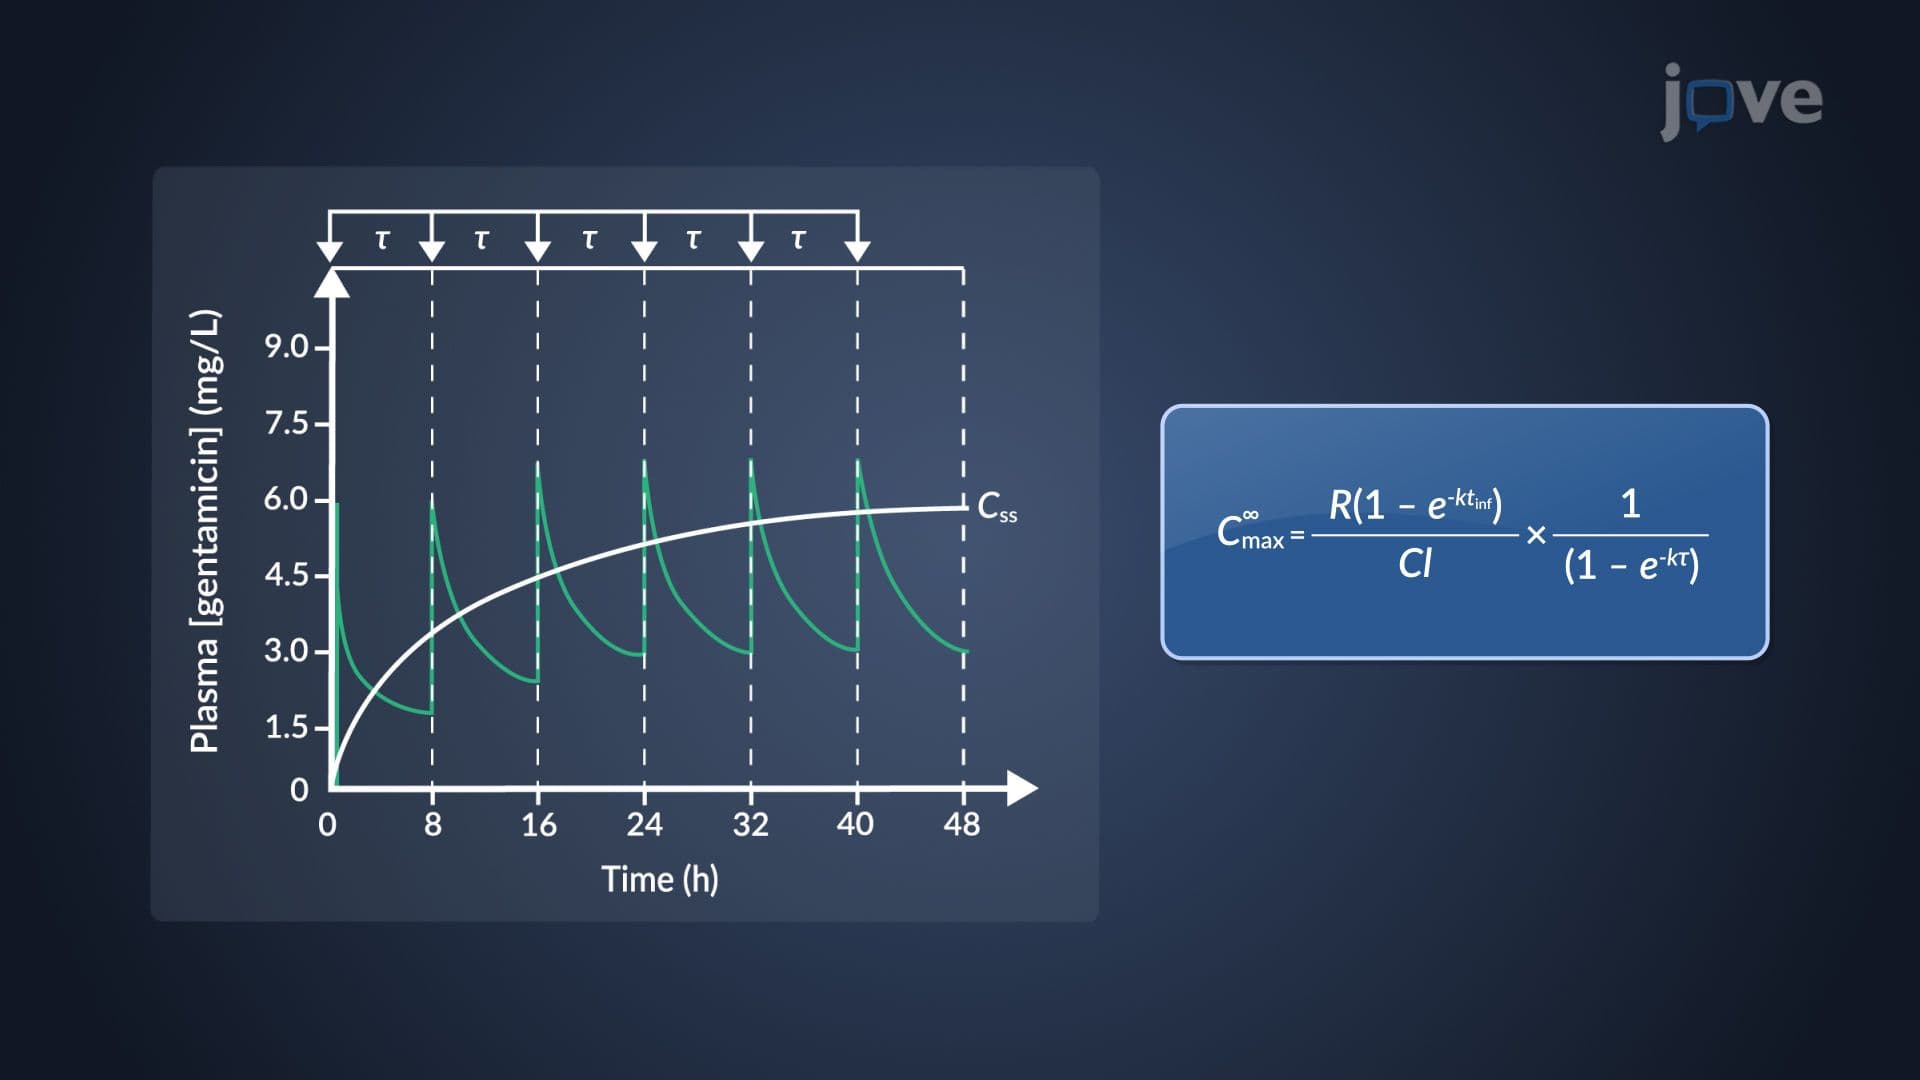
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:20
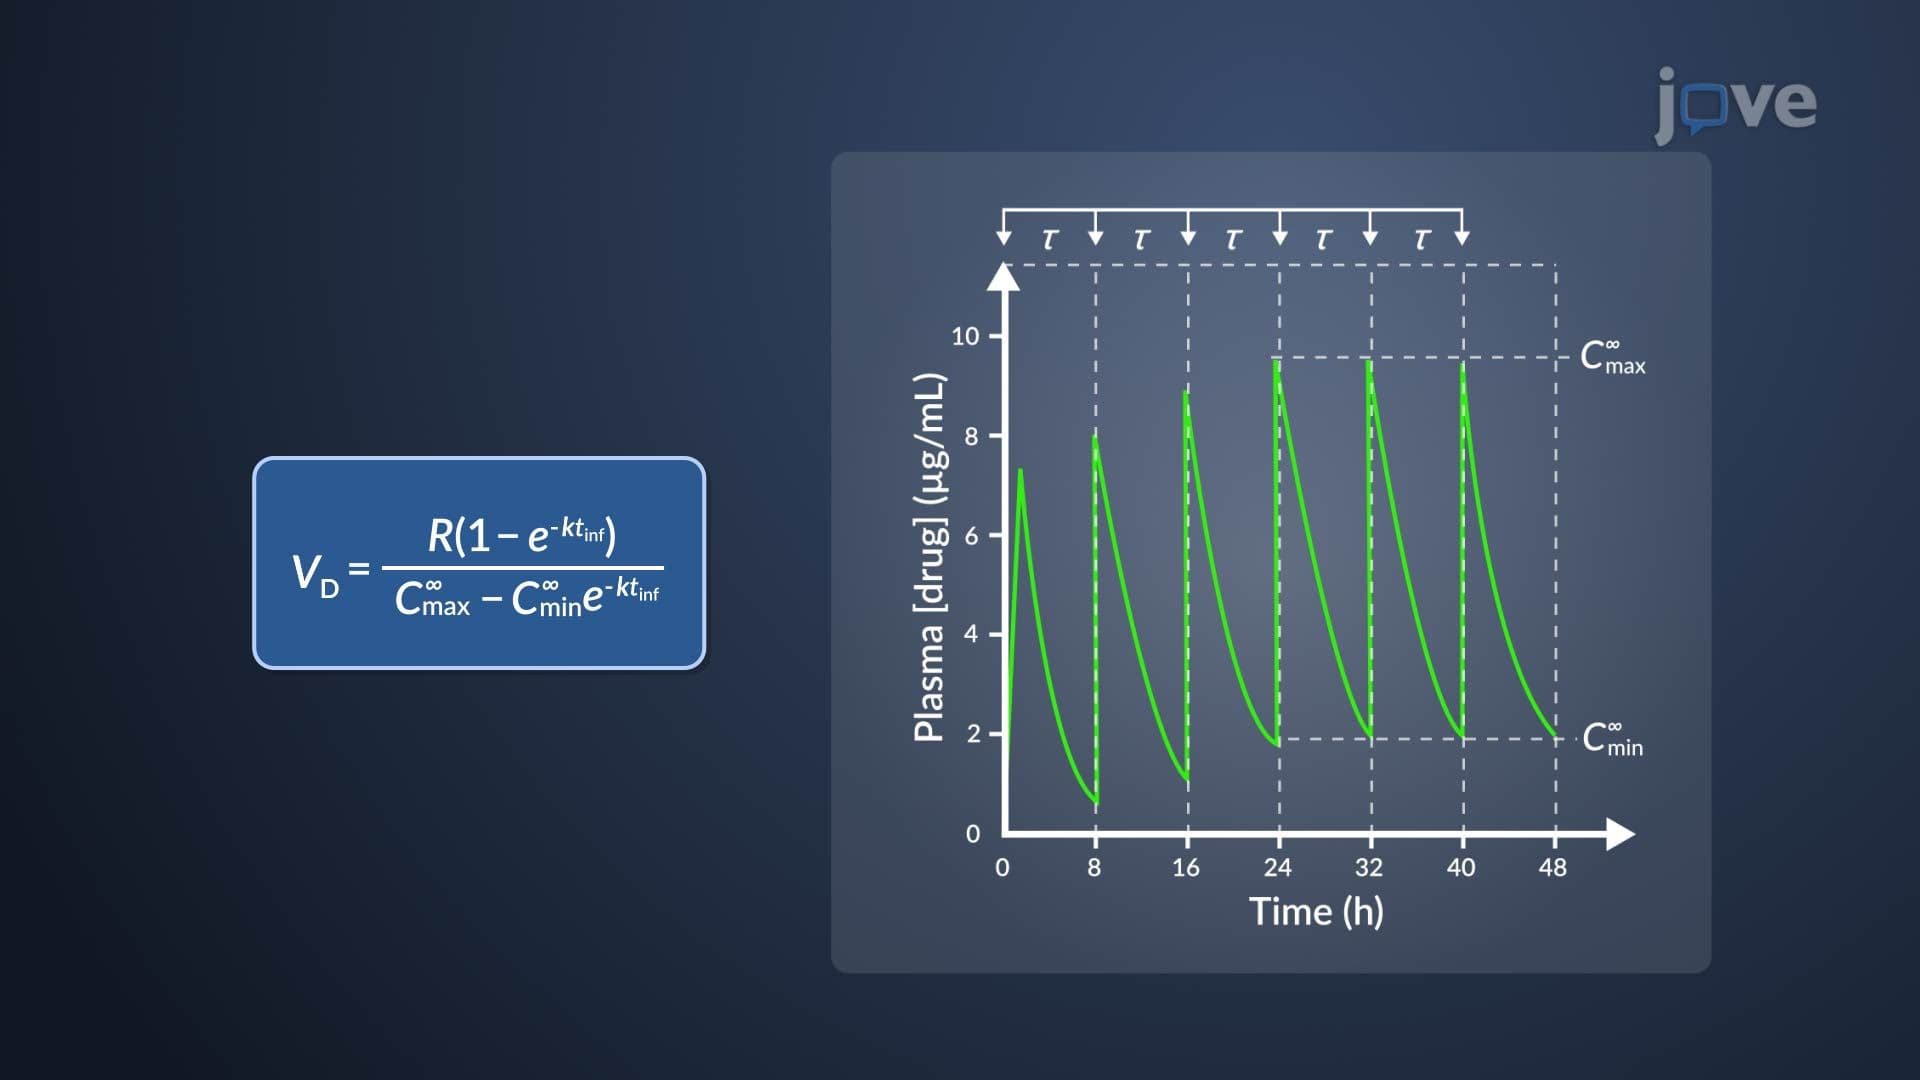
Estimation of k and VD of Aminoglycosides
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion