Related Experiment Video
Updated: Aug 8, 2026

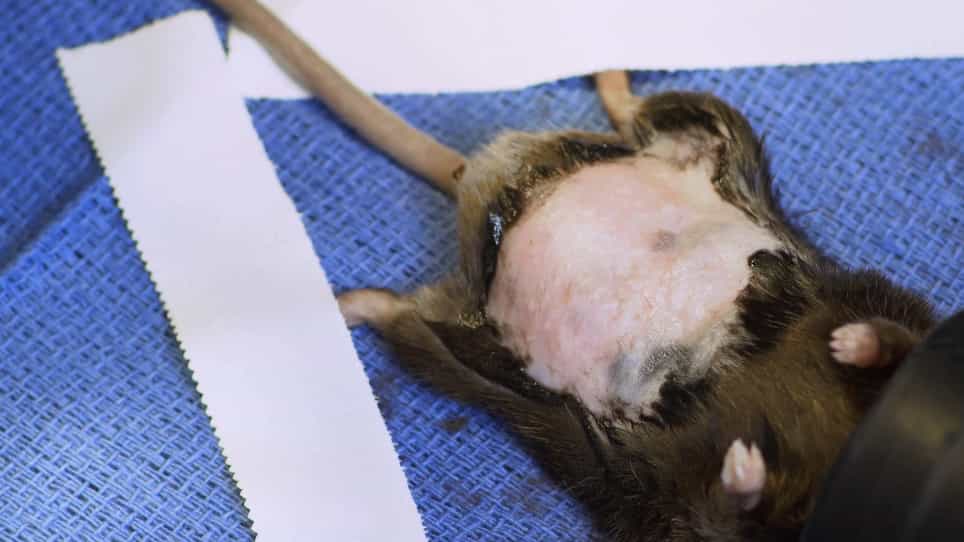
Murine Distal Colostomy, A Novel Model of Diversion Colitis in C57BL/6 Mice
Published on: July 12, 2018
[Our technic for continent perineal colostomies after the abdominal-perineal amputation of the rectum]
R Musiani1, R Banchi, S Pialli
1U.O. di Chirurgia Generale, Regione Toscana, USL n. 14, Cecina, Livorno.

Abstract:
Having briefly outlined the complex question of definitive abdominal colostomy, understood as an inevitable stage in demolitive anorectal surgery if the tumour is localised approximately 7-10 cm from the anus, the authors propose abdominal-perineal and perineal colostomy as logical alternative capable of offering a more satisfactory quality of life with equal oncological radicality. Currently used techniques are then discussed by which the perineal colostomy is fitted with a sphincter to make it continent. From this it emerges that the common limits to each method largely consist in the complexity of the operation and the type of postoperative care required, including a long period of postoperative stomal rehabilitation (with the relative equipment and staff) in order to achieve better functional results. Using their 10-year experience of perineal colostomies, also with sphincters, as a starting point, the authors illustrate their personal technique which ensures a degree of stomal continence which is comparable if not better than that obtained using other surgical procedures but is not so difficult to perform and does not require such full-time assistance. The consequent improved risk-benefit ratio for this type of operation means that the indications can be widened to coincide with those for traditional abdomino-perineal colostomy both with regard to age and the stage of disease. There are two basic steps in this technique. The first involves abdomino-peroneal demolition secondary to cancer and follows the conventional lines of classic abdomino-perineal colostomy; the second involves the sphincteric reconstruction which is performed using an extremely simple technique. The two small anti-mesenteric tenia of the prestomal colon are mobilised and placed around the colon so that they form a smooth double sphincter which completely occludes the former's lumen. On completing surgery, the sphincteric structure lies just above the perineal stoma whereas the underlying tract of colon, which is the site of the muscle graft, is completely extra-corporal until it has become regularized. The surgical safety of this technique is immediately evident from the fact that since it was introduced temporary abdominal colostomy has been no longer been performed, thus avoiding subsequent colorrhaphic surgery and reducing hospital stay, patient suffering and social costs.

Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:24
Ostomy Care
An ostomy is a surgical procedure that creates an artificial opening from the intestines to the outside of the body, allowing for the rerouting of effluent. This opening is known as a stoma. A stoma usually protrudes above the skin surface, appearing pink or red, moist, and round, and it lacks nerve sensations.
There are different types of ostomies, including colostomies, ileostomies, and urostomies: