Related Experiment Video
Updated: Sep 6, 2026
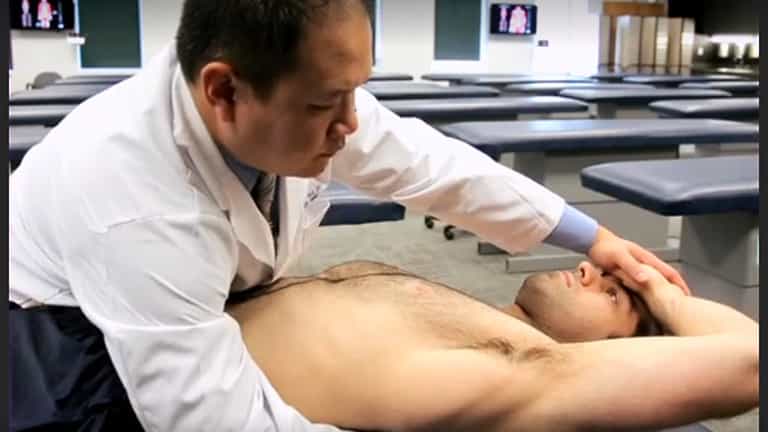

Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
Maternal perceptions of pneumonia and pneumonia signs in Pakistani children

Fifty mothers of children attending a hospital outpatient clinic with non-severe pneumonia (fast breathing but no chest indrawing) were interviewed in depth. Maternal perceptions and practices with clinical significance were documented. Results showed that most mothers initially tried "heat-producing" home remedies designed to counter the "coldness" of the disease, allowed only 2 days for any particular allopathic medicine to work, and did not go to the same practitioner twice. When mothers were asked what had alarmed them enough to come to the hospital, the symptoms named most frequently were persistent severe cough and high fever, inability to sleep and excessive crying. Fast breathing was spontaneously mentioned by only a few, although when questioned, 32/50 said that they had noticed it. The mothers who had prior experience with child pneumonia were more likely to notice fast breathing and also came to the hospital earlier than those who were inexperienced. Relatively higher levels of maternal education and income were suggestively associated with bringing a female child rather than a male child for pneumonia treatment. Fewer than half of the mothers knew where air goes when a person breathes in and where the lungs are located. Most held treatment preferences at odds with the protocols proposed for the national ARI program currently being initiated in Pakistan, e.g. they said that a doctor should use a stethoscope, should prescribe suspensions rather than tablets and should give injections. This study provides baseline data on attitudes and behaviors that can either be built on in that program or addressed through public education campaigns.
Fifty mothers of children attending a hospital outpatient clinic with non-severe pneumonia (fast breathing but no chest indrawing) were interviewed in depth. Maternal perceptions and practices with clinical significance were documented. Results showed that most mothers initially tried "heat-producing" home remedies designed to counter the "coldness" of the disease, allowed only 2 days for any particular allopathic medicine to work, and did not go to the same practitioner twice. When mothers were asked what had alarmed them enough to come to the hospital, the symptoms named most frequently were persistent severe cough and high fever, inability to sleep and excessive crying. Fast breathing was spontaneously mentioned by only a few, although when questioned, 32/50 said that they had noticed it. The mothers who had prior experience with child pneumonia were more likely to notice fast breathing and also came to the hospital earlier than those who were inexperienced. Relatively higher levels of maternal education and income were suggestively associated with bringing a female child rather than a male child for pneumonia treatment. Fewer than half of the mothers knew where air goes when a person breathes in and where the lungs are located. Most held treatment preferences at odds with the protocols proposed for the national ARI program currently being initiated in Pakistan, e.g. they said that a doctor should use a stethoscope, should prescribe suspensions rather than tablets and should give injections. This study provides baseline data on attitudes and behaviors that can either be built on in that program or addressed through public education campaigns.
More Related Videos
 06:15
Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
 05:50
International Expert Consensus and Recommendations for Neonatal Pneumothorax Ultrasound Diagnosis and Ultrasound-guided Thoracentesis Procedure
Published on: March 12, 2020
Related Concept Videos
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 01:30
Pneumonia III: Complications and Assessment
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:14
Atypical Pneumonia
 01:29
Pneumonia I: Introduction