Increased pulmonary perfusion worsens ventilation-perfusion matching
Related Experiment Video
Updated: Jul 31, 2026
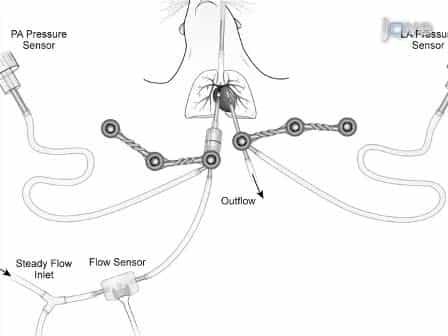
Characterization of the Isolated, Ventilated, and Instrumented Mouse Lung Perfused with Pulsatile Flow
Published on: April 30, 2011
K B Domino1, B L Eisenstein, T Tran
1University of Washington, School of Medicine, Seattle.

Background:
Severe exercise and administration of vasopressors may adversely affect pulmonary gas exchange in humans. The role of increases in pulmonary perfusion in worsening ventilation-perfusion (VA/Q) relationships is unclear, however, because concomitant changes in ventilation and alveolar gas composition occur. The purpose of this study was to determine whether increasing of lobar blood flow increased VA/Q heterogeneity in the absence of changes in respiratory parameters.
Methods:
Six pentobarbital-anesthetized dogs underwent bilateral thoracotomies, left upper lobectomy, and placement of an electromagnetic flow probe on the left lower lobe (LLL) pulmonary artery, and catheters were inserted into the LLL pulmonary artery distal to the flow probe and confluent trunk of the LLL pulmonary vein. A bronchial divider was inserted to allow separate ventilation of the right lung and LLL. Blood flow to the LLL (QLLL) was increased in random order to two and three times baseline blood flow by opening an arteriovenous fistula and partially occluding the right pulmonary artery. Minute ventilation and alveolar PCO2 of the lobe were unchanged due to use of constant tidal volume and respiratory rate and inspiration of variable amounts of carbon dioxide. VA/Q distributions of the LLL were obtained using the multiple inert gas elimination technique. The tracer inert gas arterial-alveolar difference ([a-A]D) area was used to assess VA/Q mismatch.
Results:
Increasing QLLL increased mean pulmonary artery pressure in the LLL (LLL Ppa). The PO2 of the LLL pulmonary venous blood remained unchanged, as the mixed venous oxygen tension (PvO2) was markedly increased. VA/Q inequality was increased, indicated by a 40% increase in the [a-A]D area when QLLL was increased to two times greater than baseline QLLL and a 58% increase in the [a-A]D area with three times greater than baseline QLLL. The [a-A]D area was highly correlated with the lobar blood flow (r = 0.97) and LLL Ppa (r = 0.97).
Conclusions:
Marked increases in lobar blood flow and Ppa worsened pulmonary gas exchange. The degree of impairment was correlated with the degree of increase in lobar perfusion. However, increased lobar perfusion did not affect LLL pulmonary venous blood oxygenation because the decrease in PO2, due to increased VA/Q mismatch, was opposed by an increase in PO2, due to increased PvO2.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 09:31
Normothermic Negative Pressure Ventilation Ex Situ Lung Perfusion: Evaluation of Lung Function and Metabolism
Published on: February 14, 2022
Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
External and Internal Respiration
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:22
Mitral Stenosis I: Introduction
 01:10
Atelectasis II: Pathophysiology
 01:18
Pulmonary Edema II: Pathophysiology