Related Experiment Video
Updated: Oct 3, 2026

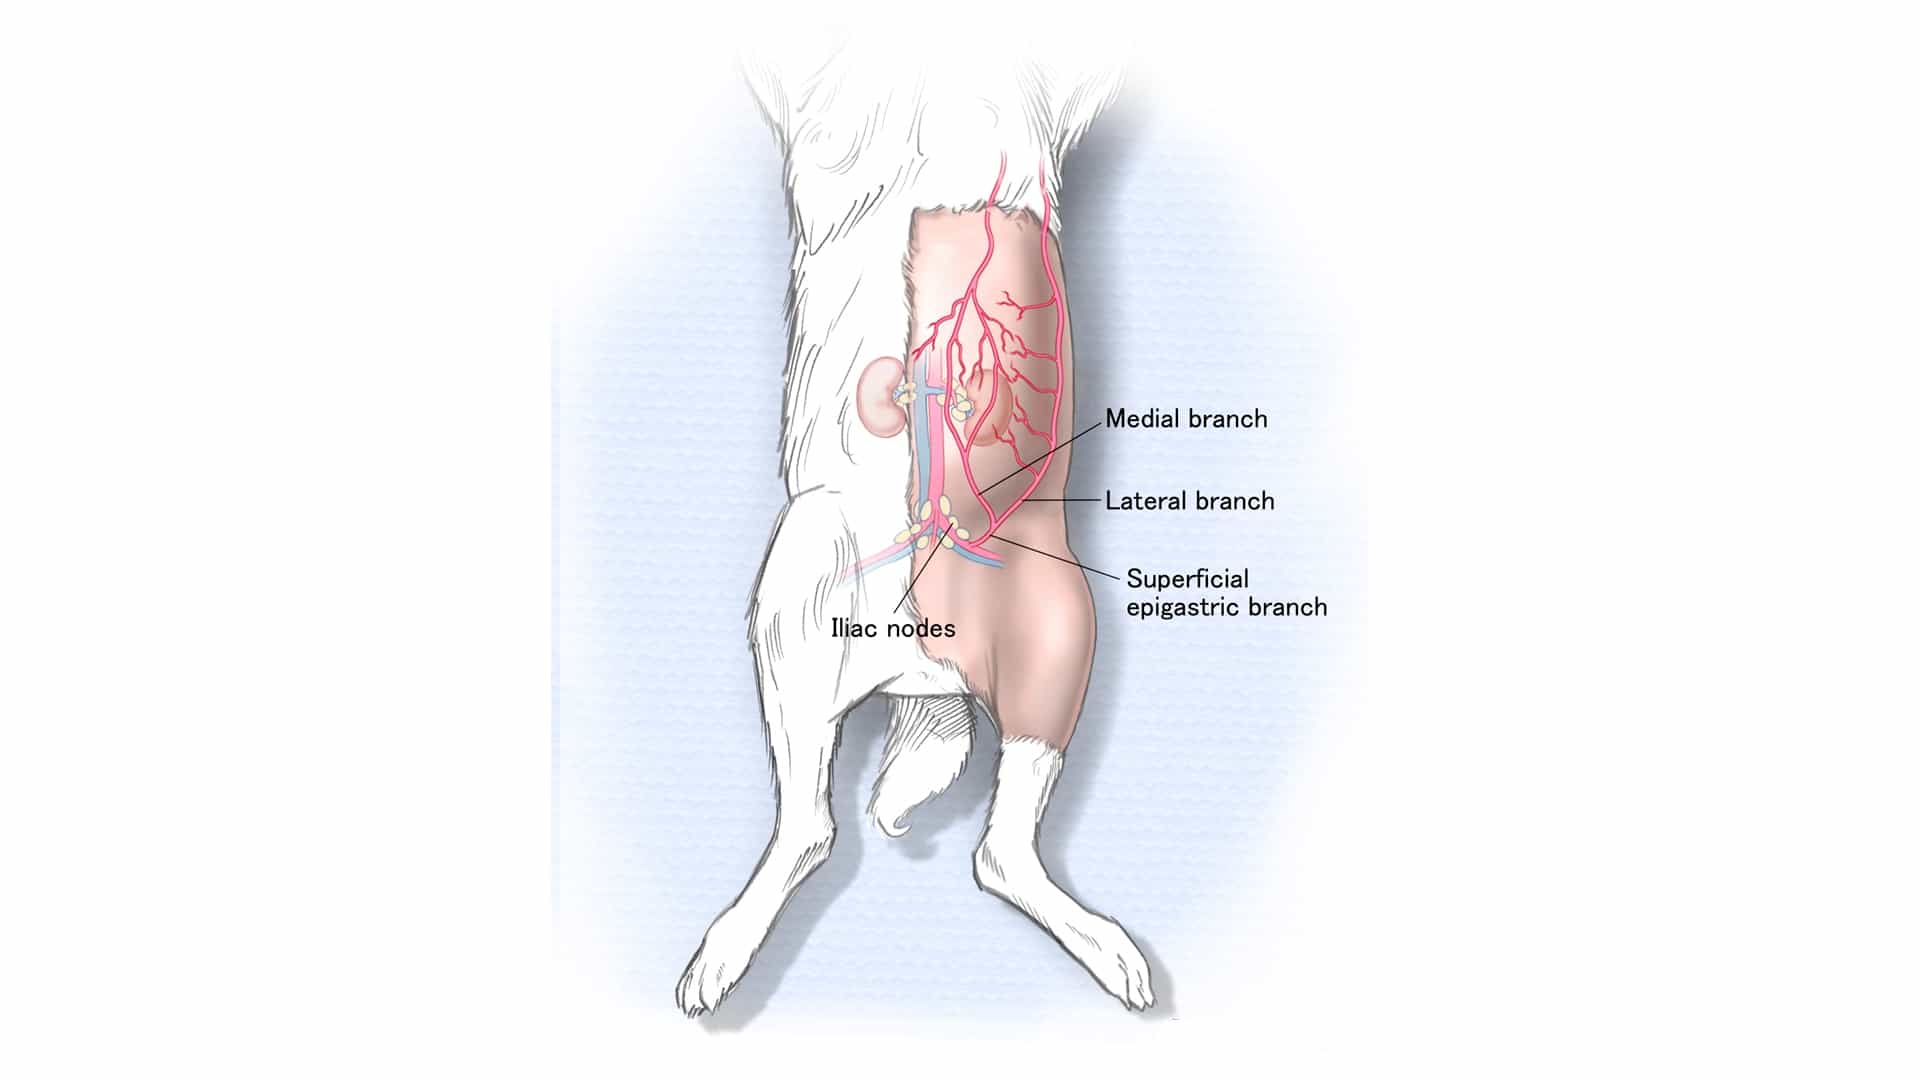
The Superficial Inferior Epigastric Artery Axial Flap to Study Ischemic Preconditioning Effects in a Rat Model
Published on: January 27, 2023
Inferior epigastric artery for myocardial revascularization
H B Barner1, K S Naunheim, P S Peigh
1Department of Surgery, St. Louis University Medical Center, MO 63110-0250.

From March 1990 through January 1992, 108 patients undergoing myocardial revascularization had one (91) or both (17) inferior epigastric arteries (IEA) used for myocardial revascularization. The internal thoracic artery (ITA) was used bilaterally in 87 patients. Of the 373 distal anastomoses, 210 (56%) were with the ITA, 130 (35%) with the IEA, and 12 (3%) with the gastroepiploic artery. Nineteen patients (18%) received 21 saphenous veins. When compared with the ITA, the IEA demonstrated a longer harvest time (36.5 vs 29.6 min, P < 0.0001), a shorter usable length (11.9 cm vs 16.5 cm, P < 0.001), and similar flow (49.7 cc/min vs 48.7 cc/min, P = NS). The operative mortality was 2.8%. Two deaths resulted from low cardiac output and the one remaining death from complications of a cerebral vascular accident. The most common major complication was respiratory insufficiency, which occurred in 11 patients (12%). There were two sternal infections (2%), and two abdominal wound infections (2%), none of which were fatal. The IEA is an acceptable additional arterial conduit. It can be safely employed with one or both ITAs. Short-term and long-term patency must be established before preferential use of this conduit is advised.
From March 1990 through January 1992, 108 patients undergoing myocardial revascularization had one (91) or both (17) inferior epigastric arteries (IEA) used for myocardial revascularization. The internal thoracic artery (ITA) was used bilaterally in 87 patients. Of the 373 distal anastomoses, 210 (56%) were with the ITA, 130 (35%) with the IEA, and 12 (3%) with the gastroepiploic artery. Nineteen patients (18%) received 21 saphenous veins. When compared with the ITA, the IEA demonstrated a longer harvest time (36.5 vs 29.6 min, P < 0.0001), a shorter usable length (11.9 cm vs 16.5 cm, P < 0.001), and similar flow (49.7 cc/min vs 48.7 cc/min, P = NS). The operative mortality was 2.8%. Two deaths resulted from low cardiac output and the one remaining death from complications of a cerebral vascular accident. The most common major complication was respiratory insufficiency, which occurred in 11 patients (12%). There were two sternal infections (2%), and two abdominal wound infections (2%), none of which were fatal. The IEA is an acceptable additional arterial conduit. It can be safely employed with one or both ITAs. Short-term and long-term patency must be established before preferential use of this conduit is advised.
More Related Videos

Related Concept Videos
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:25
Abdominal Aorta
The celiac trunk, a singular artery, divides into the left gastric artery, which...
 01:16
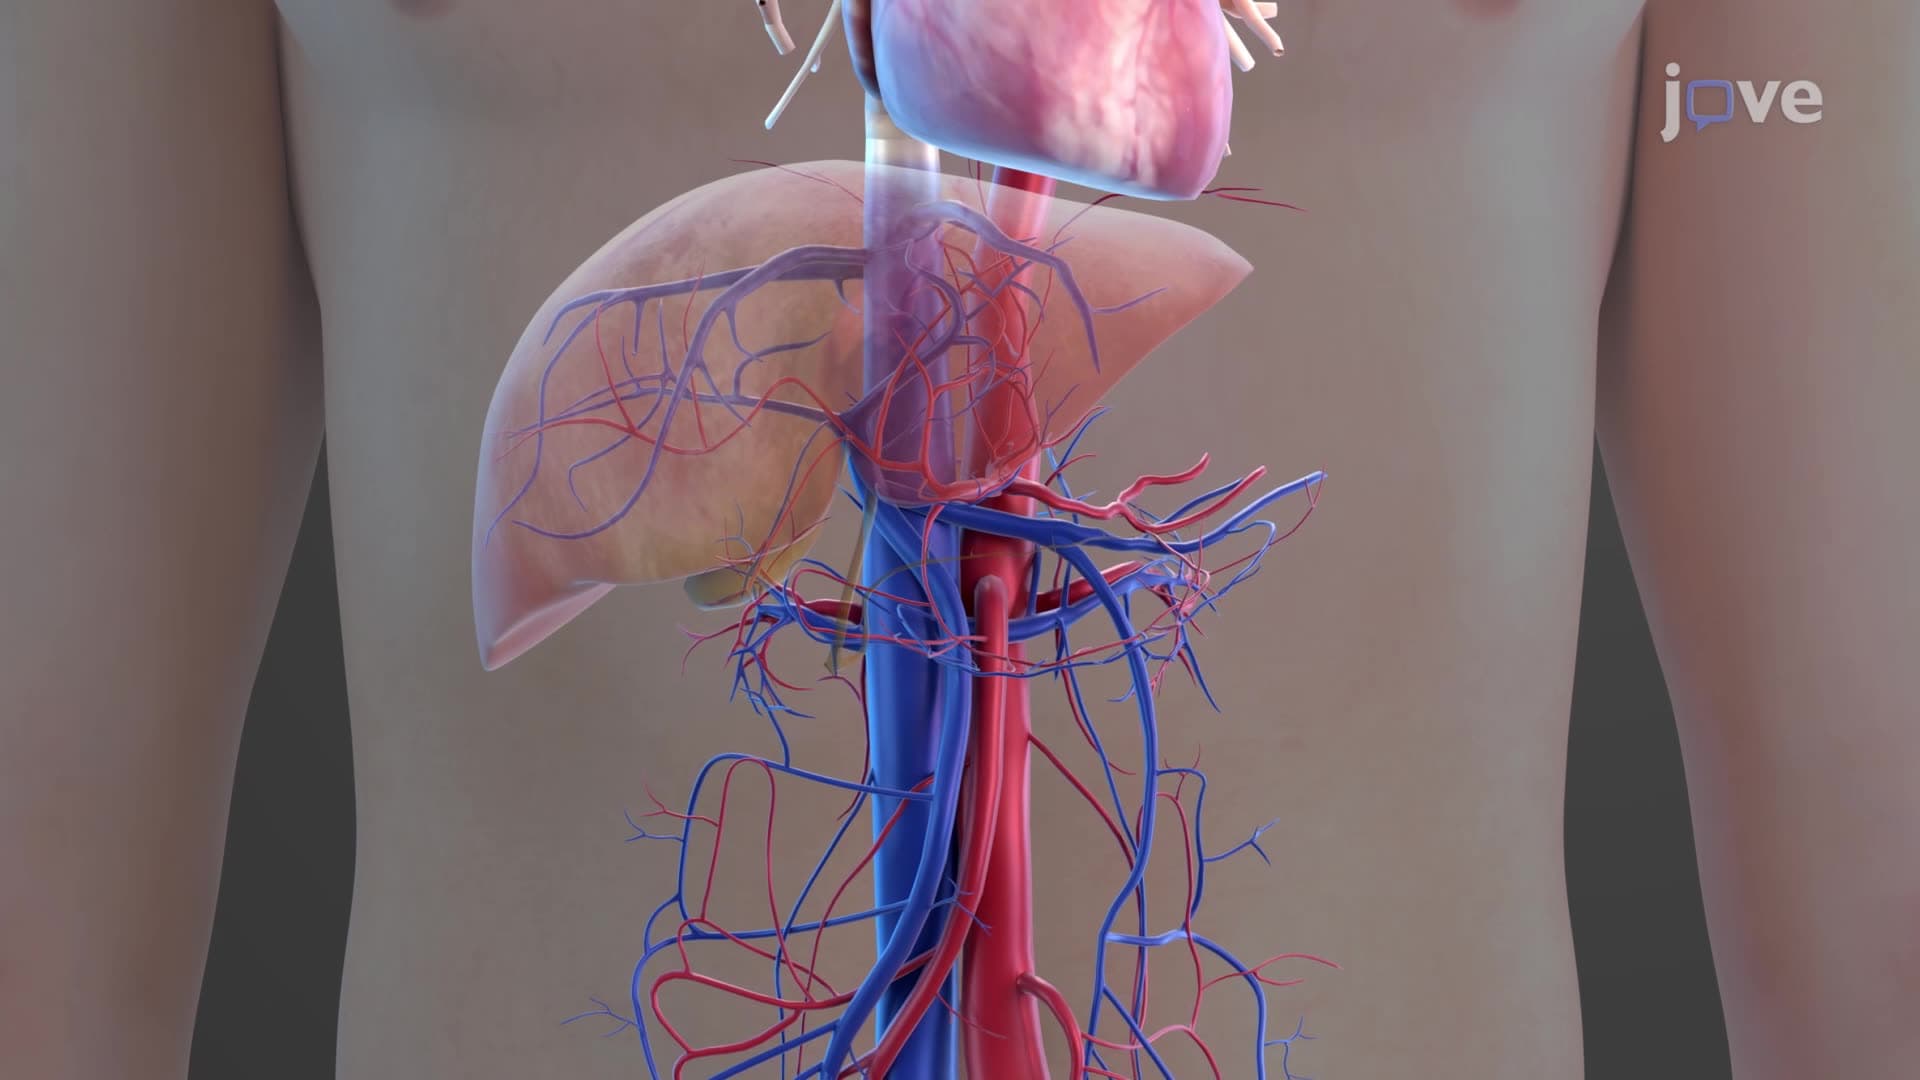
Blood Supply to the Digestive System
Blood Supply to the Digestive System: The splanchnic circulation involves three main arteries: the celiac artery (also known as the celiac trunk) and the superior and inferior mesenteric...