Hyponatraemia after acute spinal injury

A Biyani1, C G Inman, W S el Masry

  • 1Midlands Centre for Spinal Injuries, Robert Jones and Agnes Hunt Orthopaedic and District Hospital, Oswestry, Shropshire, UK.

Injury
|December 1, 1993
PubMed

Related Concept Videos

Local Anesthetics: Clinical Application as Spinal Anesthesia01:11

Local Anesthetics: Clinical Application as Spinal Anesthesia
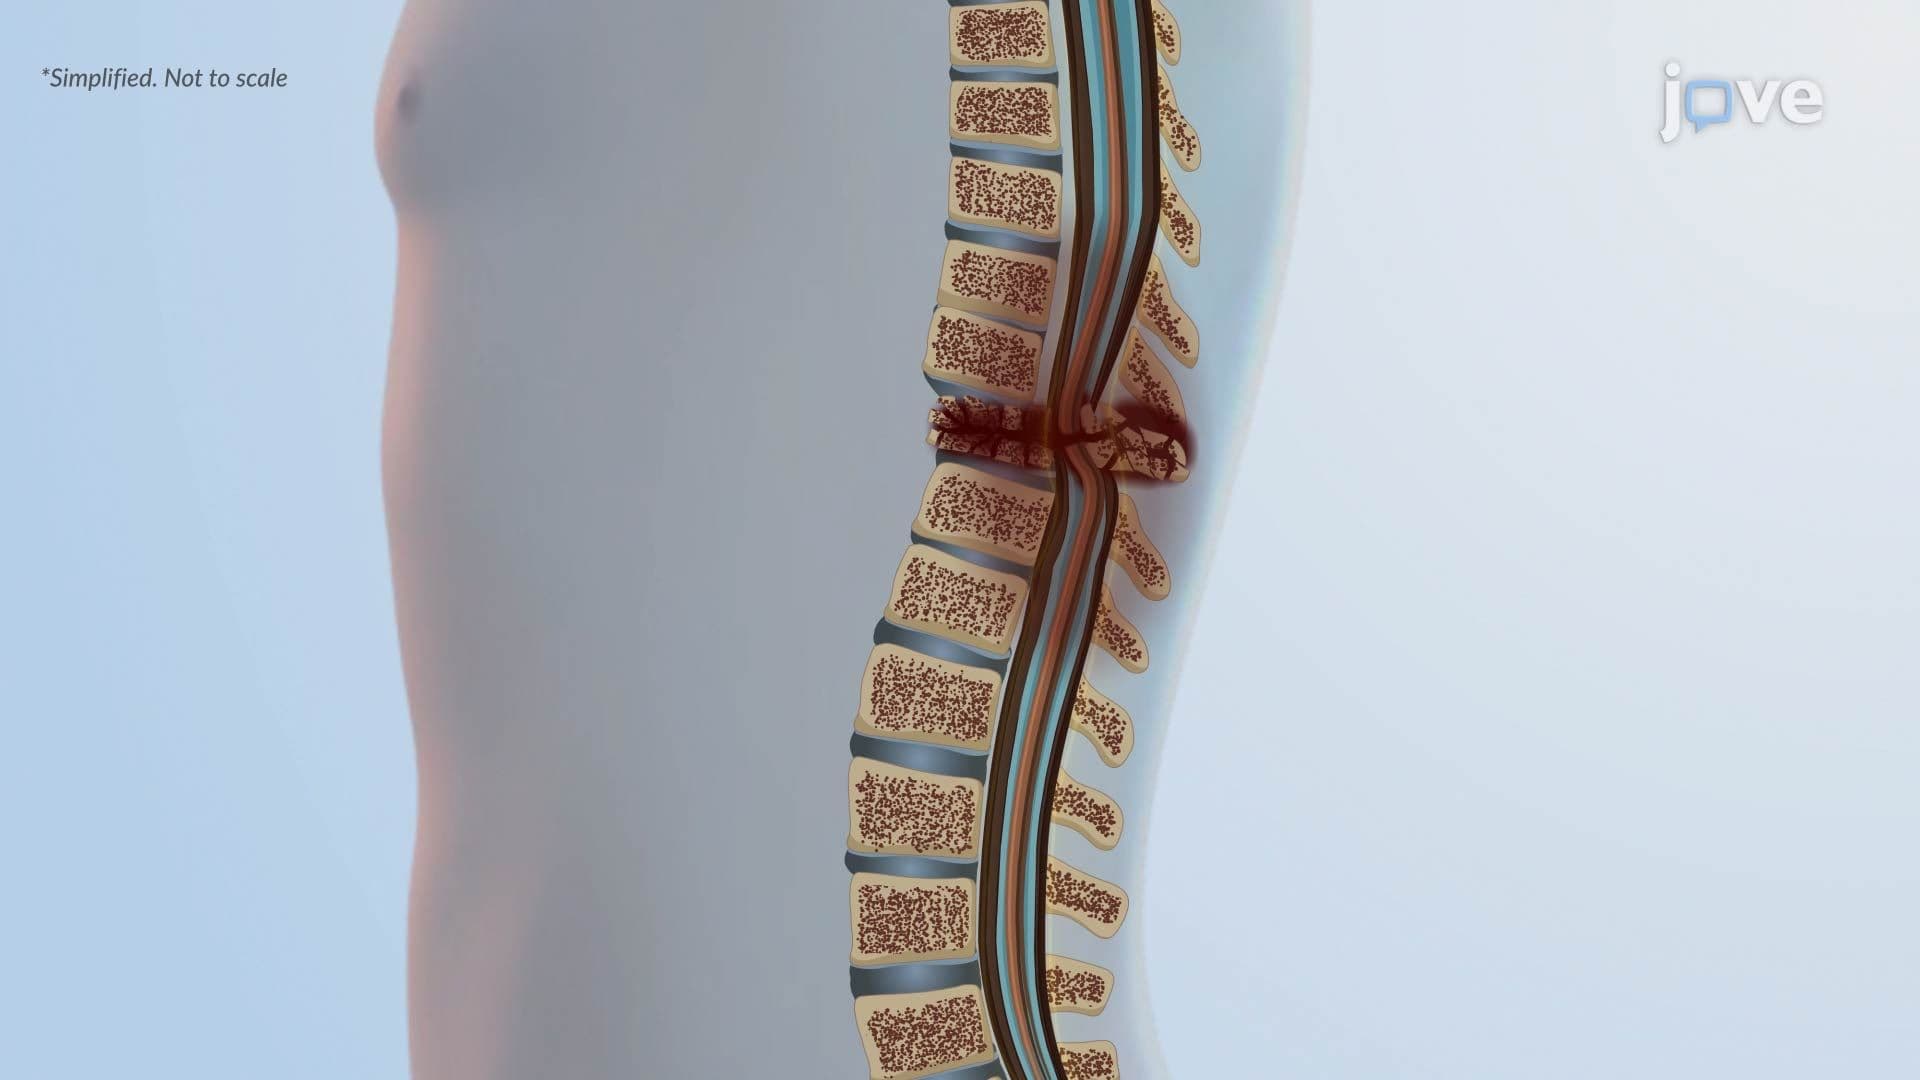
Spinal anesthetics are given during lower abdomen and limb surgeries to block sensory and motor neurons. They are administered in the mid to low lumbar regions, primarily acting on the cauda equina's nerve roots. The blockade level depends on the local anesthetic (LA) concentration. Usually, low LA concentrations are sufficient to block sensory fibers, while only high LA concentrations block motor fibers. Other factors like injection volume and speed, the patient's posture, and the drug...
Spinal Cord Injury ll: Pathophysiology01:14

Spinal Cord Injury ll: Pathophysiology

Spinal cord injury progresses through two interconnected phases: primary injury and secondary injury.Primary InjuryPrimary injury happens at the moment of trauma and involves immediate mechanical damage to the spinal cord.Compression happens when broken vertebrae, herniated discs, or accumulating blood (such as a hematoma) press directly against the spinal cord, distorting its normal shape and function. In cases of contusion, the cord is bruised by a blunt force (like penetrating injuries or...
Increased Intracranial Pressure l: Introduction01:14

Increased Intracranial Pressure l: Introduction

Intracranial hypertension is a sustained elevation of intracranial pressure (ICP) above 22 mm Hg. In supine adults, normal ICP is ~7–15 mm Hg.The rigid, nonexpandable cranium contains three components—brain tissue, blood, and cerebrospinal fluid (CSF)—that total ~1,700 mL in a typical adult: 1,400 mL brain (~80%), 150 mL blood (~10%), and 150 mL CSF (~10%). According to the Monro–Kellie doctrine, total intracranial volume is effectively fixed. When one component expands, CSF and venous blood...
Cerebral Edema ll: Pathophysiology01:22

Cerebral Edema ll: Pathophysiology

Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...
Cytotoxic Edema: Pathophysiology01:21

Cytotoxic Edema: Pathophysiology

Cytotoxic edema is a form of cerebral edema characterized by intracellular swelling of neurons, astrocytes, and other glial cells. It develops when the mechanisms responsible for maintaining ionic gradients across the cell membrane become impaired. Under normal physiological conditions, the sodium–potassium ATPase actively transports sodium ions out of the cell and potassium ions into the cell, preserving osmotic balance and enabling electrical signaling. This pump requires a continuous supply...
Secondary Spinal Cord Injury llI: Pathophysiology01:25

Secondary Spinal Cord Injury llI: Pathophysiology

Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...