Efficacy of bromocriptine administration for selective pituitary resistance to thyroid hormone

T Ohzeki1, K Hanaki, H Motozumi

  • 1Department of Pediatrics, Faculty of Medicine, Tottori University, Yonago, Japan.

Hormone Research
|January 1, 1993
PubMed

Related Concept Videos

Hypothyroidism II: Pathophysiology01:23

Hypothyroidism II: Pathophysiology

Hypothyroidism is a disorder characterized by insufficient production of thyroid hormones, which regulate metabolism, energy balance, and multiple organ systems.TypesHypothyroidism is classified based on the level of dysfunction. Primary hypothyroidism results from intrinsic thyroid gland dysfunction, causing reduced hormone production despite normal or increased stimulation. Secondary hypothyroidism arises from inadequate thyroid-stimulating hormone (TSH) secretion by the pituitary. Tertiary...
Synthesis and Regulation of Thyroid Hormones01:20

Synthesis and Regulation of Thyroid Hormones

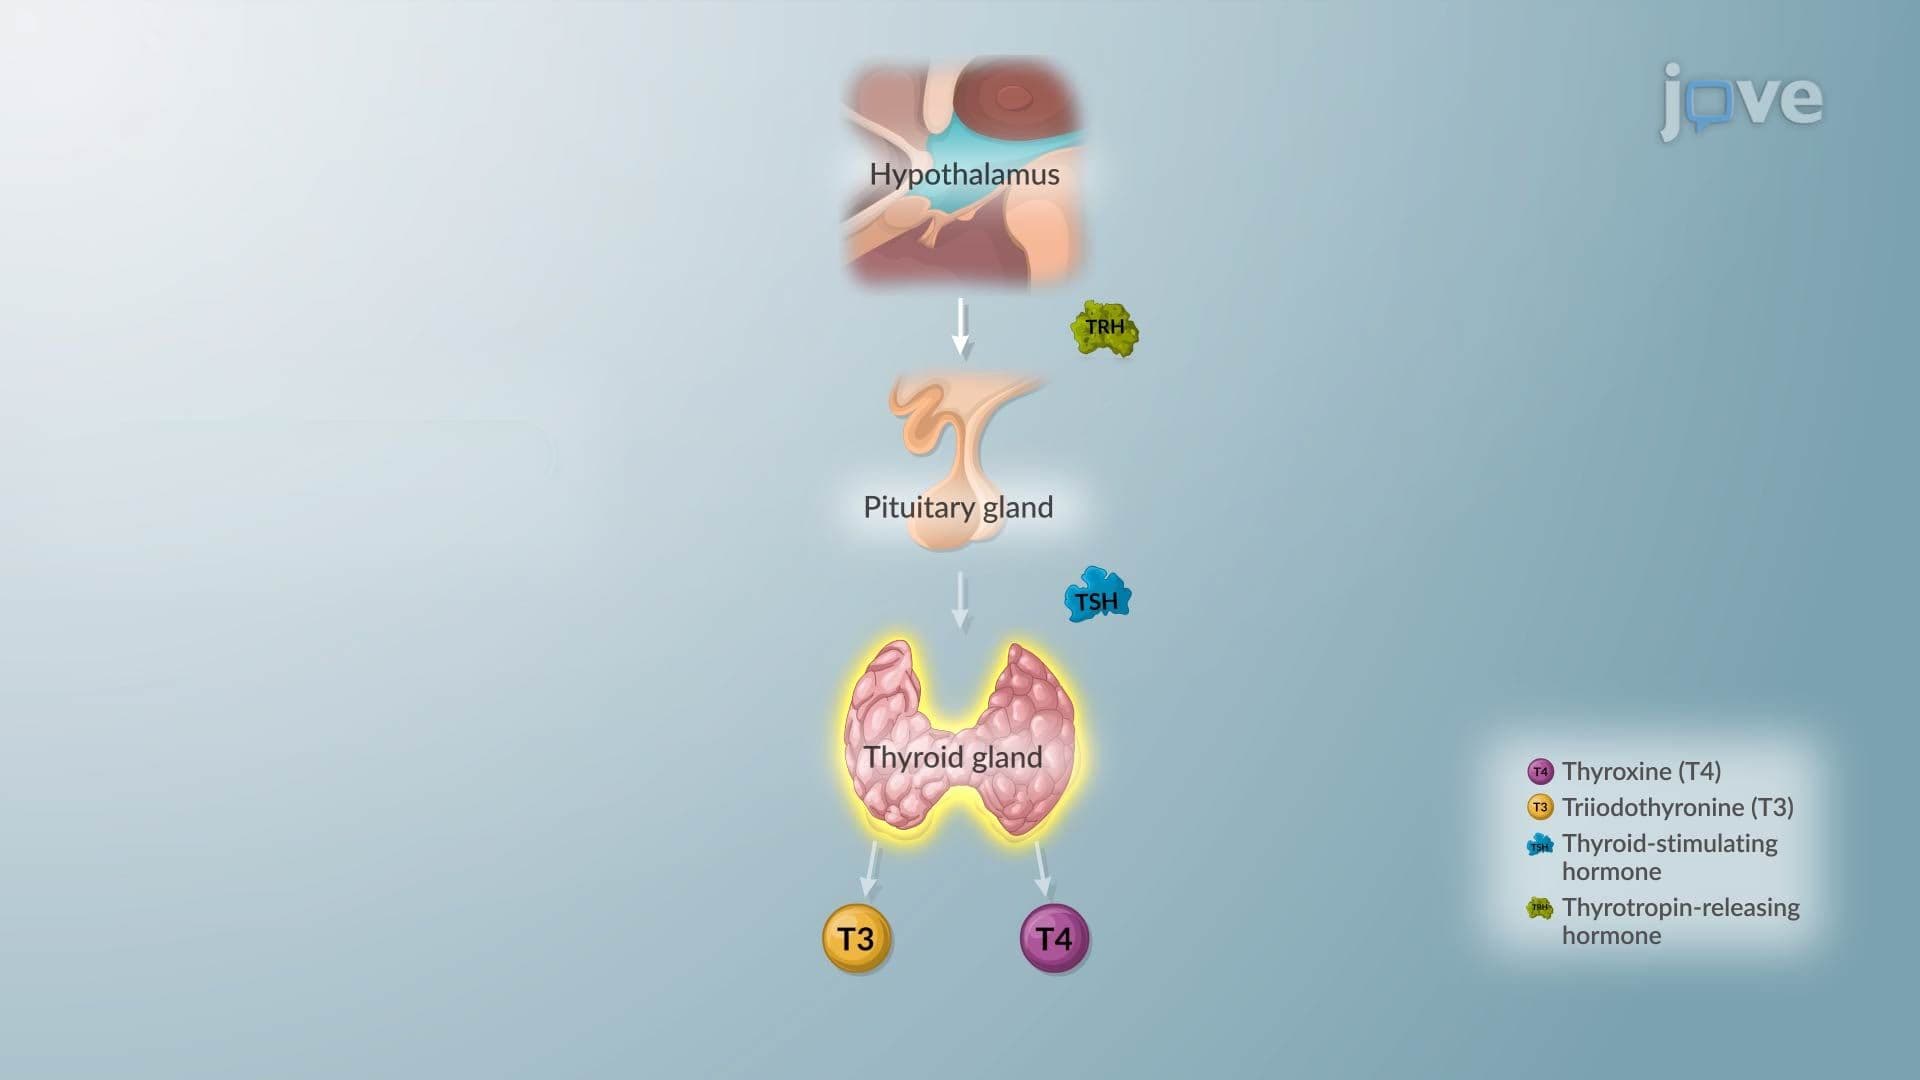
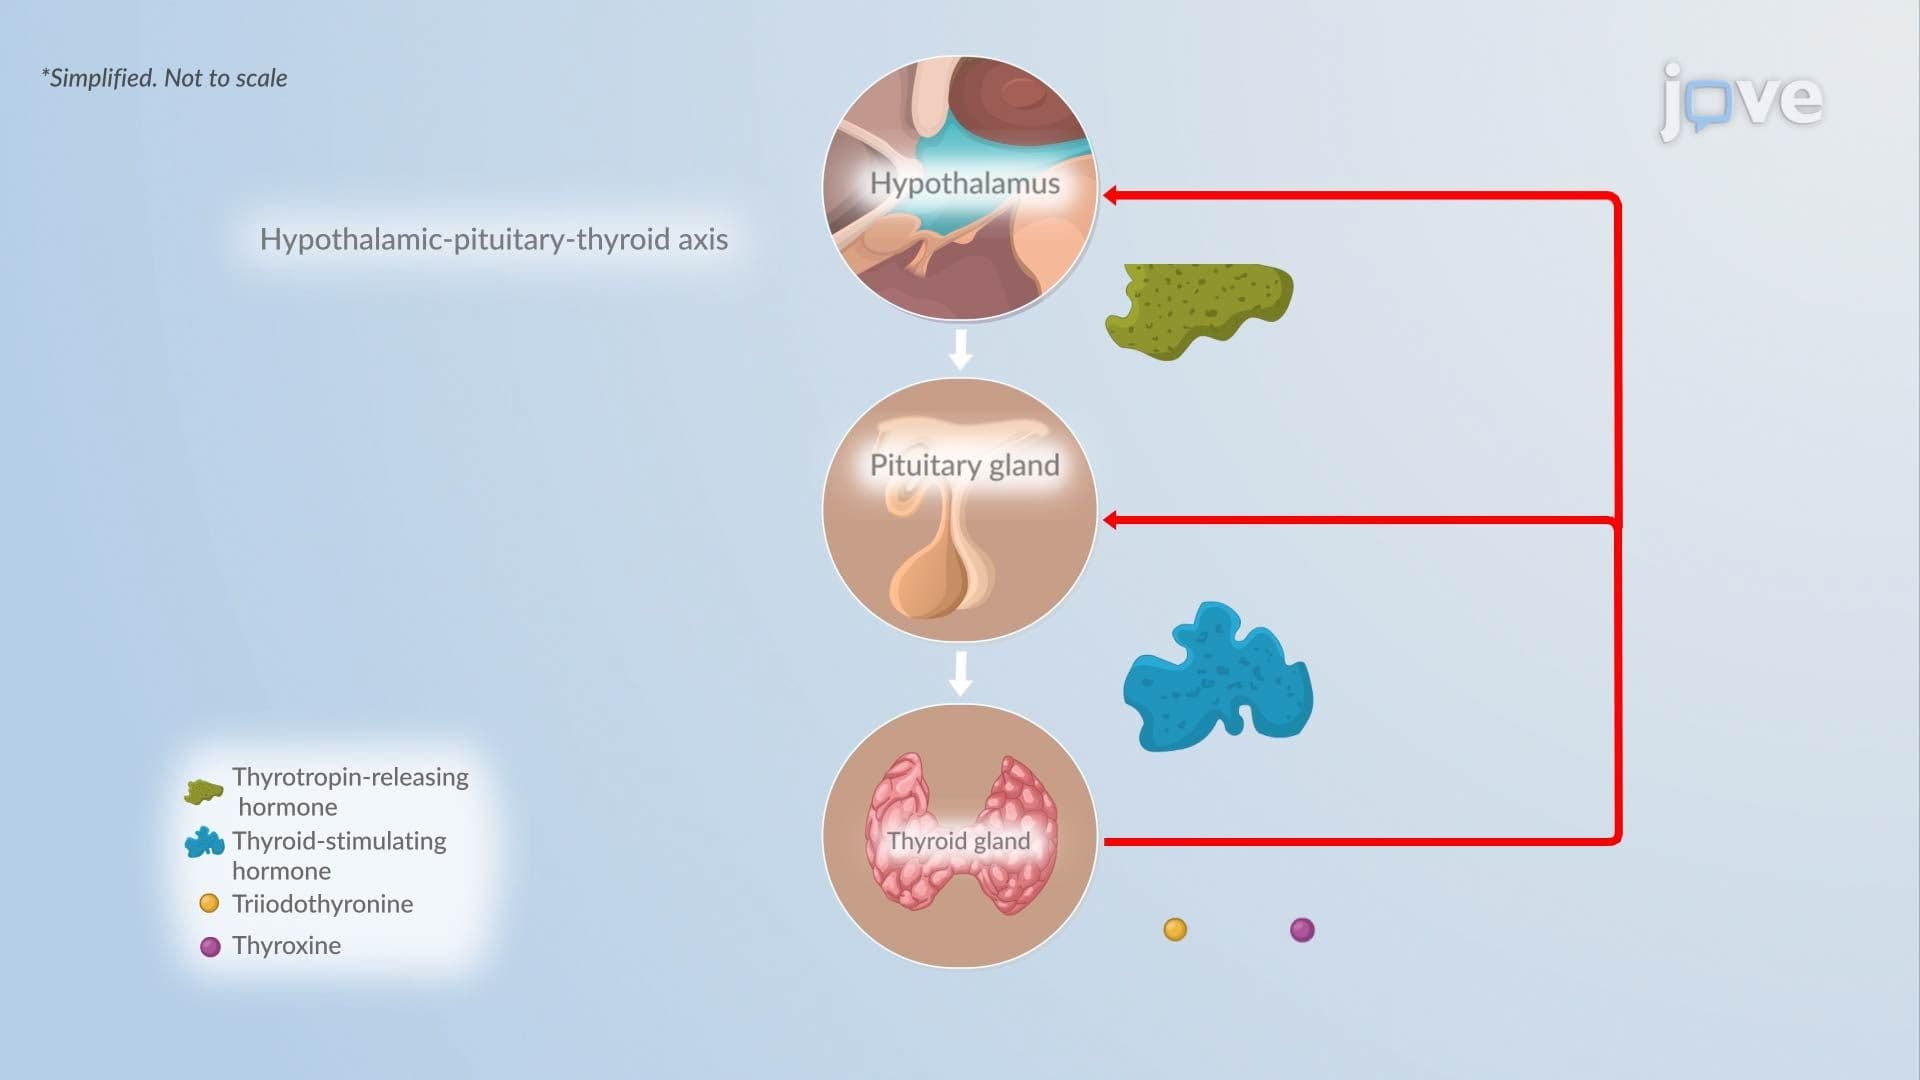
Low blood levels of the thyroid hormones — triiodothyronine (T3) and thyroxine (T4) — signal the hypothalamus to release the thyrotropin-releasing hormone (TRH). TRH then reaches the pituitary gland and stimulates the release of thyroid-stimulating hormone(TSH) into the bloodstream.
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers01:27

Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers

β-receptor blockers significantly impact the cardiovascular system by counteracting catecholamine-induced sympathetic responses. These medications decrease heart rate, contractility, and cardiac output, potentially leading to cardiac depression, life-threatening bradycardia, and death. Therapeutically, β-blockers function as mild antihypertensives and are utilized in treating angina pectoris and cardiac arrhythmias. However, nonselective β-blockers inhibit β2-receptors in bronchial smooth...
Hyperthyroidism II: Pathophysiology01:27

Hyperthyroidism II: Pathophysiology

Hyperthyroidism is a hypermetabolic state caused by elevated levels of thyroid hormones, triiodothyronine (T3) and thyroxine (T4). It results from dysregulation at the thyroid, pituitary, or immune system level and affects multiple organ systems.PathophysiologyThe most common cause of hyperthyroidism is Graves’ disease, an autoimmune disorder in which antibodies, specifically thyroid-stimulating antibodies (TSAb), a subtype of TSH receptor antibodies (TRAb), bind to and activate TSH receptors...
Dose-Response Relationship: Potency and Efficacy01:22

Dose-Response Relationship: Potency and Efficacy
The potency of a drug is the measure of its ability to produce a biological response and can be compared by looking at the half-maximum effective concentration or EC50 values of different drugs. A lower EC50 value indicates higher potency of the drug. In the dose–response curve of two antihypertensive drugs, candesartan and irbesartan, a significant difference is observed in their EC50 values. A lower EC50 value for candesartan indicates that it is more potent than irbesartan, as it produces...
Hyperthyroidism I: Introduction01:25

Hyperthyroidism I: Introduction

Hyperthyroidism is a type of thyrotoxicosis characterized by the thyroid gland's overproduction of the thyroid hormones triiodothyronine (T3) and thyroxine (T4). This hormone excess increases the basal metabolic rate and enhances sensitivity to catecholamines.DiagnosisDiagnosis is based on clinical features and biochemical testing. It typically shows suppressed thyroid-stimulating hormone (TSH) levels below 0.4 mIU/L, with elevated free T3 and/or T4. Additional tests, including thyroid...