Related Experiment Video
Updated: Jul 26, 2026


Evaluation of Coronary Flow Reserve After Myocardial Ischemia Reperfusion in Rats
Published on: June 28, 2019
Limit to cardiac compensation during acute isovolemic hemodilution: influence of coronary stenosis
1Department of Anesthesiology, Illinois Masonic Medical Center, Chicago 60657.

Insights
Cardiac compensation during hemodilution (HD) is limited by coronary stenosis. Normal circulation maintains function until maldistribution causes ischemia, while stenosis impairs adaptation, reducing tolerance to HD.
Area of Science:
- Cardiovascular Physiology
- Hemodynamics
- Myocardial Metabolism
Background:
- Isovolumetric hemodilution (HD) is used to reduce hematocrit, impacting cardiac function.
- Understanding the limits of cardiac compensation during HD is crucial for managing patients.
- Coronary artery stenosis can significantly alter the heart's response to physiological stress.
Purpose of the Study:
- To assess the limits of cardiac compensation during graded isovolemic hemodilution (HD).
- To investigate the role of coronary vasodilator reserve and transmural myocardial blood flow (MBF) distribution in maintaining cardiac function during HD.
- To compare the effects of HD on cardiac function in dogs with normal coronary arteries versus those with critical left anterior descending coronary artery (LAD) stenosis.
Main Methods:
- 14 anesthetized dogs underwent graded isovolemic HD using Hespan.
- Radioactive microspheres were used to measure myocardial blood flow (MBF) and its transmural distribution (endo/epi ratio).
- Myocardial oxygen consumption (MVO2), lactate extraction, and coronary vasodilator reserve were assessed.
Main Results:
- Cardiac failure (CF) occurred at lower hematocrit in dogs with intact LAD (9%) compared to those with LAD stenosis (17%).
- In dogs with normal LAD, MBF increased uniformly to maintain MVO2 until CF, when subendocardial ischemia occurred.
- In dogs with LAD stenosis, MBF was constant, leading to decreased MVO2 and myocardial ischemia at CF, with absent coronary vasodilator reserve.
Conclusions:
- Normal coronary circulation maintains cardiac function during HD via uniform MBF increases until extreme hemodilution causes maldistribution and subendocardial ischemia.
- Critical coronary stenosis significantly impairs the heart's ability to adapt to HD, reducing left ventricular tolerance.
- Recruitment of coronary vasodilator reserve is vital for preserving myocardial oxygenation during hemodilution.
Abstract:
We assessed limit to cardiac compensation during isovolemic hemodilution (HD) in 14 anesthetized dogs. Radioactive microspheres were used to evaluate myocardial blood flow (MBF) and its transmural distribution (endo/epi). Myocardial O2 consumption (MVO2) and percent lactate extraction were determined. Coronary vasodilator reserve was assessed from reactive hyperemic responses. Dogs were divided into group 1, with intact left anterior descending coronary artery (LAD), and group 2, with critical stenosis of LAD. Measurements were obtained at baseline and during graded HD (Hespan) until cardiac failure (CF). CF occurred at lower hematocrit in group 1 compared with group 2 (9 +/- 1 vs. 17 +/- 1%). In group 1, MBF increased during HD to maintain MVO2 constant; increases in MBF were transmurally uniform until CF, when decreased endo/epi and lactate production suggested subendocardial ischemia. Coronary vasodilator reserve decreased progressively during HD and was absent at CF. In group 2, stenotic LAD demonstrated constant MBF (resulting in decreased MVO2) during HD. At CF, these responses along with reduced endo/epi and lactate production indicated local myocardial ischemia. We conclude that 1) with normal coronary circulation, cardiac function was well maintained over a wide range of hematocrits because increases in MBF were transmurally uniform and sufficient to maintain myocardial oxygenation: CF occurred during extreme HD when MBF became maldistributed, resulting in subendocardial ischemia; 2) critical coronary stenosis impaired coronary vascular adjustment to HD and reduced significantly tolerance of left ventricle to HD; and 3) present findings underscore the importance of recruitment of coronary vasodilator reserve in preserving total and regional myocardial oxygenation during HD.

Related Concept Videos
 01:29
Pathophysiology of Cardiac Performance
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
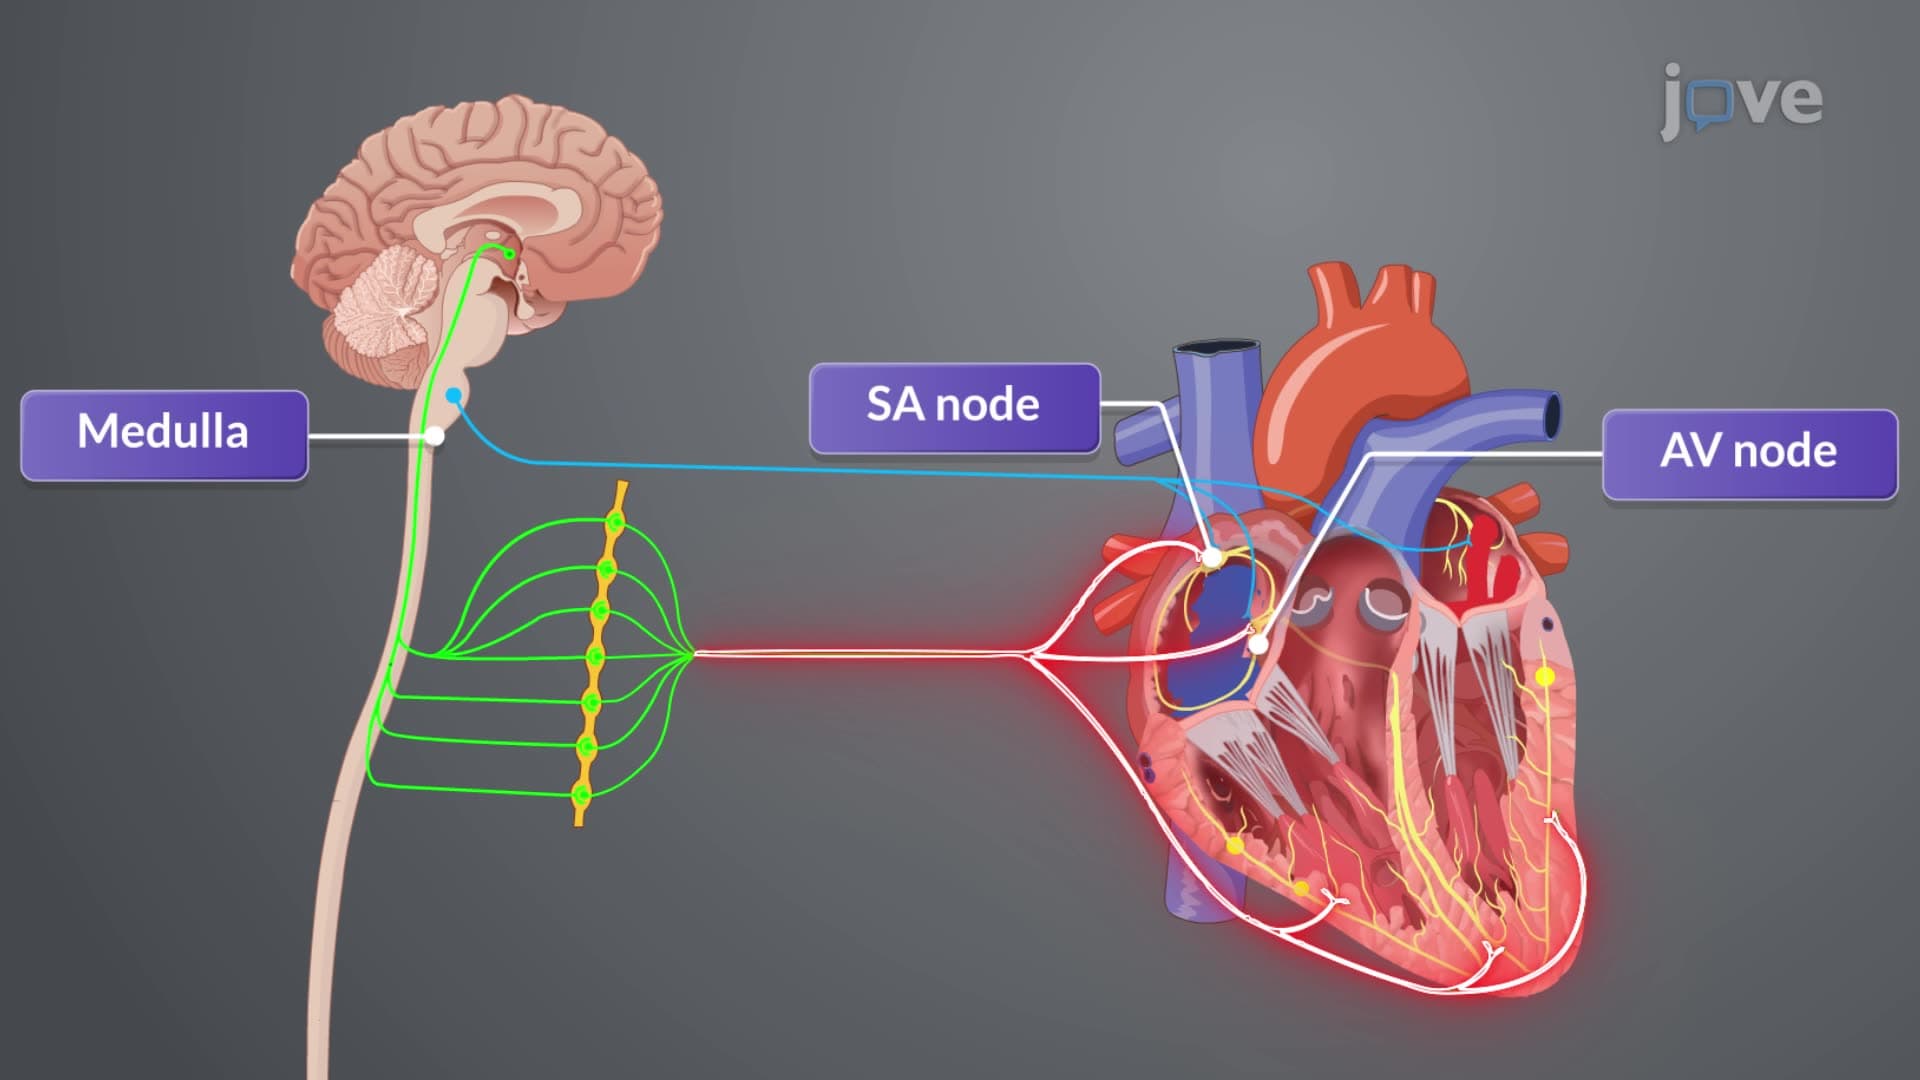
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:22
Mitral Stenosis I: Introduction
 01:29
Heart Failure II: Pathophysiology