Celiac territory ischemic syndrome in visceral artery occlusion
Related Experiment Video
Updated: Oct 13, 2026

Rodent Model of Intestinal Ischemia-Reperfusion Injury via Occlusion of the Superior Mesenteric Artery
Published on: October 20, 2023
1Section of Vascular Surgery, Westchester Medical Center, New York Medical College, Valhalla 10595.

Abstract:
Abdominal angina that is characterized by postprandial pain, and often associated with weight loss, is a well-recognized symptom complex of mesenteric artery insufficiency (mesenteric territory symptoms). In the past 5 years, we have observed six patients with atypical symptoms who had mesenteric artery occlusion combined with stenosis or occlusion of the celiac artery. Atypical symptoms included severe nausea and vomiting at the sight or smell of food, anorexia, weight loss, and right upper quadrant or epigastric discomfort (celiac territory symptoms). An extensive work-up to rule out gastric, pancreatic, biliary, or colonic pathology was undertaken in these patients. The findings included gallbladder dysfunction, diffuse micro-ulceration of gastric mucosa, and colonic mucosal ulceration. The diagnosis of visceral artery occlusion was initially missed in all six patients. Four patients had cholecystectomy. Visceral angiography confirmed occlusion of the celiac, superior, and inferior mesenteric arteries. Five patients had dramatic resolution of symptoms after restoration of visceral circulation. One patient who developed intestinal infarction before revascularization died. Symptoms suggesting upper abdominal visceral pathology may be a manifestation of celiac artery stenosis/occlusion coexisting with mesenteric artery occlusive disease. Visceral angiography should be part of the work-up in these patients for early diagnosis and prompt management.

Related Concept Videos
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:26
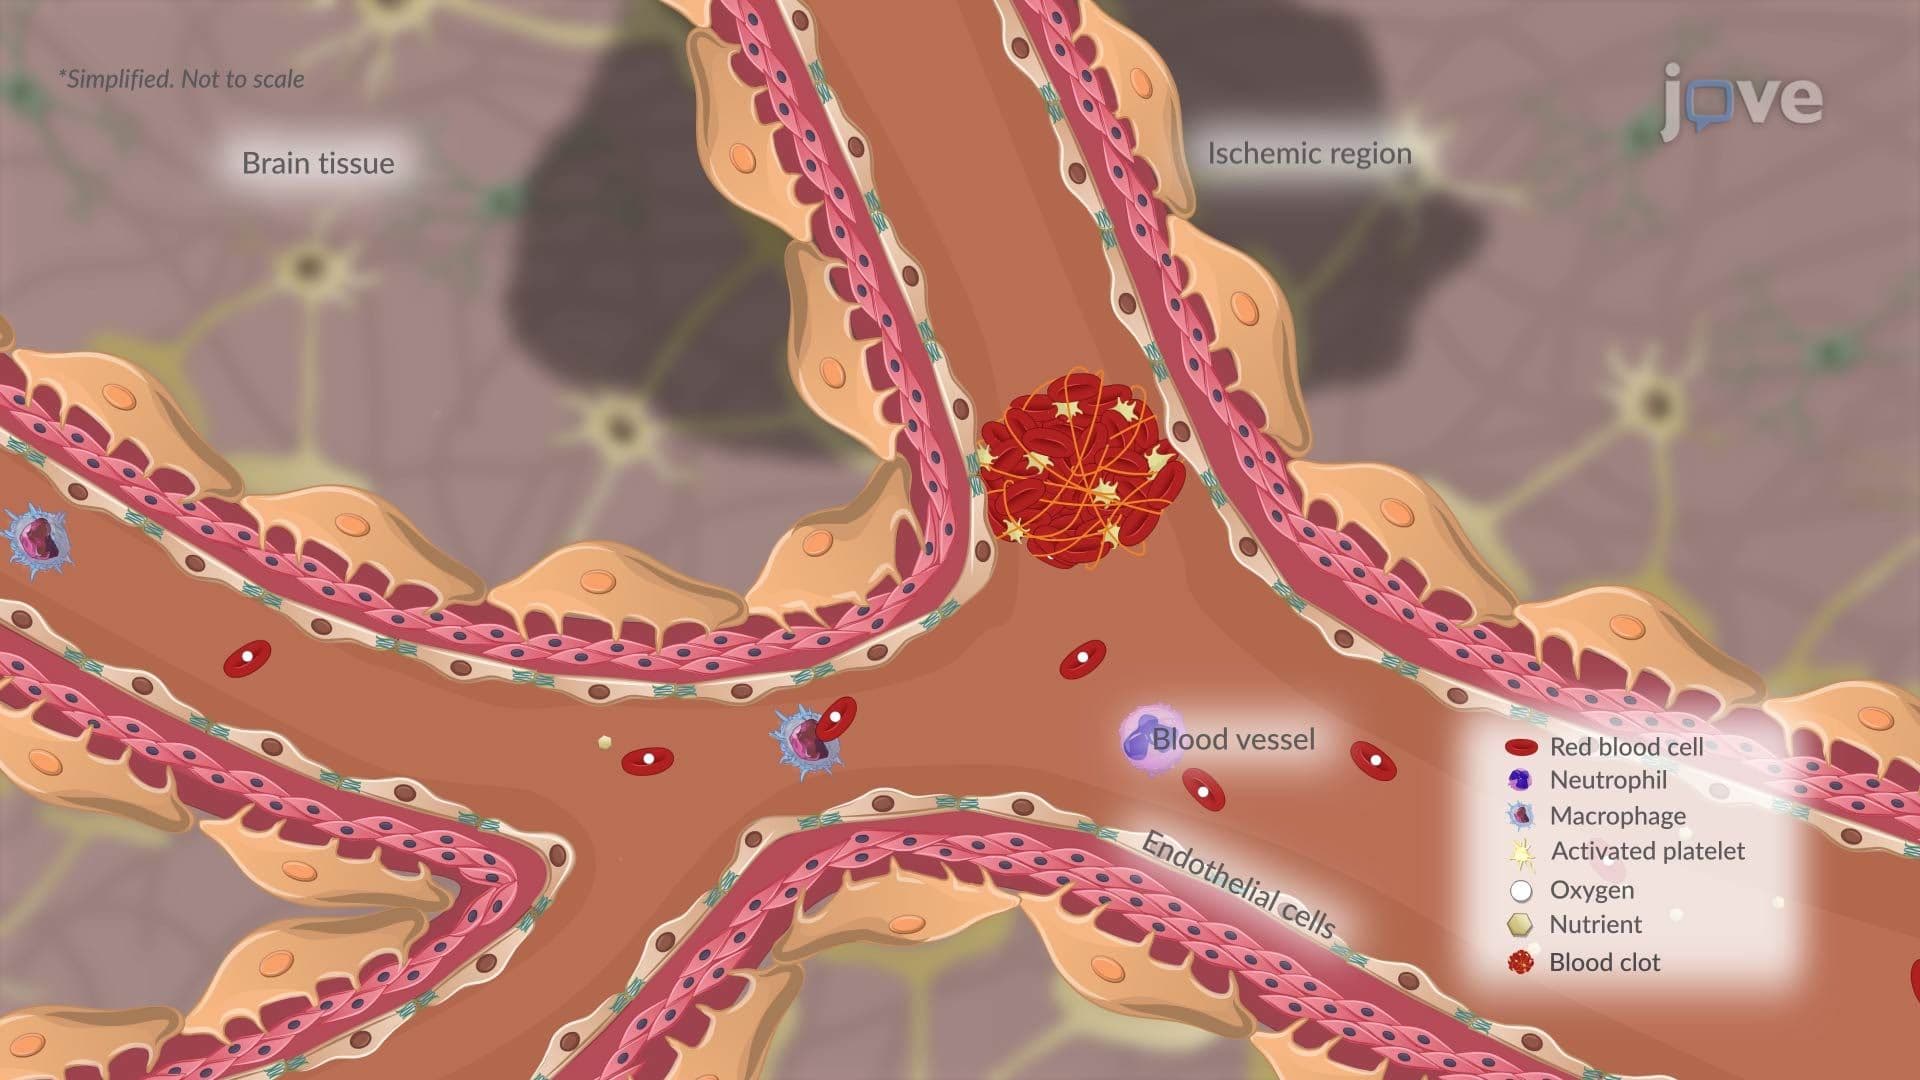
Transient Ischemic Attack l: Introduction
 01:26
Gastritis II: Pathophysiology
 01:11
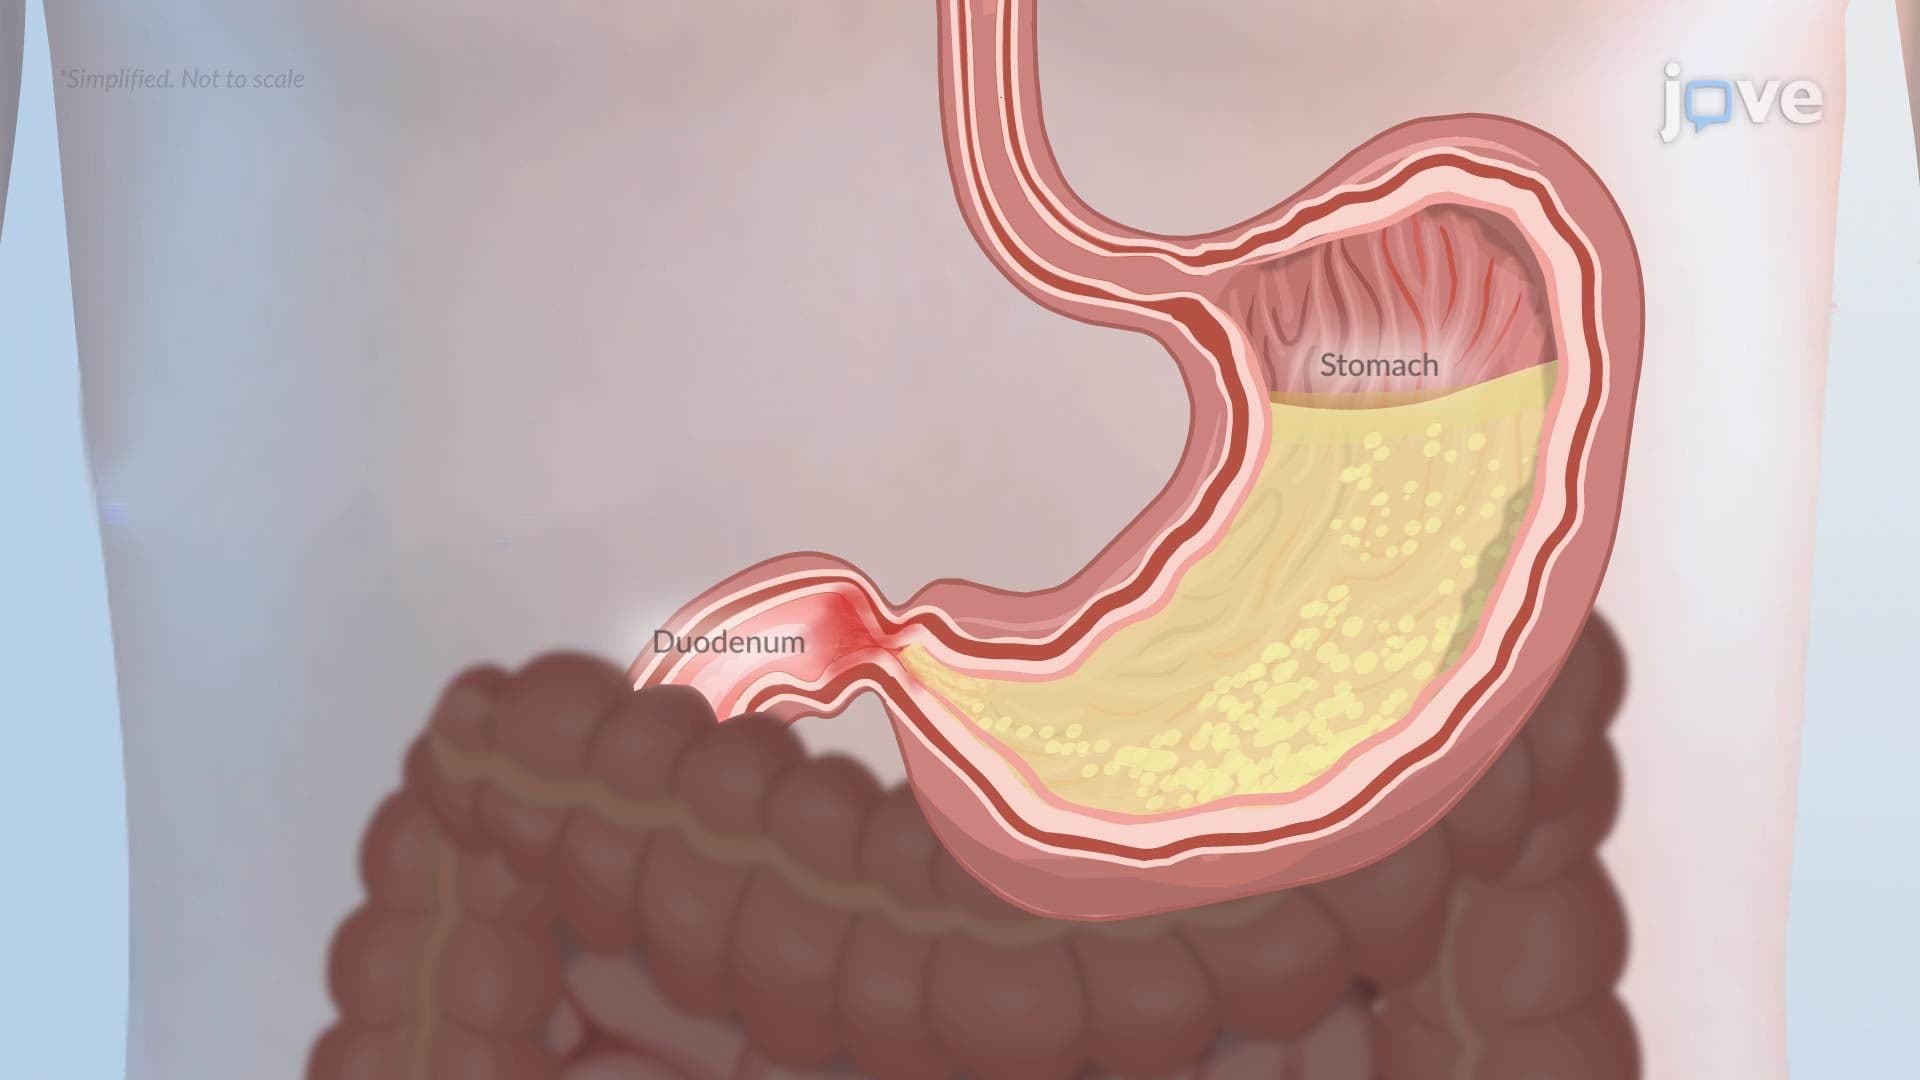
Pyloric Obstruction
 01:07
Intestinal Obstruction II: Pathophysiology