Related Experiment Video
Updated: Sep 29, 2026


Scanning Electron Microscopy of Macerated Tissue to Visualize the Extracellular Matrix
Published on: June 14, 2016
A role of fatty acid oxidation in cardiac hypertrophy
1Department of Medicine, University of Arizona Health Sciences Center, Tucson.

Insights
Inducing myocardial hypertrophy with a carnitine palmitoyl transferase I inhibitor helped prevent pathological heart dilation after a large myocardial infarction in rats. This intervention improved systolic function and reduced heart enlargement.
Area of Science:
- Cardiology
- Molecular Biology
- Pharmacology
Background:
- Myocardial infarction (MI) can lead to pathological cardiac remodeling, including left ventricular (LV) dilation, increasing risks of arrhythmias, heart failure, and sudden death.
- Infarctions exceeding 20% of the LV induce minimal compensatory hypertrophy, leading to increased filling pressures and dilation.
- Inadequate myocardial hypertrophy post-MI is hypothesized to drive progressive LV dilation.
Purpose of the Study:
- To investigate if inducing additional myocardial hypertrophy using 2-tetradecylglycidic acid (TDGA) can prevent pathological LV dilation after a large MI in rats.
- To assess the effects of TDGA-induced hypertrophy on cardiac function following a significant myocardial infarction.
Main Methods:
- Rats underwent a large myocardial infarction (50% of LV).
- Experimental groups received oral administration of 2-tetradecylglycidic acid, an inhibitor of carnitine palmitoyl transferase I, for 10 days post-infarction.
- Hemodynamic parameters, including peak developed LV pressure, LV end-diastolic volume, and stroke volume, were measured.
Main Results:
- TDGA treatment induced myocardial hypertrophy in both control and infarcted rats.
- Infarcted rats treated with TDGA exhibited increased peak developed LV pressure and reduced LV end-diastolic volumes compared to untreated infarcted rats.
- Stroke volume was maintained in the TDGA-treated infarcted group.
Conclusions:
- Pharmacological induction of myocardial hypertrophy using a long-chain fatty acid oxidation inhibitor (TDGA) mitigated LV dilation post-large MI.
- This approach demonstrated beneficial effects on systolic function, suggesting a potential therapeutic strategy for post-MI cardiac remodeling.
Abstract:
Following a myocardial infarction the patient with a dilated heart is at greater risk for arrhythmias, congestive failure and sudden death. Studies of myocardial infarction in experimental animals have shown that, with infarcts involving up to 20% of the left ventricle, hypertrophy of surviving myocytes occurs and there are minimal hemodynamic changes. Infarctions greater than 20% induce little additional hypertrophy, and develop increased left ventricular filling pressures and cardiac dilatation. It has been suggested that inadequate hypertrophy of residual myocardium may be a reason for the progressive left ventricular dilatation which occurs after large myocardial infarcts. There are data in humans and animals suggesting that the mass of the left ventricle following a myocardial infarction correlates with improvement in systolic function. Studies from our laboratories have previously shown that 2-tetradecylglycidic acid, an inhibitor of carnitine palmitoyl transferase I, inhibits mitochondrial long-chain fatty acid oxidation and causes myocardial hypertrophy when given to rats by mouth for 7-28 days. We carried out studies to see whether induction of additional myocardial hypertrophy by means of feeding tetradecylglycidic acid might prevent pathologic dilation following a large (50%) infarct in rats. Treatment of control and infarcted rats with tetradecylglycidic acid for 10 days resulted in myocardial hypertrophy in both groups. The rats with myocardial infarction treated with tetradecylglycidic acid had an increase in peak developed left ventricular pressure during abrupt aortic occlusion and lower left ventricular end-diastolic volumes, when compared to untreated rats with myocardial infarction, while the stroke volume was maintained. Thus induction of myocardial hypertrophy with an inhibitor of long-chain fatty acid oxidation retarded the process of left ventricular dilatation and had beneficial effects on systolic function following a large myocardial infarction.

Related Concept Videos
 01:28
Overview of Fatty Acid Metabolism
Fatty acids are catabolized in a process called beta-oxidation, which takes place in the matrix of the mitochondria and converts their fatty acid chains into two-carbon units of acetyl groups. The acetyl...
 01:13
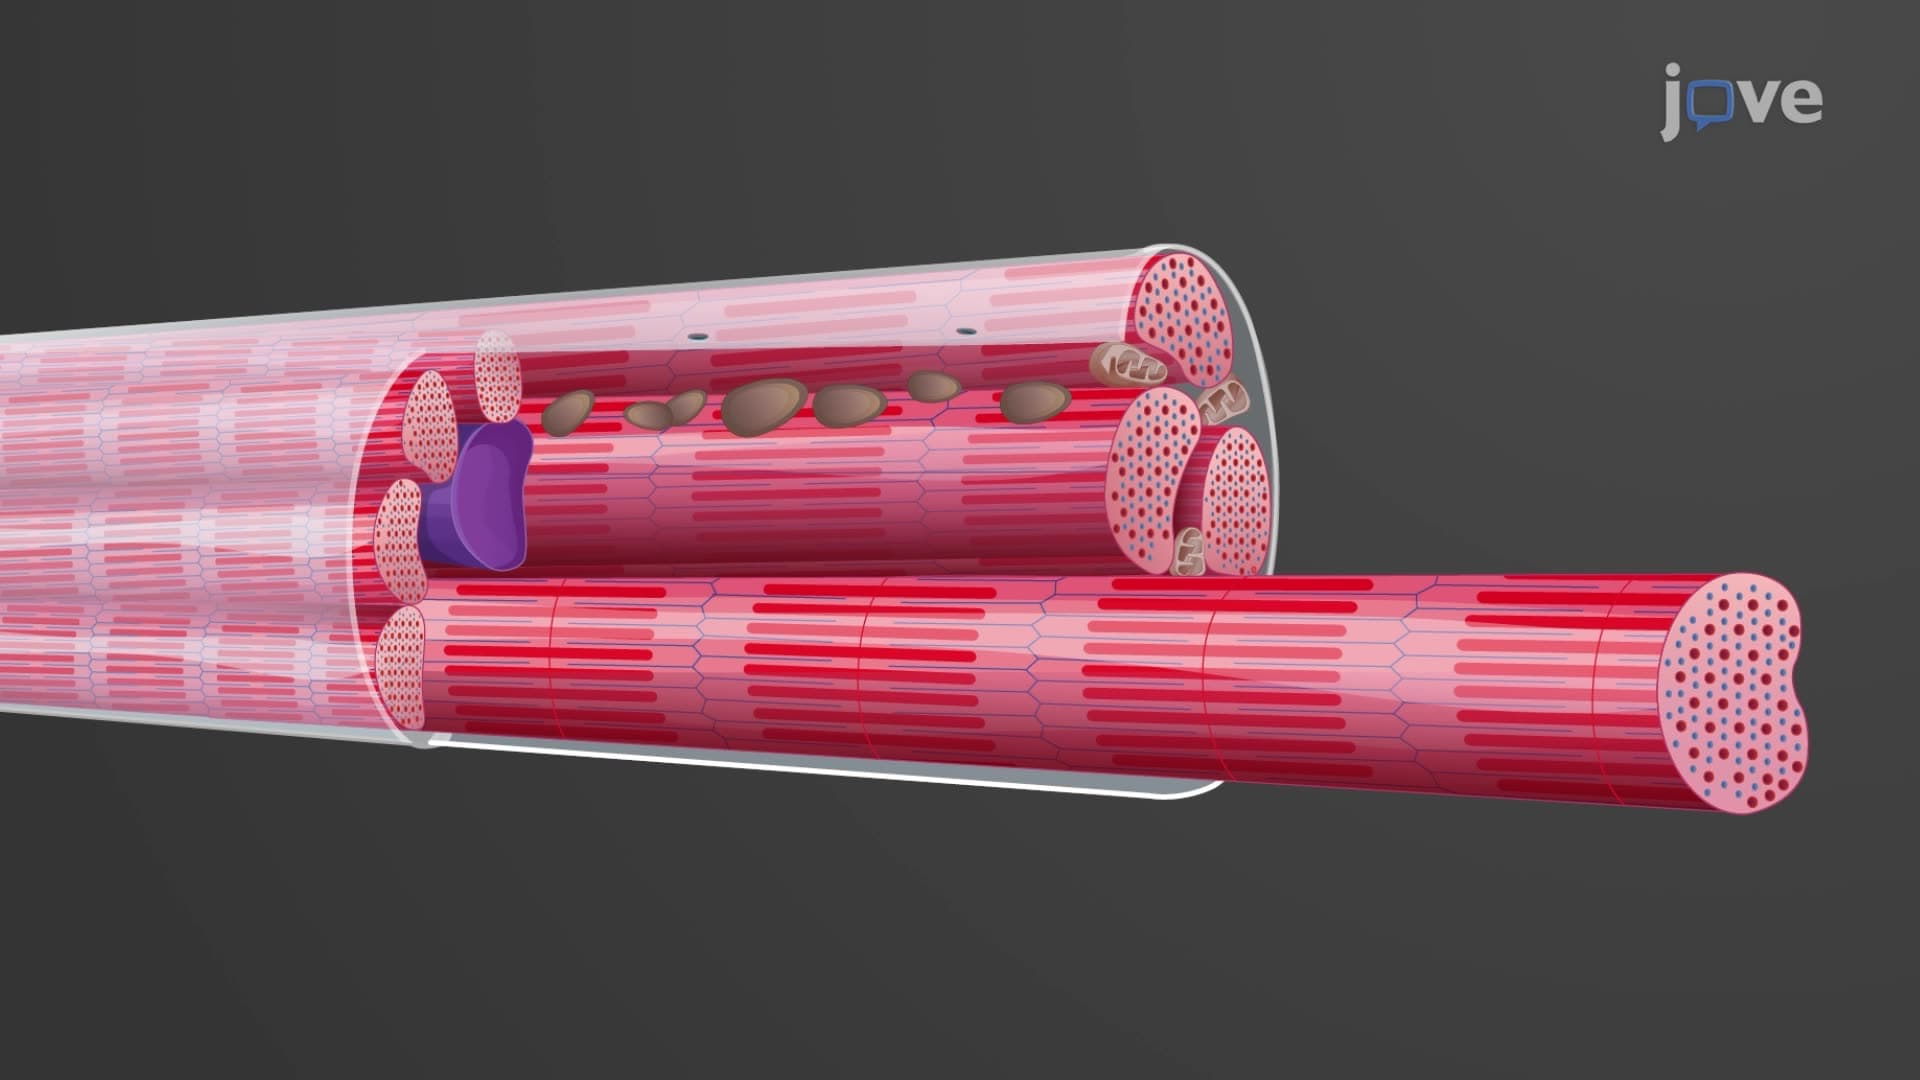
Structure of Cardiac Muscles
Compared to skeletal muscles, cardiac muscle cells are small and mostly have a single nucleus. Additionally, they are usually...
 01:17
Pathophysiology of Heart Failure
 01:29
Heart Failure II: Pathophysiology
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:26
Cellular Adaptation II: Hypertrophy