Increased leukocyte elastase of the tracheal aspirate at birth and neonatal pulmonary emphysema
Related Experiment Video
Updated: Aug 19, 2026
Noninvasive Sampling of Mucosal Lining Fluid for the Quantification of In Vivo Upper Airway Immune-mediator Levels
Published on: August 7, 2017
M Fujimura1, H Kitajima, M Nakayama
1Department of Neonatal Medicine, Osaka Medical Center, Japan.

Objective:
The authors have previously shown the association of elevated neonatal serum IgM and chorioamnionitis in infants in whom pulmonary emphysema characteristic of Wilson-Mikity syndrome subsequently developed. This paper extends the observation to the measurement of polymorphonuclear leukocyte elastase-alpha 1-proteinase inhibitor complex (PMN elastase-alpha 1-PI) in tracheal aspirates of infants with chronic lung disease.
Patients:
Tracheal aspirates were obtained from 90 very low birth weight neonates within 24 hours of birth. Serum also was collected within 72 hours of birth, and placentas were examined for signs of inflammation.
Results:
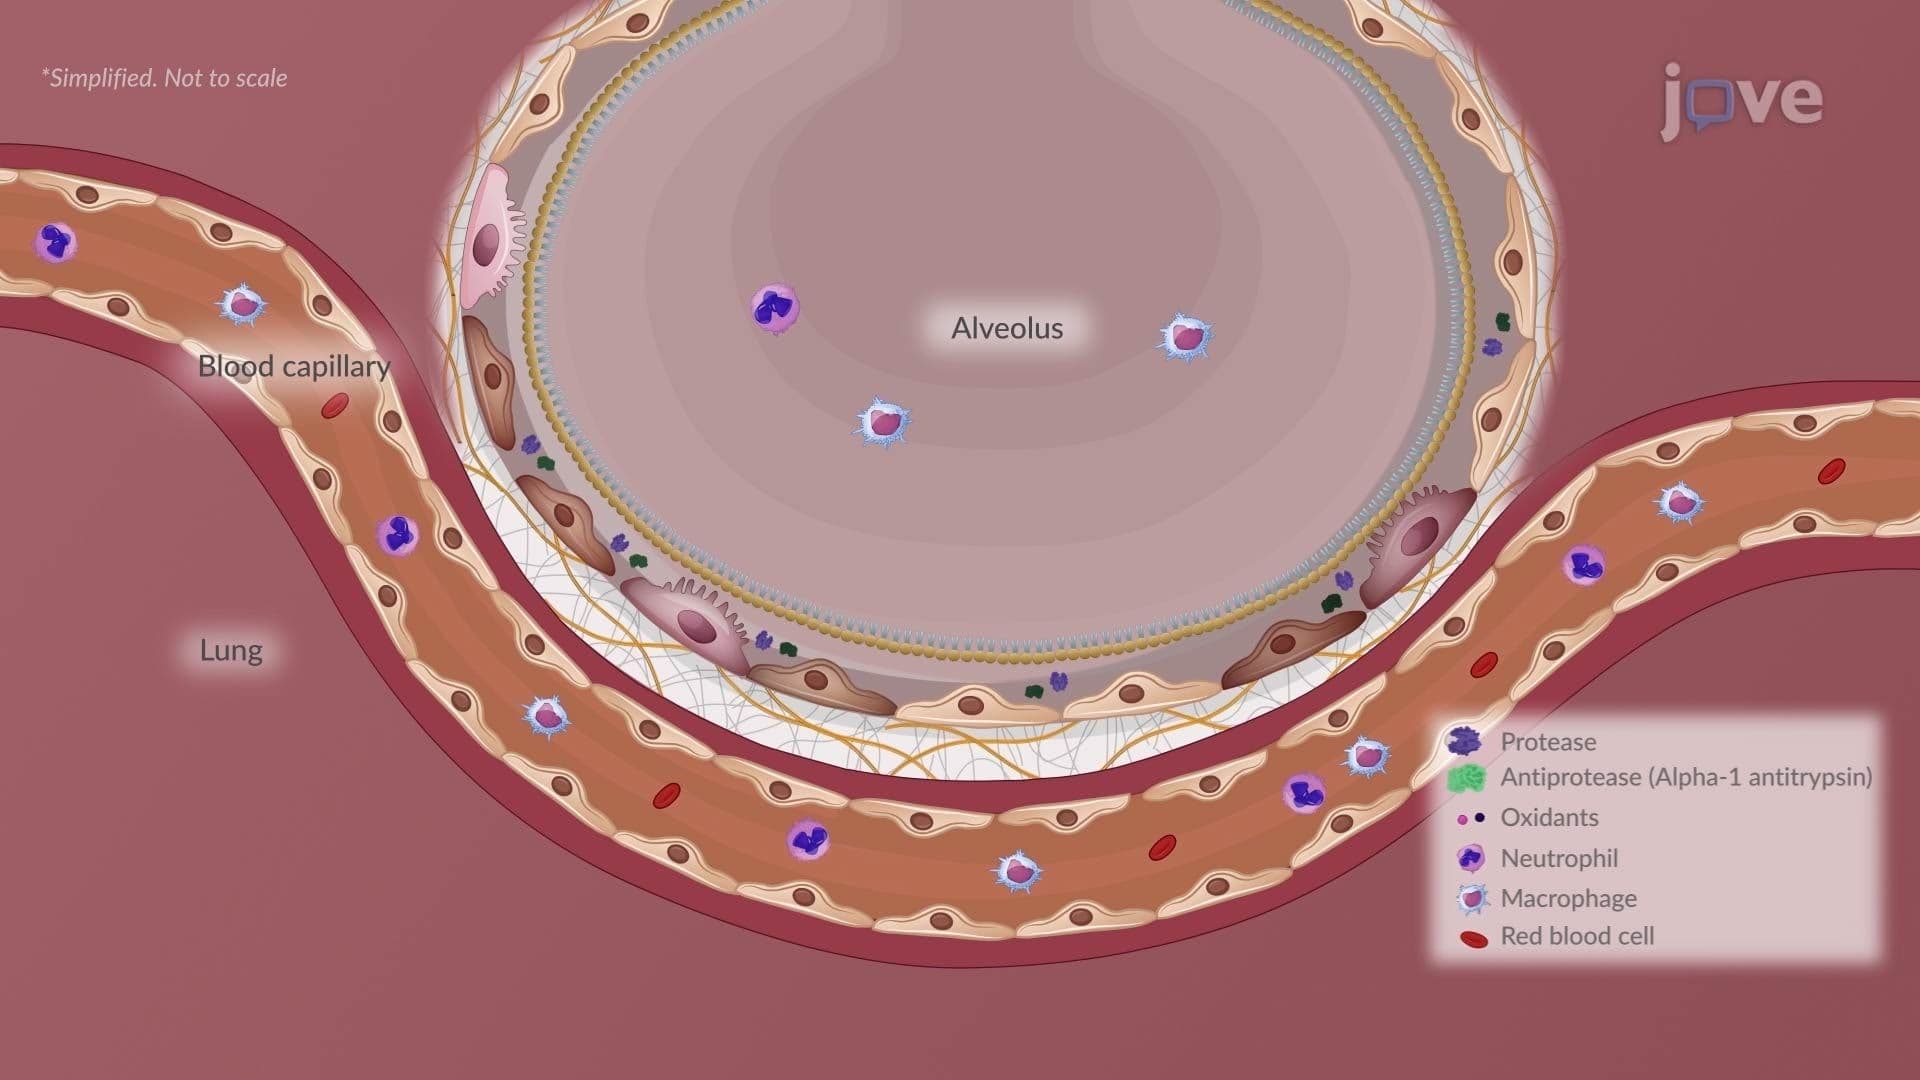
The mean PMN elastase-alpha 1-PI was significantly elevated (21.8 micrograms/mg albumin) in infants with a pulmonary emphysema syndrome like that designated by Wilson-Mikity compared either with those with bronchopulmonary dysplasia (1.5 micrograms/mg albumin, P < .01) or those with respiratory distress syndrome in whom bronchopulmonary dysplasia did not develop (2.3 micrograms/mg albumin, P < .01). Infants with pulmonary emphysema had a significantly elevated mean serum IgM and a high incidence of chorioamnionitis.
Conclusions:
The level of PMN elastase-alpha 1-PI was increased in the tracheal aspirates of newborns in whom pulmonary emphysema developed. Intrauterine inflammation may increase the level of PMN elastase in the fetal respiratory tract. This increase in PMN elastase-alpha 1-PI in fetal lung tissue may cause lung injury in utero, resulting in postnatal pulmonary emphysema consistent with the Wilson-Mikity syndrome following ventilation.

Related Concept Videos
 01:05
Breathing
 01:17
Pulmonary Cycle: Exhalation
 01:29
Microbiota of the Respiratory Tract
 01:10
Atelectasis II: Pathophysiology
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:18
Pulmonary Edema II: Pathophysiology