Development of postmolar trophoblastic disease after partial molar pregnancy
Related Experiment Video
Updated: Nov 7, 2026

Microsatellite DNA Genotyping and Flow Cytometry Ploidy Analyses of Formalin-fixed Paraffin-embedded Hydatidiform Molar Tissues
Published on: October 20, 2019
1Department of Obstetrics and Gynecology, School of Medicine, Nagoya University, Japan.

We investigated the clinical characteristics of patients with partial molar pregnancy and patients who developed invasive partial mole. Between 1981 and 1990, 349 patients were followed up by the Aichi prefecture trophoblastic disease registration center after partial molar pregnancy. Ten of the 349 patients with partial molar pregnancy developed invasive partial mole, an incidence (2.87%) significantly lower (P < 0.01) than that for the development of invasive complete mole (174/1410, 12.34%) following complete molar pregnancy during the same period. None of the patients had any histologic evidence of choriocarcinoma after partial molar pregnancy. The medical records of these 10 patients were compared with those of 85 of 174 registered patients with invasive complete mole, whose clinical information could be used. The interval from molar delivery to the diagnosis of invasive mole was under 9 weeks (mean, 4.90 weeks) for the patients with invasive partial mole and was significantly shorter than that for the patients with invasive complete mole, from 2 to 18 weeks (mean, 8.12 weeks) (P < 0.01). All 10 patients with invasive partial mole achieved a negative hCG level (< 0.5 mIU/ml) with eight courses or less of chemotherapy (mean, 5.50 courses). The number of courses was the same as that in the invasive complete mole group (mean, 5.70 courses). None of the patients with invasive partial mole developed recurrence. We conclude that all patients with partial molar pregnancy should be followed up as are those with complete molar pregnancy. Some patients with partial molar pregnancy will develop invasive partial mole with a relatively short interval, but remission can be achieved without the recurrence and choriocarcinoma seldom develops after partial molar pregnancy.
We investigated the clinical characteristics of patients with partial molar pregnancy and patients who developed invasive partial mole. Between 1981 and 1990, 349 patients were followed up by the Aichi prefecture trophoblastic disease registration center after partial molar pregnancy. Ten of the 349 patients with partial molar pregnancy developed invasive partial mole, an incidence (2.87%) significantly lower (P < 0.01) than that for the development of invasive complete mole (174/1410, 12.34%) following complete molar pregnancy during the same period. None of the patients had any histologic evidence of choriocarcinoma after partial molar pregnancy. The medical records of these 10 patients were compared with those of 85 of 174 registered patients with invasive complete mole, whose clinical information could be used. The interval from molar delivery to the diagnosis of invasive mole was under 9 weeks (mean, 4.90 weeks) for the patients with invasive partial mole and was significantly shorter than that for the patients with invasive complete mole, from 2 to 18 weeks (mean, 8.12 weeks) (P < 0.01). All 10 patients with invasive partial mole achieved a negative hCG level (< 0.5 mIU/ml) with eight courses or less of chemotherapy (mean, 5.50 courses). The number of courses was the same as that in the invasive complete mole group (mean, 5.70 courses). None of the patients with invasive partial mole developed recurrence. We conclude that all patients with partial molar pregnancy should be followed up as are those with complete molar pregnancy. Some patients with partial molar pregnancy will develop invasive partial mole with a relatively short interval, but remission can be achieved without the recurrence and choriocarcinoma seldom develops after partial molar pregnancy.

Related Concept Videos
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...
 01:15
Teeth
In the bud stage, the tooth germ (an aggregation of cells) starts to form in the developing jawbone. During the cap stage, the tooth germ differentiates into enamel organ, dental papilla, and dental sac, which will later develop into the tooth's enamel, dentin and...
 02:07
Oogenesis
 01:19
Mitral Valve Prolapse III: Nursing Management
 02:57
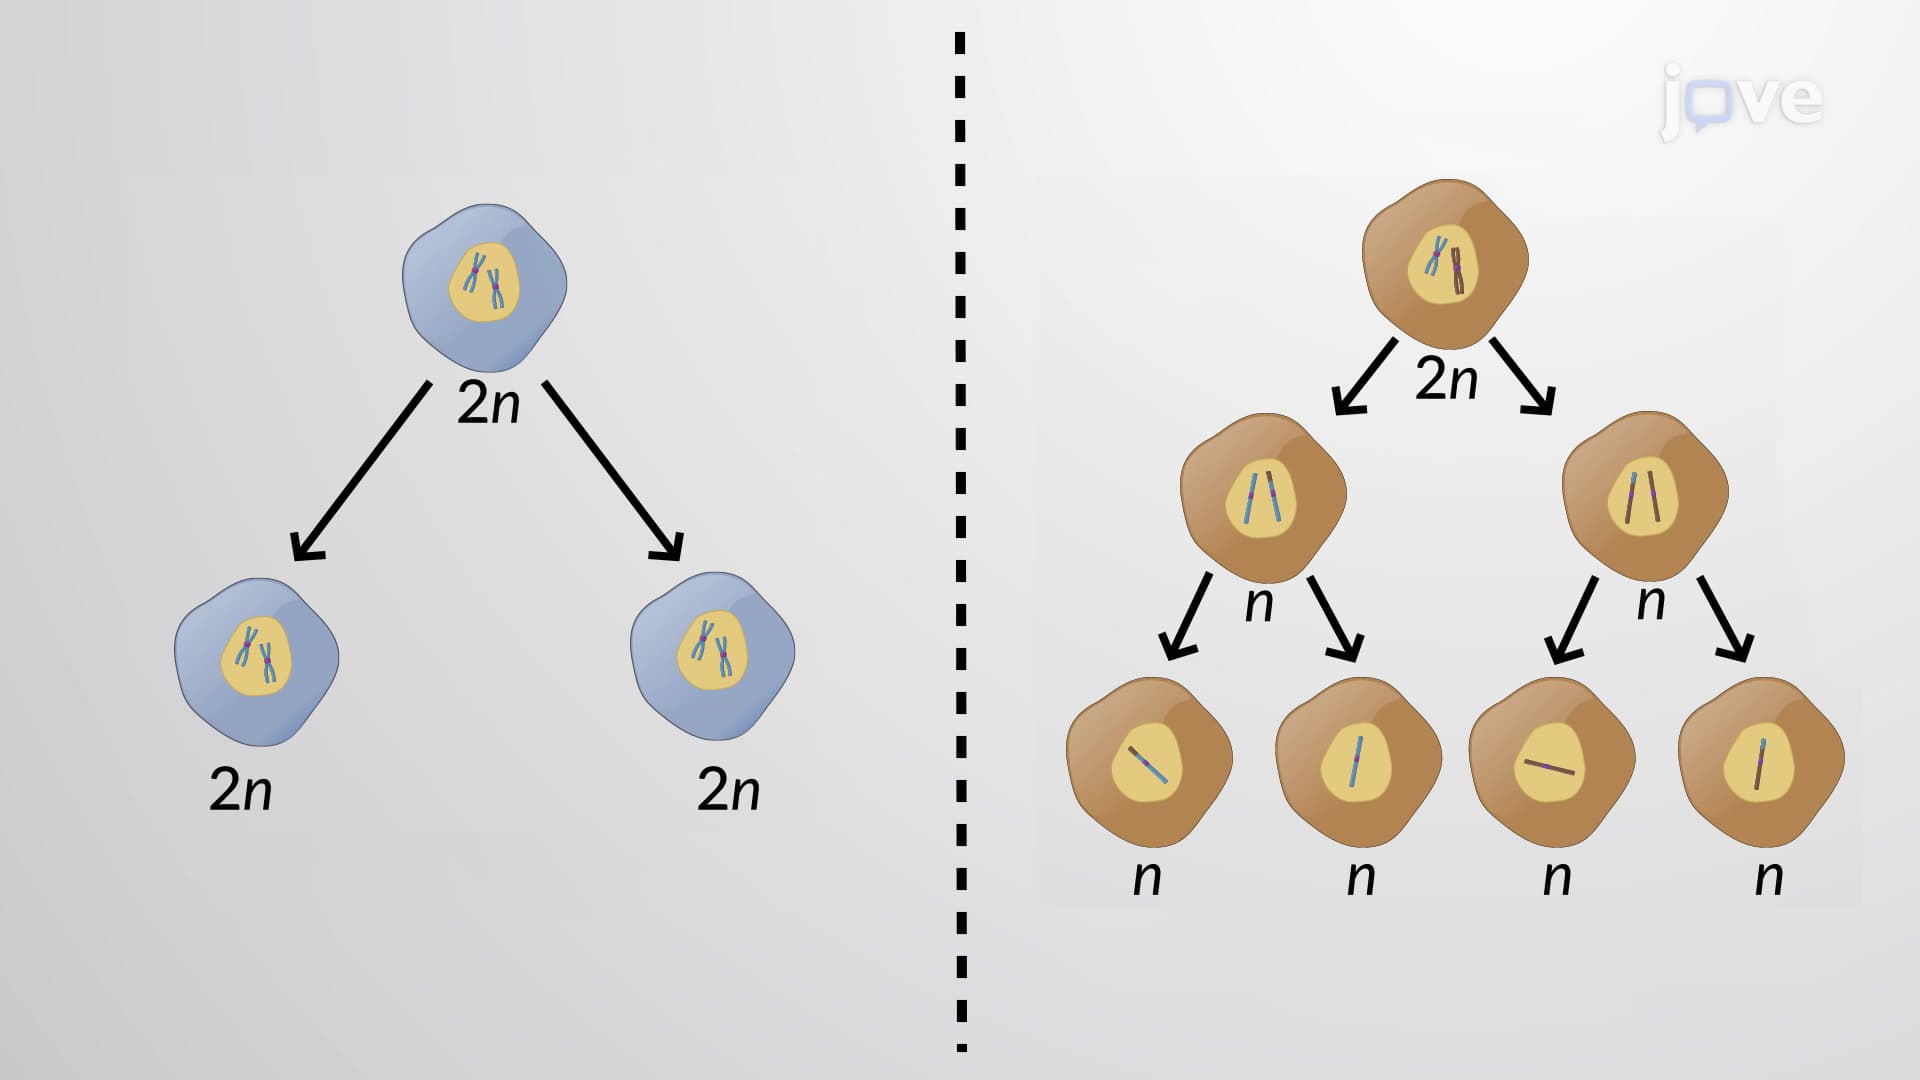
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:07
Teratogenicity