Related Experiment Video
Updated: May 6, 2026
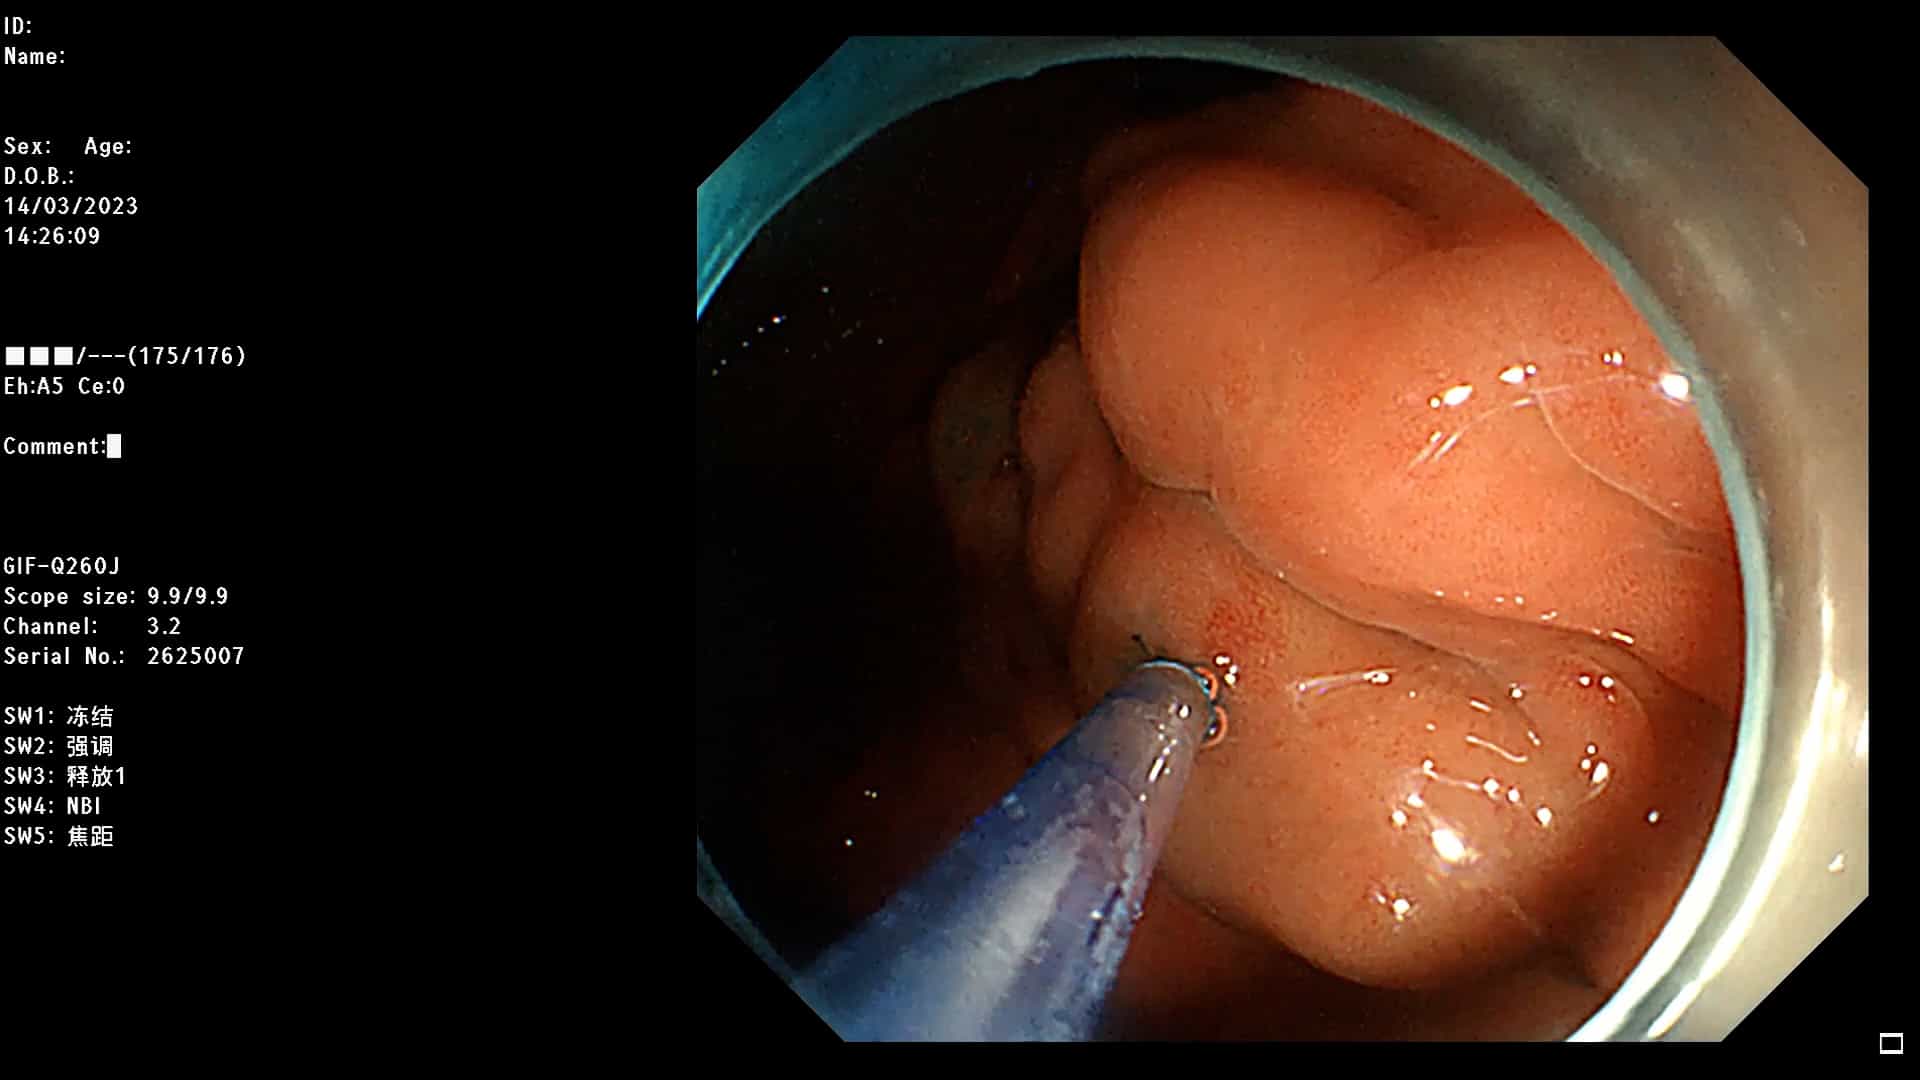
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Complications and limitations of injection sclerotherapy in portal hypertension
1Department of Surgery, King's College Hospital, London.

Injection sclerotherapy is now the accepted first line treatment for bleeding oesophageal varices, although it is associated with an impressive list of rare complications. The main problem concerns the strategy for uncontrollable or recurrent bleeding. Patients with uncontrolled bleeding may be referred for surgery after considerable blood loss and are then extremely difficult to assess. The effects of blood loss on liver function can lead to an unduly pessimistic assessment of liver status. An effective choice of emergency surgical procedure may require considerable surgical expertise. Oesophageal transection and devascularisation are satisfactory for many patients with oesophageal varices secondary to cirrhosis and should nearly always control bleeding. Difficulties arise in patients who are grossly obese and in those who have undergone extensive surgery in the upper abdomen. Problems may also be encountered in those treated by repeated sclerotherapy, which may have caused severe inflammatory change and thickening around the lower oesophagus and upper stomach. We believe that an emergency mesocaval shunt using either a vein graft or a synthetic material such as polytetrafluoroethylene is the procedure of choice for this difficult group of very sick patients. The surgical exposure is satisfactory and not unduly prolonged in even the largest patients and the technique does not interfere with any subsequent transplant operation. There is a greater choice in the management of the patient with less urgent bleeding from recurrent varices after sclerotherapy. Repeat sclerotherapy may be effective for small oesophageal varices while liver transplantation may be indicated in the patient with deteriorating liver function. A selective distal splenorenal shunt should be considered for patients with intact splenic and left renal veins and a mesocaval vein graft for the remainder. We would therefore suggest that surgery should still be considered for the management of portal hypertension, particularly in the following circumstances: (1) Uncontrollable bleeding during the initial course of sclerotherapy; (2) Life threatening haemorrhage from recurrent varices; (3) Bleeding from ectopic varices not accessible to sclerotherapy; (4) Uncontrollable bleeding from oesophageal ulceration secondary to injection sclerotherapy; (5) Severe, symptomatic hypersplenism; (6) For patients who live in communities remote from blood transfusion facilities and adequate medical care. The management of the complications of portal hypertension continues to pose problems. We believe that the best results should come from a combined management approach using injection sclerotherapy as primary treatment and surgery for complications and for haemorrhage from unusual anatomical sites.
Injection sclerotherapy is now the accepted first line treatment for bleeding oesophageal varices, although it is associated with an impressive list of rare complications. The main problem concerns the strategy for uncontrollable or recurrent bleeding. Patients with uncontrolled bleeding may be referred for surgery after considerable blood loss and are then extremely difficult to assess. The effects of blood loss on liver function can lead to an unduly pessimistic assessment of liver status. An effective choice of emergency surgical procedure may require considerable surgical expertise. Oesophageal transection and devascularisation are satisfactory for many patients with oesophageal varices secondary to cirrhosis and should nearly always control bleeding. Difficulties arise in patients who are grossly obese and in those who have undergone extensive surgery in the upper abdomen. Problems may also be encountered in those treated by repeated sclerotherapy, which may have caused severe inflammatory change and thickening around the lower oesophagus and upper stomach. We believe that an emergency mesocaval shunt using either a vein graft or a synthetic material such as polytetrafluoroethylene is the procedure of choice for this difficult group of very sick patients. The surgical exposure is satisfactory and not unduly prolonged in even the largest patients and the technique does not interfere with any subsequent transplant operation. There is a greater choice in the management of the patient with less urgent bleeding from recurrent varices after sclerotherapy. Repeat sclerotherapy may be effective for small oesophageal varices while liver transplantation may be indicated in the patient with deteriorating liver function. A selective distal splenorenal shunt should be considered for patients with intact splenic and left renal veins and a mesocaval vein graft for the remainder. We would therefore suggest that surgery should still be considered for the management of portal hypertension, particularly in the following circumstances: (1) Uncontrollable bleeding during the initial course of sclerotherapy; (2) Life threatening haemorrhage from recurrent varices; (3) Bleeding from ectopic varices not accessible to sclerotherapy; (4) Uncontrollable bleeding from oesophageal ulceration secondary to injection sclerotherapy; (5) Severe, symptomatic hypersplenism; (6) For patients who live in communities remote from blood transfusion facilities and adequate medical care. The management of the complications of portal hypertension continues to pose problems. We believe that the best results should come from a combined management approach using injection sclerotherapy as primary treatment and surgery for complications and for haemorrhage from unusual anatomical sites.
Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:23
Cirrhosis I: Introduction
 01:24
Cirrhosis II: Pathophysiology
 01:22
Portal Hypertension