Related Experiment Videos
Q fever in children
J Ruiz-Contreras1, R González Montero, J T Ramos Amador
1Departamento de Pediatriá, Hospital 12 de Octubre, Universidad Complutense de Madrid, Spain.

Insights
Q fever in children typically presents as a self-limited illness with high fever and gastrointestinal issues. Early antibody testing for Coxiella burnetii is recommended for suspected pediatric Q fever cases.
Area of Science:
- Pediatrics
- Infectious Diseases
- Microbiology
Background:
- Q fever is a zoonotic disease caused by Coxiella burnetii.
- Clinical presentation in children is not well-defined.
- Understanding pediatric Q fever profiles aids diagnosis and management.
Purpose of the Study:
- To delineate the clinical characteristics of Q fever in pediatric patients.
- To identify key diagnostic indicators for childhood Q fever.
Main Methods:
- Retrospective analysis of medical records from a tertiary teaching hospital.
- Inclusion of thirteen children aged 2-14 years diagnosed with Q fever.
- Diagnosis confirmed by detecting phase II antibodies to Coxiella burnetii via complement fixation test.
Main Results:
- The illness was self-limited, marked by high fever (mean 39.9°C) lasting 5-10 days.
- Common symptoms included constitutional complaints and mild liver dysfunction; gastrointestinal issues were prevalent.
- Respiratory symptoms were minimal, with mostly normal or low white blood cell counts and elevated erythrocyte sedimentation rates.
Conclusions:
- Pediatric Q fever typically manifests with fever and gastrointestinal symptoms.
- Testing for Coxiella burnetii antibodies is crucial for children presenting with these clinical features.
- Children generally recover well without specific anti-Coxiella burnetii therapy.
Objective:
To describe clinical profiles of Q fever in children.
Design:
Retrospective study.
Setting:
Tertiary teaching hospital.
Participants:
Thirteen children aged 2 to 14 years, with a mean +/- SD age of 9.6 +/- 3.6 years.
Selection Procedures:
Review of the medical records of all children with Q fever admitted from 1986 to 1990. The diagnosis was made by detection of phase II antibodies to Coxiella burnetii by the complement fixation test.
Measurements/Main Results:
Clinical profiles consisted of a self-limited illness characterized by high fever (mean +/- SD, 39.9 degrees C +/- 0.66 degrees C) of 5 to 10 days' duration (mean +/- SD, 7.4 +/- 1.6 days), constitutional symptoms, and mild liver dysfunction. Eleven patients had gastrointestinal manifestations (vomiting and/or abdominal pain). Respiratory symptoms were not prominent. Most patients had normal or low white blood cell counts, and seven showed a relative increase of band forms. Their erythrocyte sedimentation rates ranged from 8 to 23 mm/h. All patients did well without specific therapy for C burnetii.
Conclusion:
In children with the symptoms described above, tests to detect antibodies to C burnetii should be performed.
Related Concept Videos
 01:25
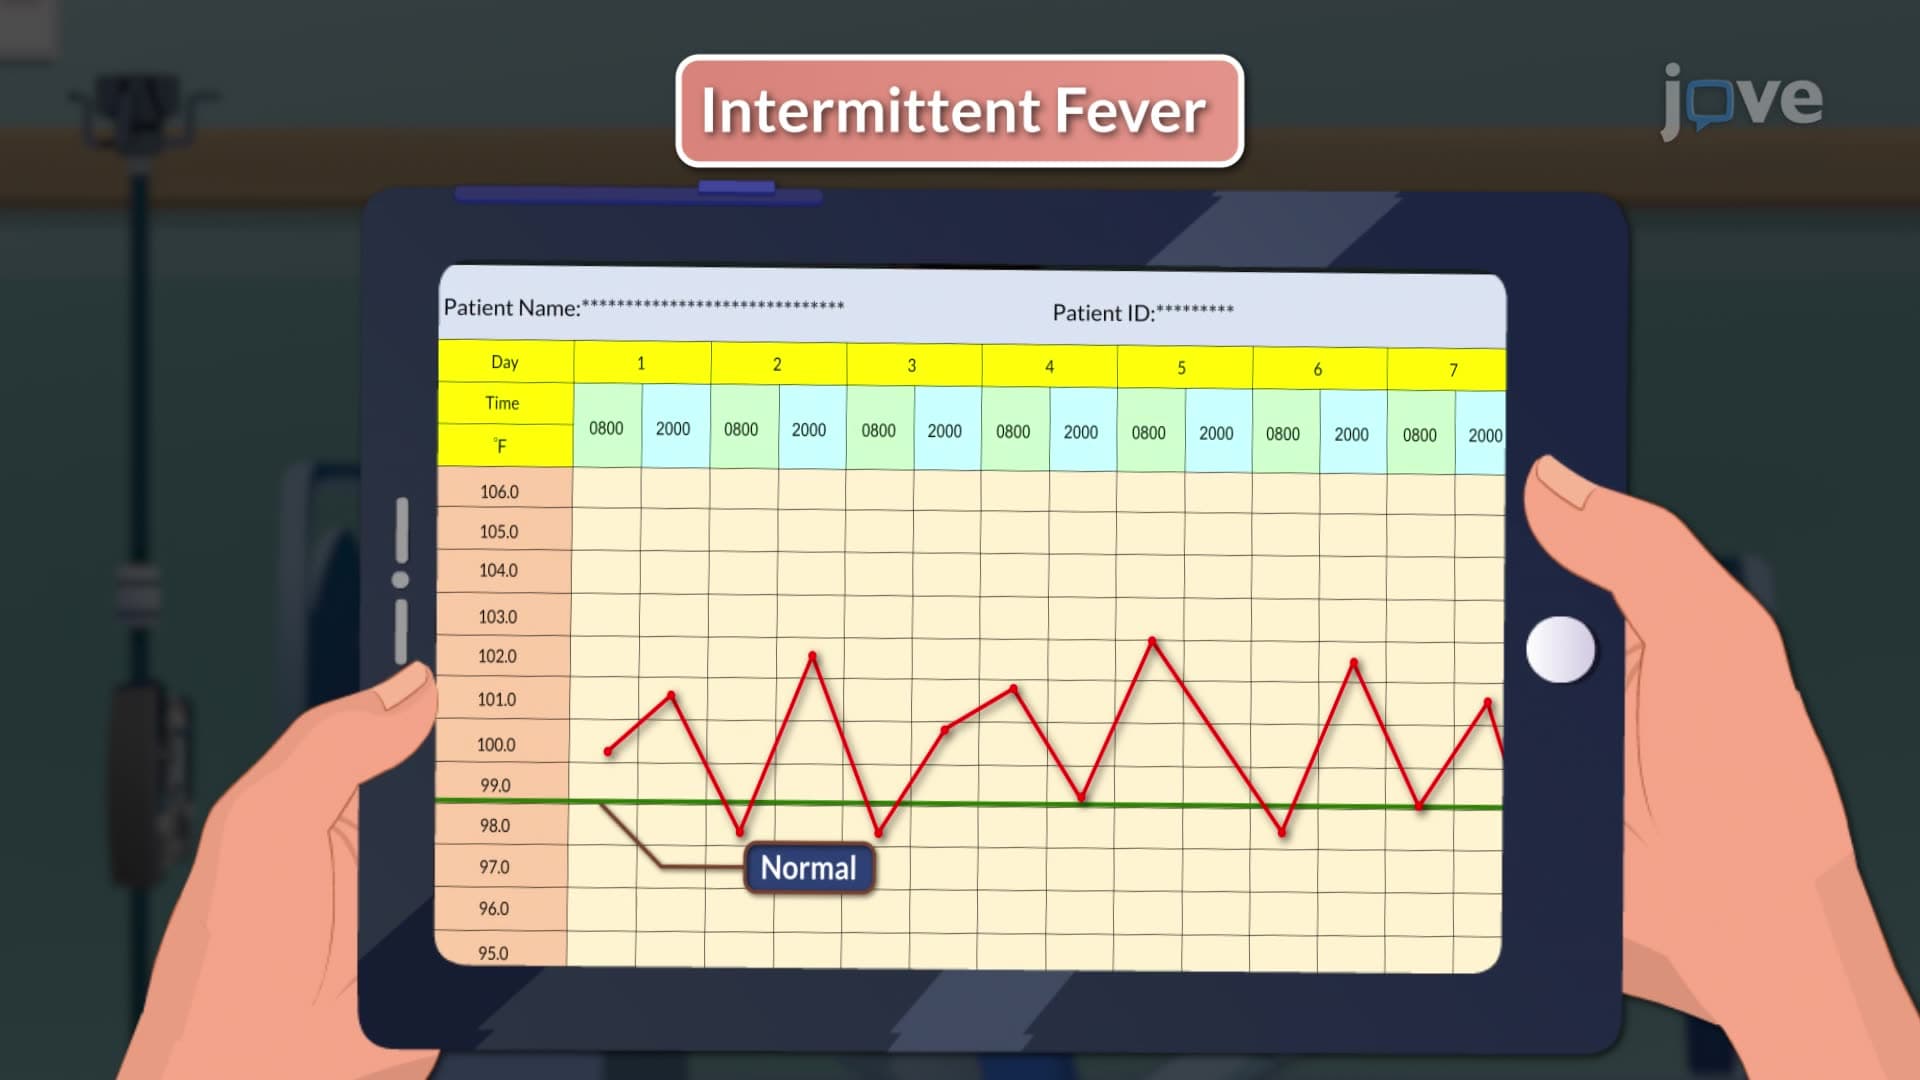
Types of Fever
Here are the different types of fever:
 01:26
Patterns of Fever
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:30
Acute Pharyngitis
Acute pharyngitis is the inflammation of the back of the throat (pharynx), commonly resulting in a sore throat. It is a frequently encountered condition that prompts individuals to seek medical advice.
Classification
Acute pharyngitis can be categorized based on its underlying cause:
 01:25
Increased Body Temperature
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...