Related Experiment Video
Updated: Aug 12, 2026


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
[Deep rectovaginal fistula and incontinence after labor trauma]
1II. Lehrstuhl für Chirurgie, Universität Köln.

The commonest cause of traumata to the organ of continence is the injury during childbirth. Specially after negligent or missing reconstruction apart from incontinence rectovaginal fistulas can arise. This report deals with 24 incontinent women with a perineal laceration. After delivery 17 women had developed a low rectovaginal fistula. In addition to clinical recording of the incontinence, the proctological examination including anal manometry was carried out before and 25 months after surgery on an average. All patients get the same operation: Section of the anterior commissure, cutting out the fistula if necessary, separated suture of the animalic and voluntary sphincter, vaginal plasty. Preoperative resting pressure was 30 cm H2O and the voluntary pressure 46 cm H2O-on an average. Postoperative there was an increase to 61 cm H2O for the resting pressure and to 77 cm H2O for the voluntary pressure. 22 patients reported an improvement. 13 women are completely continent, 7 x soiling, 2 x incontinence for flatus, one incontinence for liquid stool and one stool incontinence were found. One fistula occurred again during follow up. Our surgical procedure compared with others has the advantage to give similar results avoiding protective colostoma. Besides the option for an other surgical procedure is still remained.
The commonest cause of traumata to the organ of continence is the injury during childbirth. Specially after negligent or missing reconstruction apart from incontinence rectovaginal fistulas can arise. This report deals with 24 incontinent women with a perineal laceration. After delivery 17 women had developed a low rectovaginal fistula. In addition to clinical recording of the incontinence, the proctological examination including anal manometry was carried out before and 25 months after surgery on an average. All patients get the same operation: Section of the anterior commissure, cutting out the fistula if necessary, separated suture of the animalic and voluntary sphincter, vaginal plasty. Preoperative resting pressure was 30 cm H2O and the voluntary pressure 46 cm H2O-on an average. Postoperative there was an increase to 61 cm H2O for the resting pressure and to 77 cm H2O for the voluntary pressure. 22 patients reported an improvement. 13 women are completely continent, 7 x soiling, 2 x incontinence for flatus, one incontinence for liquid stool and one stool incontinence were found. One fistula occurred again during follow up. Our surgical procedure compared with others has the advantage to give similar results avoiding protective colostoma. Besides the option for an other surgical procedure is still remained.


Related Concept Videos
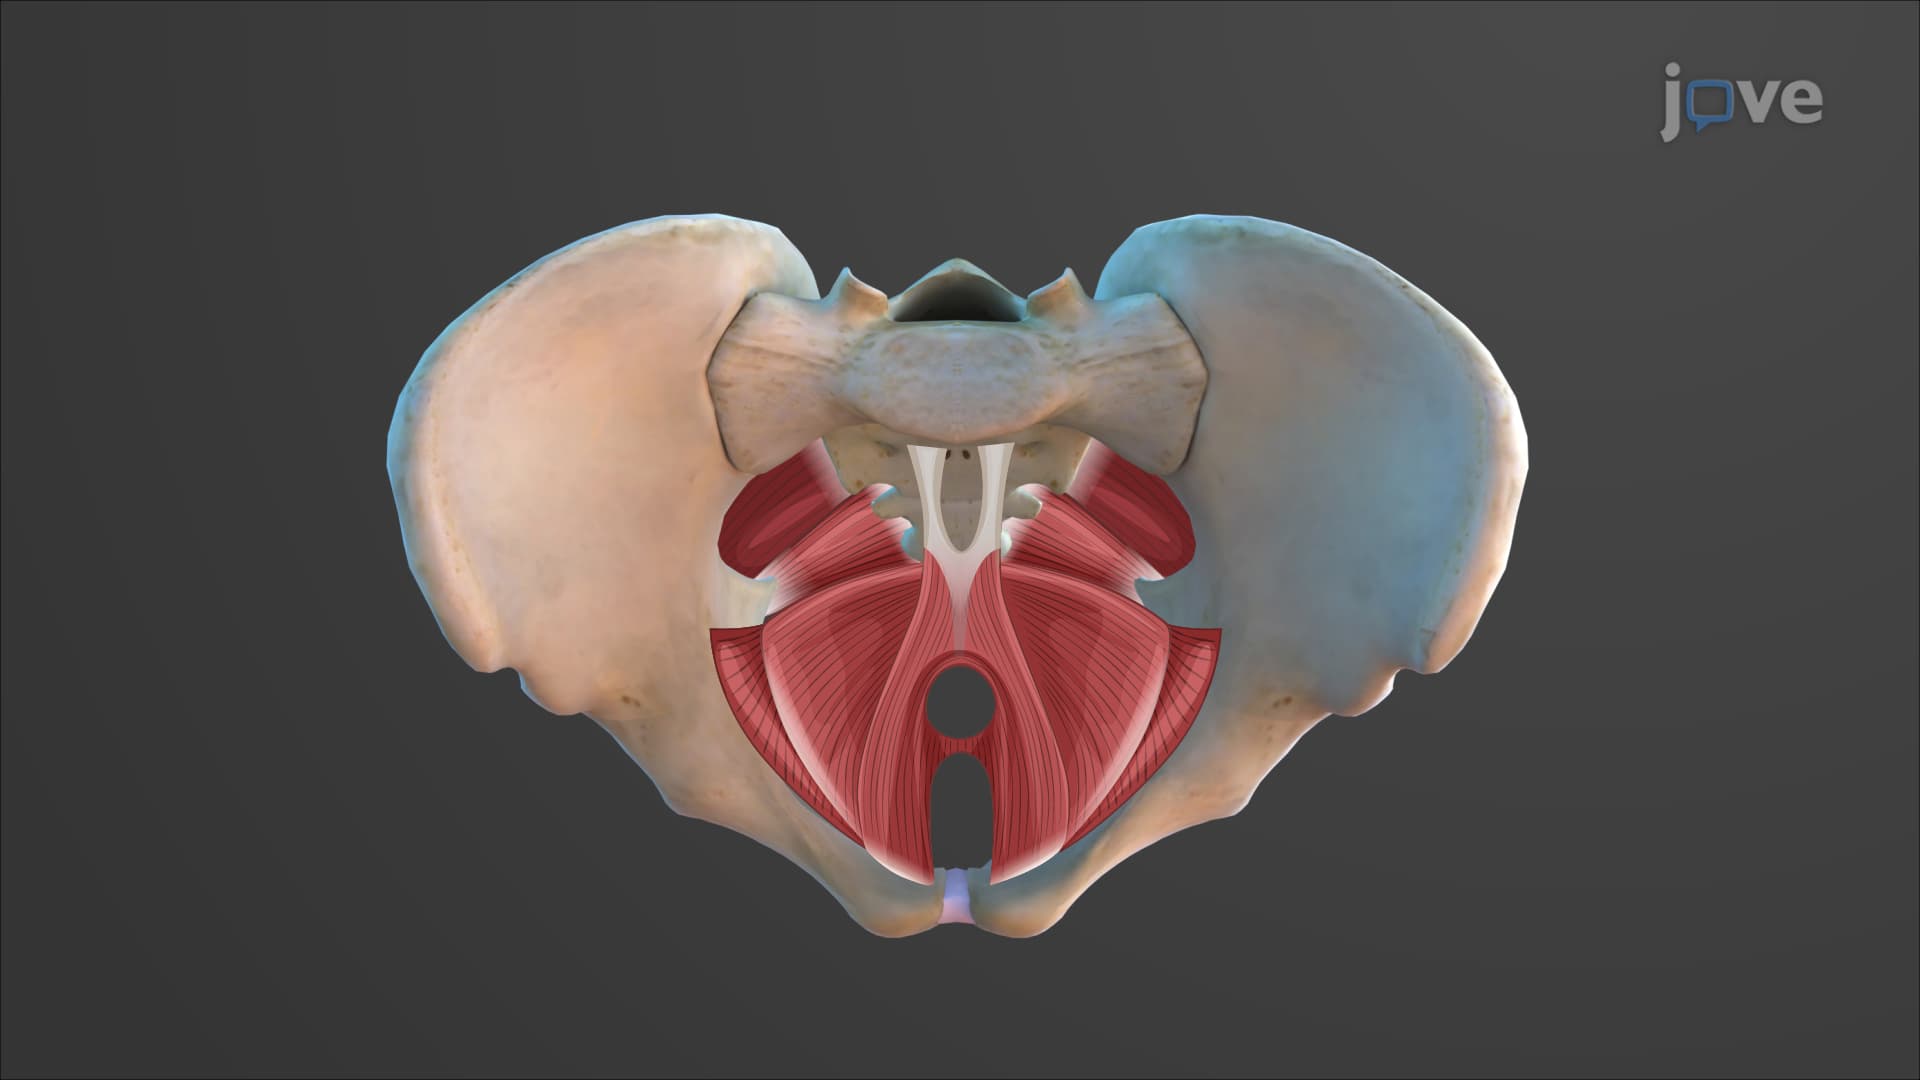 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:27
Diverticular Disease of the Colon