The surgical management of motility disorders
Related Experiment Video
Updated: Nov 7, 2026
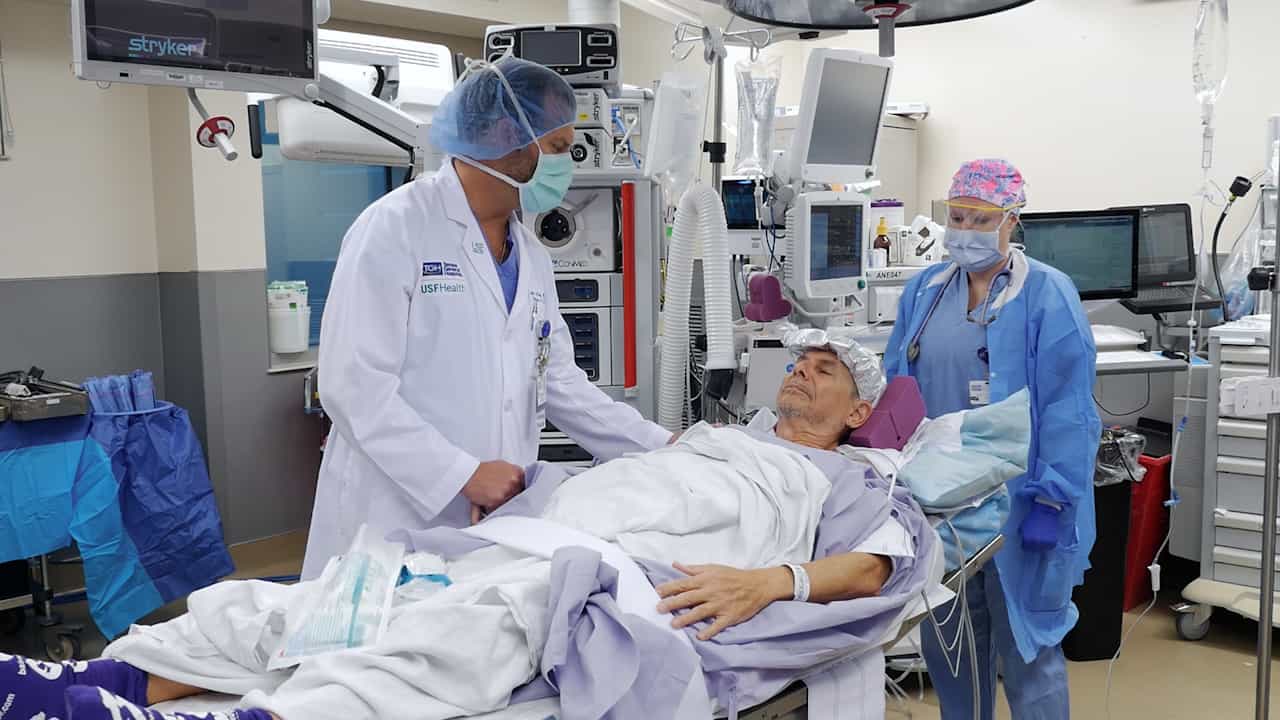
Robotic Heller Myotomy for Advancements in Surgical Management of Achalasia
Published on: February 16, 2024
H Feussner1, W Kauer, J R Siewert
1Chirurgische Klinik und Poliklinik, Technische Universität München, Germany.

Abstract:
Surgical treatment is either the therapy of choice or a facultative procedure in various types of esophageal motility disorders. In achalasia, cardiomyotomy, frequently combined with fundoplasty, achieves good or excellent results in > 80% of cases, and is, therefore, advised in cases when pneumostatic dilatation fails. Diverticulectomy and myotomy of the upper or lower esophageal sphincter are proven procedures to treat cervical and epiphrenic diverticula, leading to good/excellent results or at least an improvement in more than 95%. If, exceptionally, parabronchial diverticula require therapy, they should be excised transthoracically. Cervical myotomy is indicated in cases of cervical achalasia, when sufficient pharyngeal propulsion is preserved. In systemic diseases like scleroderma reflux induced complications may require surgical intervention in medically intractable cases. In these rather few cases, subtotal gastrectomy with a Roux-en-Y anastomosis is advised. In patients suffering from diffuse esophageal spasm or symptomatic "nutcracker" esophagus, extended esophageal myotomy can relieve symptoms. If a clear diagnosis is provided, about 75% of patients will have an improvement of symptoms.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:20
Gastrointestinal Motility Disorders
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:28
Drugs Affecting GI Tract Motility: Dopamine Receptor Antagonists
 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:23
Drugs Affecting GI Tract Motility: Serotonin Receptor Agonists