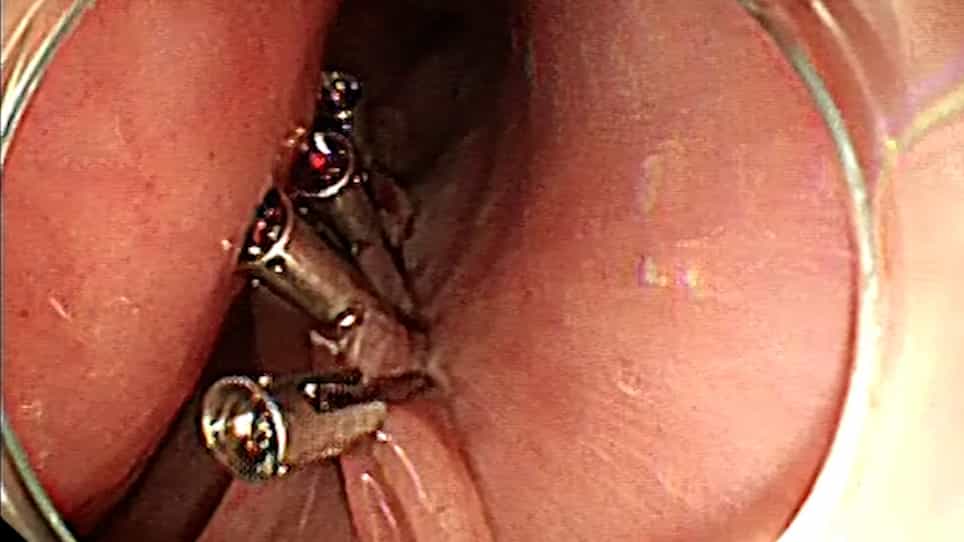
[A modified Macintosh blade for difficult intubation. The mirror blade]
Related Experiment Video
Updated: Nov 7, 2026
The Rigid Tube as an Alternative in Controlling the Problematic Airway
Published on: June 6, 2020
1Institut für Anästhesiologie, Universitätsspital Zürich.

Abstract:
Difficult intubations can occur in cases of anatomical or physiological abnormalities of the face and neck. They are frequently predictable when specific signs are evident preoperatively. There are still occasional unexpected difficulties during conventional laryngoscopy when common blades like the Macintosh and Foregger types are used. During the past 5 decades several authors have proposed many types of laryngoscopes and blades differing in length and shape, as well as various accessories such as guide-wires, prisms, and mirrors. METHOD. We modified a size 3 Macintosh blade by adding a mirror placed tangential to the external curve near the apex. This configuration allows both conventional direct visualisation of the vocal cords and non-direct viewing through the mirror. Insertion of the tube is facilitated using a specially shaped guide-wire. RESULTS. This equipment was used for orotracheal intubation in 20 patients with different degrees of direct laryngeal visibility prior to otolaryngologic endoscopy and surgery under general anaesthesia. Both methods of larynx visualisation were performed and compared. In 1 patient the mirror was not useful because it became fogged. In all the others we could avoid this problem by warming the blade in water. Only in 1 other case was the conventional view better and intubation seemed to be easier than when the mirror was used. In 15 patients the vocal cords were visualised better with the mirror, and intubation was performed by means of the guide-wire with the non-direct technique. In 2 of these cases difficult direct laryngoscopy of grades 3 and 4 according to the Cormack and Lehane classification was found. Four patients were difficult to intubate and neither type of laryngoscopy was ideal. It is notable that a satisfactory view was achieved in the mirror with much less effort. In particular, there was no need to introduce the blade as deeply or raise its apex as much as is usually done. CONCLUSION. The mirror-blade is a suitable device for management of unexpected difficult intubations. Because of its dual availability, it offers both direct and non-direct visualisation of the larynx. Handling of this mirror-blade can be practised extensively, which allows integration of this equipment in the "failed intubation drill". This should be an integral part of the teaching and training of anaesthesia personnel.