Related Experiment Video
Updated: Jul 24, 2026

A Two-Step Method for Percutaneous Transhepatic Choledochoscopic Lithotomy
Published on: September 13, 2022
Prospective randomized study of two different doses of clindamycin admixed with gentamicin in the management of
A E Yellin1, T V Berne, P N Heseltine
1Department of Surgery, University of Southern California, School of Medicine.

Abstract:
Septic complications after surgery for enterogenous peritonitis are minimized by adjuvant antibiotics effective against aerobes and anaerobes. Historically, "gold standard" therapy included an aminoglycoside plus clindamycin, the latter given at 600 mg intravenous piggyback (IVPB), every 6 hours. Clindamycin pharmacokinetics suggests that it can be given q8h and admixed with gentamicin, thereby markedly reducing the cost of administration. Although this is now common practice, there is no prospective study comparing the efficacy of the two dose schedules in peritonitis. This study was designed to test the hypothesis regarding the clinical efficacy of the two regimens. One hundred twenty-six patients with gangrenous (n = 34) or perforated appendicitis (n = 91) were randomized (2:1) to receive gentamicin admixed with clindamycin 900 mg IVPB every 8 hours (Group I n = 80) or gentamicin IVPB q8h plus clindamycin 600 mg IVPB every 6 hours (Group II n = 46). Appendectomy was performed, and aerobic and anaerobic cultures were obtained. Twenty-one patients had simultaneous determinations of clindamycin levels in plasma, peritoneal fluid, and appendix. Outcome analysis revealed no significant differences in postoperative days of fever, days non per os, antibiotic therapy, or hospitalization. There were 6 failures (4 abscesses and 2 wound infections) in Group I and 4 failures (1 abscess and 3 wound infections) in Group II. Both antibiotic regimens provided clinically equivalent results in mixed infections due to aerobic and anaerobic bacteria. The admixed clindamycin, administered every 8 hours, results in at least 20% reduction in costs. This is an important consideration.
Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:15
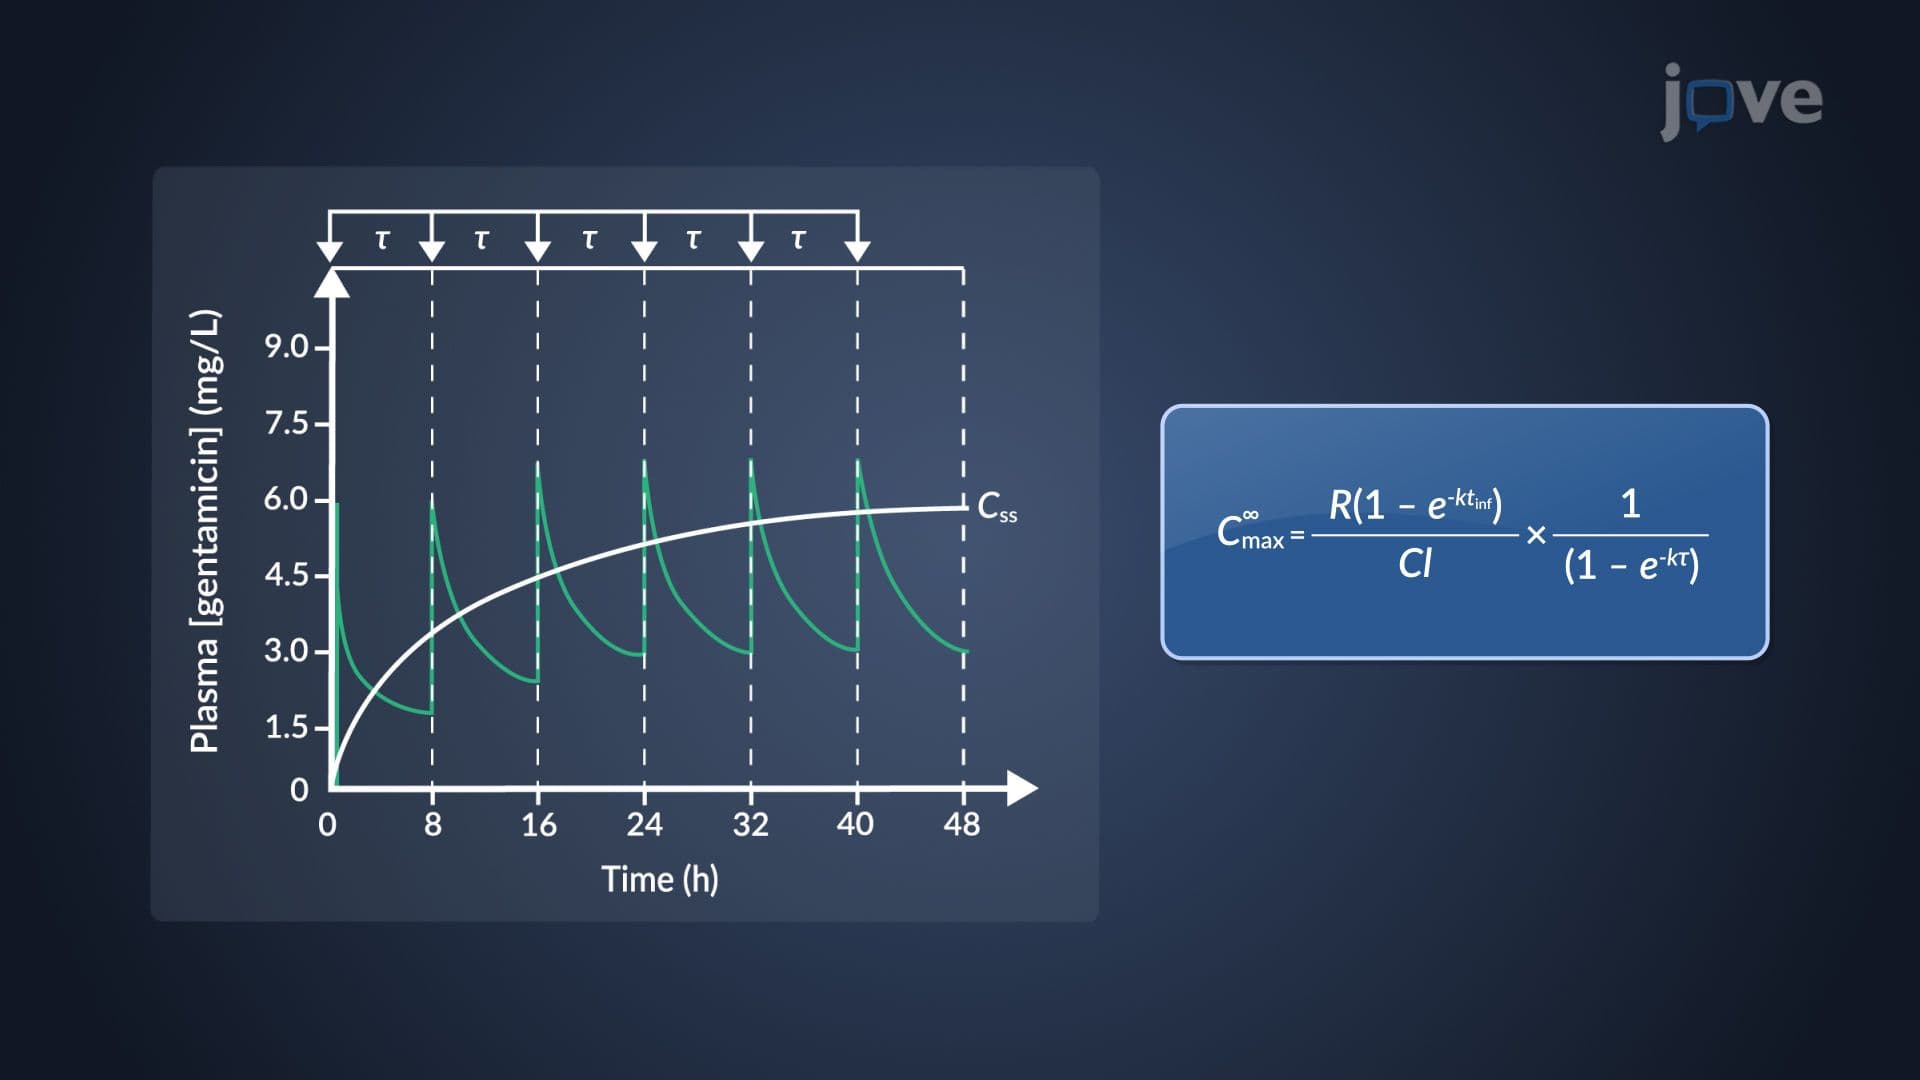
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:19
Appendicitis