Related Experiment Video
Updated: Jul 3, 2026


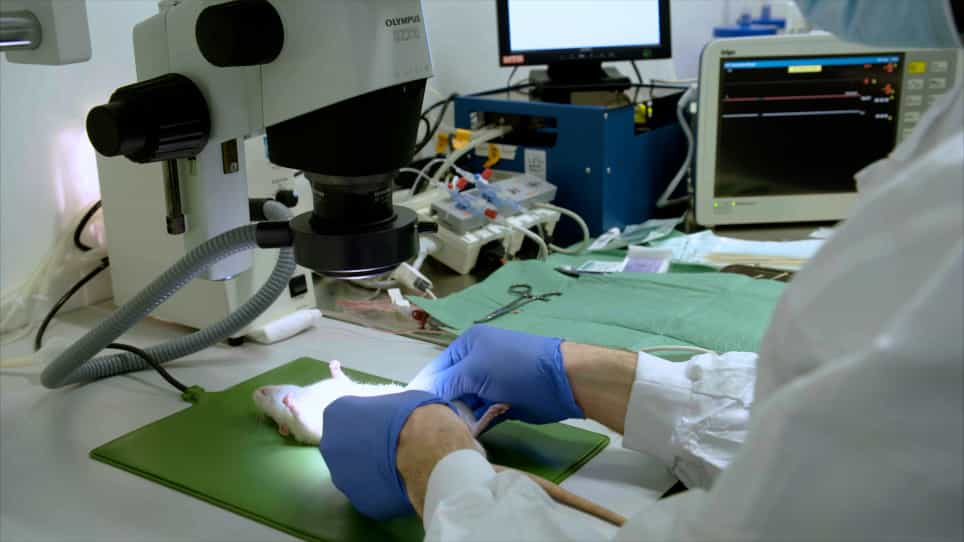
Cecal Ligation Puncture Procedure
Published on: May 7, 2011
Mechanisms of endotoxin-induced intestinal injury in a hyperdynamic model of sepsis
D Xu1, L Qi, D Guillory
1Department of Surgery, Louisiana State University Medical Center, Shreveport 71130-3932.

Abstract:
The goal of this study was to test the hypothesis that endotoxin-induced bacterial translocation is the result of a selective decrease in intestinal blood flow that causes an oxidant-mediated intestinal mucosal injury. To accomplish this goal, 116 instrumented rats receiving a nonlethal dose of endotoxin (5 mg/kg IP) or saline were studied. Organ blood flow and cardiac output were measured using the microsphere technique and intestinal permeability was measured both by the blood to luminal clearance of 51Cr-EDTA and by horseradish peroxidase. Cardiac output was higher in the endotoxin-treated group than in the saline group (76 +/- 12 versus 95 +/- 17 mL/min; p < 0.05). Although endotoxin induced a hyperdynamic state, blood flow to the distal ileum and cecum was selectively decreased by 35%-50% (p < 0.01), whereas blood flow to the rest of the intestine, spleen, pancreas, and liver was normal. Furthermore, blood flow to the ileal mucosa was decreased to a greater extent than to the remainder of the gut wall (p < 0.05). Small bowel permeability to 51Cr-EDTA was increased at sites of decreased blood flow (ileum) but not at sites of normal (jejunum) blood flow. Allopurinol, a competitive inhibitor of xanthine oxidase, ameliorated the endotoxin-induced decrease in ileal blood flow as well as the increase in ileal permeability. Thus these studies support the hypothesis that endotoxin-induced mucosal injury is the result of an ischemia reperfusion-mediated injury of the distal small intestine and cecum.
Related Concept Videos
 01:20
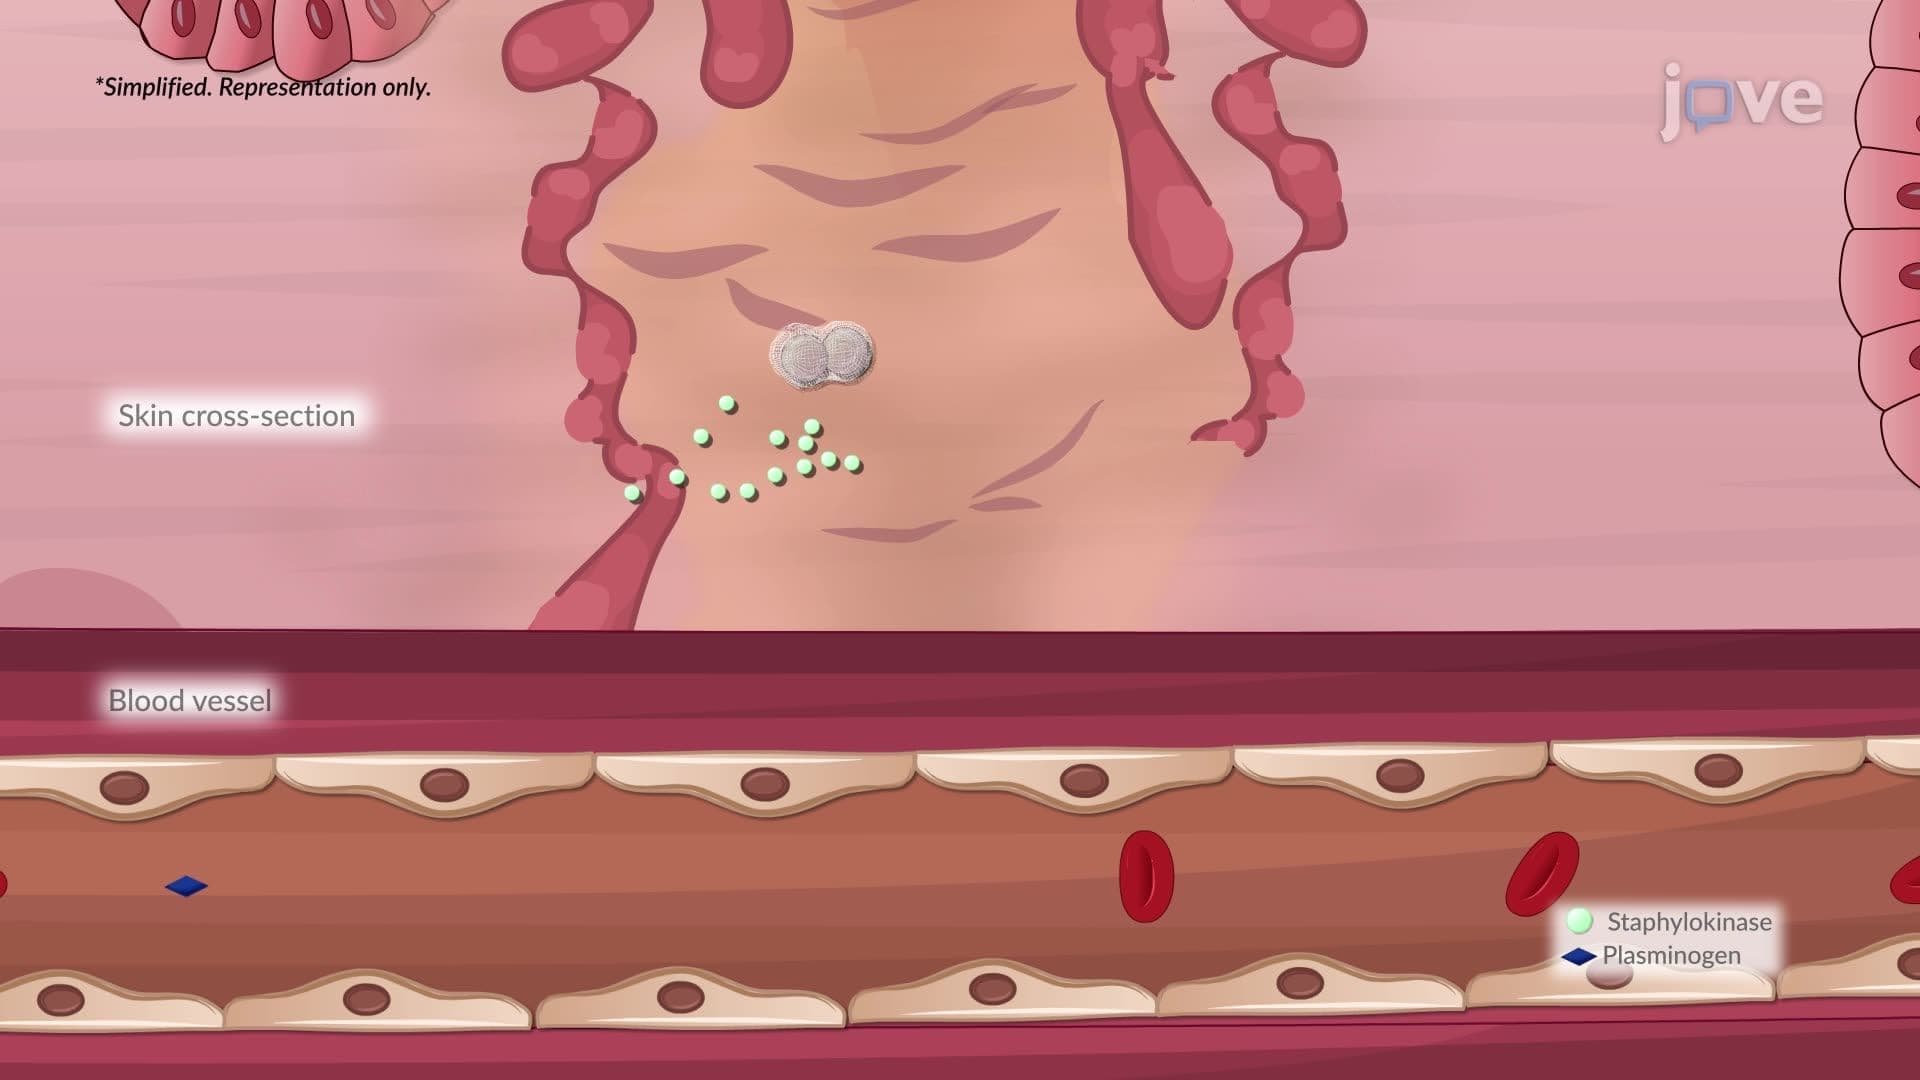
Determinants of Bacterial Pathogenicity and Virulence
 01:18
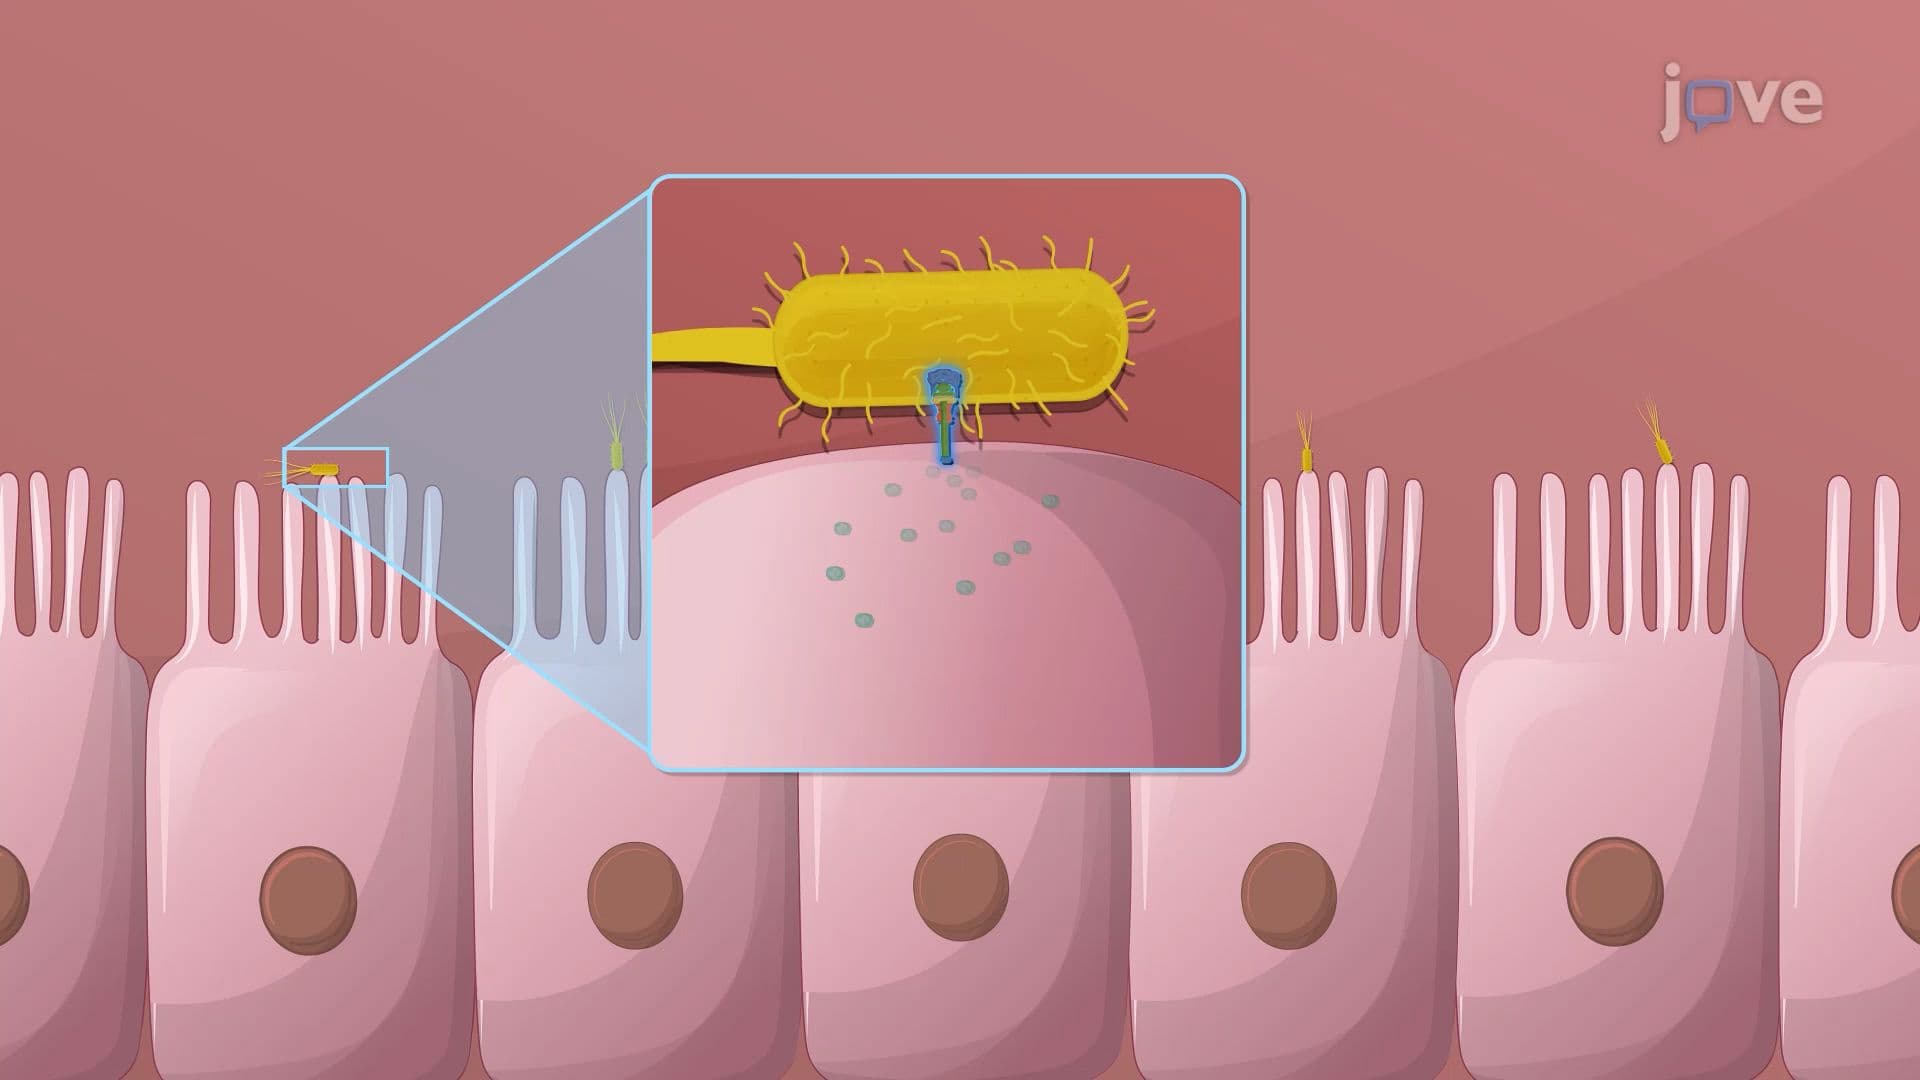
Bacterial Gastroenteritis
 01:25
Acute Inflammation III: Local and Systemic Effects
 01:07
Intestinal Obstruction II: Pathophysiology
 01:21
Acute Pancreatitis II: Pathophysiology