Related Experiment Video
Updated: Aug 14, 2026
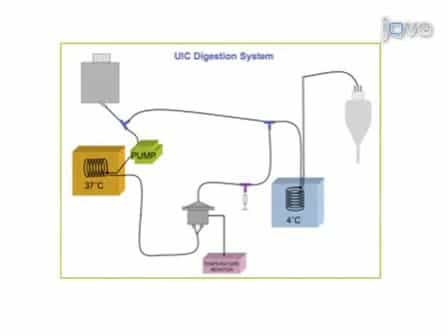

Human Pancreatic Islet Isolation: Part I: Digestion and Collection of Pancreatic Tissue
Published on: May 26, 2009
Fate of oral enzymes in pancreatic insufficiency
L Guarner1, R Rodríguez, F Guarner
1Digestive System Research Unit, Hospital General Vall d'Hebron, Autonomous University of Barcelona, Spain.

Abstract:
Oral pancreatic enzyme supplements, including those protected from gastric acidity by enteric coating, often achieve only partial correction of pancreatic steatorrhoea. To characterise the mechanisms involved in vivo, eight patients with steatorrhoea due to advanced pancreatic insufficiency and nine healthy controls were studied. Two sets of studies (small bowel intubation and five day faecal fat quantification) were randomly performed while patients were either on enteric coated pancreatin or equivalent placebo. A 260 cm long multilumen tube was used for double marker perfusion of two 20 cm segments located in the duodenum and in the ileum respectively. Luminal pH, flow, and trypsin and lipase activity outputs were measured at each segment for four hours postcibally. Placebo treated patients with pancreatic steatorrhoea had low enzyme outputs in the duodenal test segment and even lower outputs in the ileal segment. Pancreatin treatment significantly decreased steatorrhoea (p < 0.05) and increased luminal enzyme outputs (p < 0.05). The increase was much greater in the ileal than in the duodenal segment. Thus enteric coated pancreatin treatment abolished the normal gradient between postcibal duodenal and ileal lipase output. The results suggest that enteric coated pancreatin nearly corrects severe pancreatic steatorrhoea. The ingested lipase was utilised inefficiently, however, as luminal enzyme activity in the ileum was enhanced to a greater extent than in the duodenum, and consequently the absorptive potential of the small bowel was only partially utilised.

Related Concept Videos
 01:06
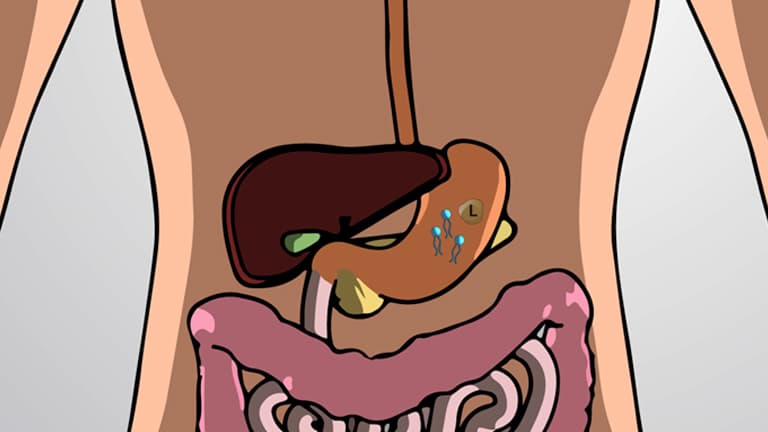
Lipid Digestion
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:25
Acute Pancreatitis I: Introduction
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
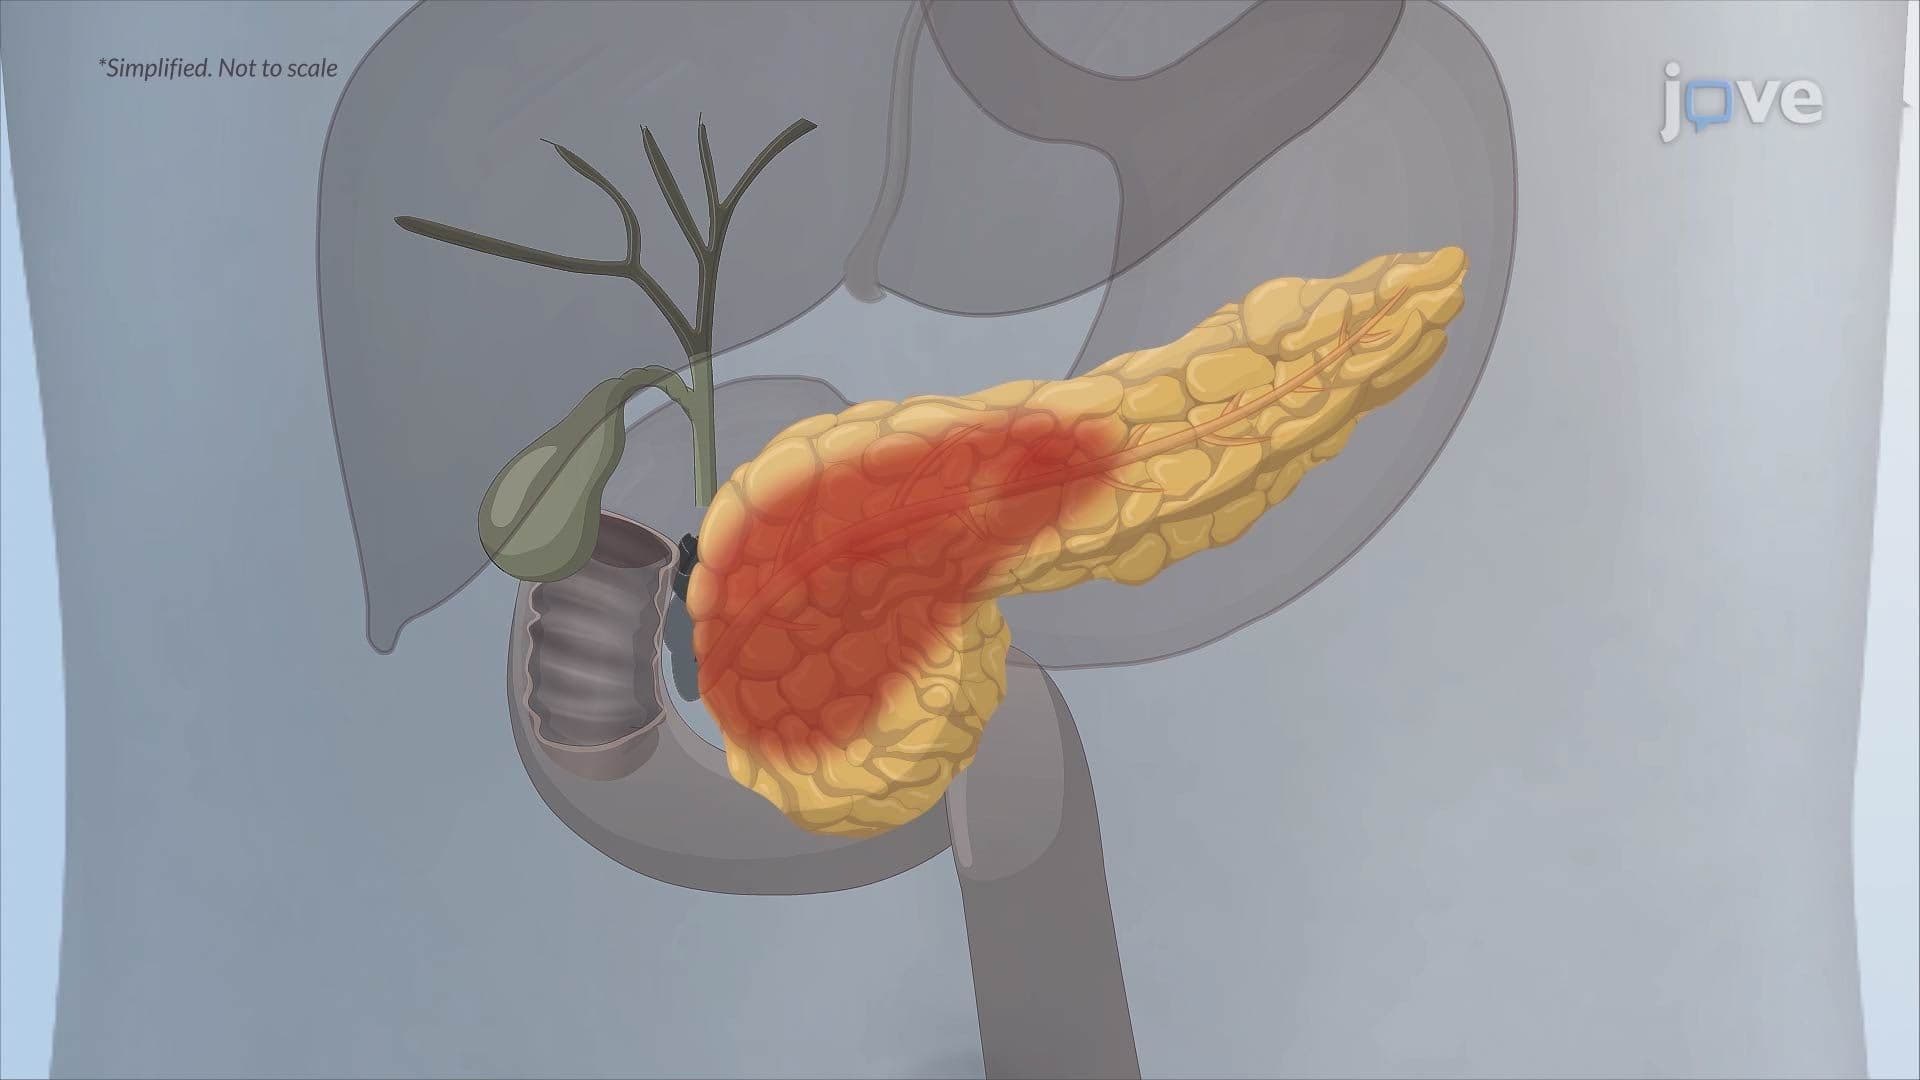
Chronic Pancreatitis I: Introduction
 01:21
Chronic Pancreatitis II: Pathophysiology