Central diabetes insipidus in a dog with a pro-opiomelanocortin-producing pituitary tumor not causing

M M Goossens1, A Rijnberk, J A Mol

  • 1Department of Clinical Sciences of Companion Animals, Faculty of Veterinary Medicine, Utrecht University, The Netherlands.

Related Concept Videos

Diabetes Insipidus I: Introduction01:29

Diabetes Insipidus I: Introduction
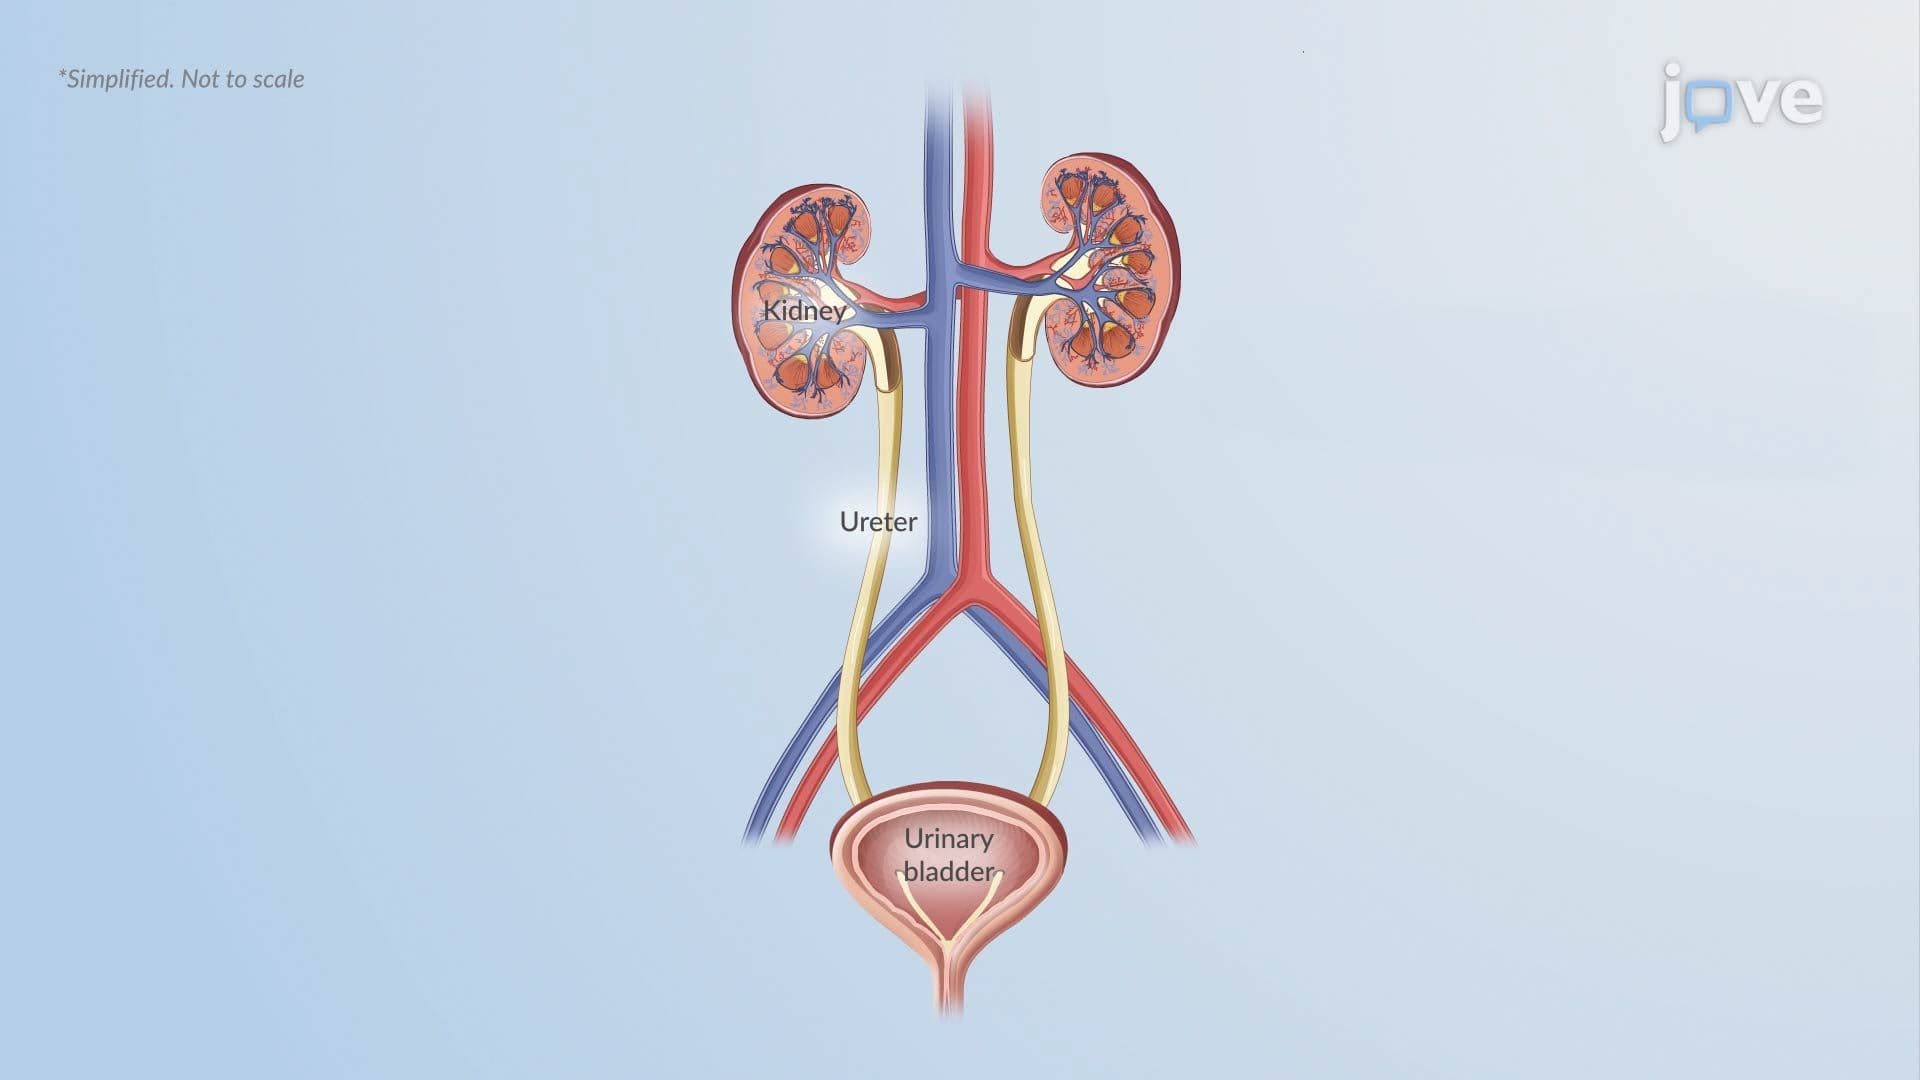
Definition Diabetes insipidus is a disorder marked by the production of large amounts of dilute urine because of impaired vasopressin production, release, or kidney response. The lack of effective vasopressin action limits water reabsorption in the renal collecting ducts, which leads to excessive urinary water loss and intense thirst.Clinical PresentationIndividuals with diabetes insipidus report persistent thirst and very high urine output. In severe cases, fluid intake can reach up to 20...
Diabetes Insipidus II: Pathophysiology01:22

Diabetes Insipidus II: Pathophysiology

Normally, water balance is maintained through three interconnected mechanisms: the hypothalamic thirst center, the synthesis and release of antidiuretic hormone (ADH, or vasopressin), and the kidneys' responsiveness to this hormone. ADH is synthesized in the hypothalamus, released from the posterior pituitary, and acts on the distal nephron, allowing water reabsorption and concentrated urine production.Diabetes Insipidus and Its TypesIn diabetes insipidus (DI), this regulatory system is...
Cushing Syndrome I: Introduction01:26

Cushing Syndrome I: Introduction

Cushing syndrome refers to the collection of clinical manifestations that arise when tissues are exposed to excessive amounts of cortisol or cortisol-like medications over an extended period. Cortisol, a glucocorticoid produced by the adrenal cortex, regulates metabolism, immune responses, and the body’s adaptation to stress. When its concentration remains chronically elevated, these physiological pathways become dysregulated, resulting in the characteristic features of the syndrome.Exogenous...
Cushing Syndrome II: Pathophysiology01:19

Cushing Syndrome II: Pathophysiology

Cortisol production is normally governed by the hypothalamic–pituitary–adrenal (HPA) axis, which maintains hormonal balance through tightly regulated feedback mechanisms. Disruption of this regulatory system is central to the development of Cushing syndrome, whether the excess cortisol originates from external medications or internal pathology. Persistent cortisol elevation alters metabolism, immune function, and endocrine signaling, producing the characteristic clinical features of the...
Type I Diabetes III: Clinical Manifestations01:19

Type I Diabetes III: Clinical Manifestations

Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...
Hyperglycemia01:29

Hyperglycemia

Hyperglycemia is an abnormally high blood glucose level. It is diagnosed by fasting glucose ≥126 mg/dL, 2-hour oral glucose tolerance test (or OGTT) ≥200 mg/dL, random glucose ≥200 mg/dL with symptoms, or HbA1c ≥6.5%. However, HbA1c results may be unreliable in certain conditions, such as anemia or hemoglobinopathies, and the diagnosis should be confirmed unless classic symptoms are present. Postprandial hyperglycemia is typically considered significant when glucose levels exceed 180 mg/dL two...




