Related Experiment Video
Updated: May 3, 2026
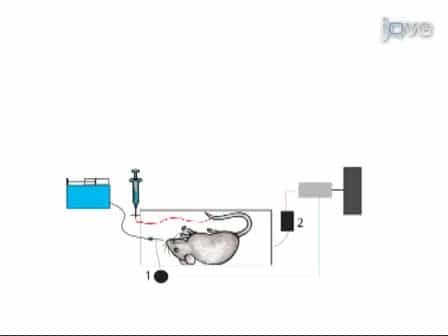
A Reversible, Non-invasive Method for Airway Resistance Measurements and Bronchoalveolar Lavage Fluid Sampling in Mice
Published on: April 14, 2010
Salbutamol-induced increased airway responsiveness to allergen and reduced protection versus methacholine: dose
R Bhagat1, V A Swystun, D W Cockcroft
1Department of Medicine, Royal University Hospital, Saskatoon, Saskatchewan, Canada.

Background:
Two adverse effects of inhaled beta 2-agonists are increased airway responsiveness to allergen and tolerance to the bronchoprotective effect of beta 2-agonists versus bronchoconstrictors (e.g., methacholine).
Objective:
We studied three doses of inhaled salbutamol, 200, 400, and 800 micrograms/day, to determine dose-response curves for these two adverse effects.
Methods:
Ten atopic patients with mild, stable asthma free of all asthma medications, allergen exposure, and respiratory tract infection for at least 4 weeks participated in a double-blind, random-order, crossover study. There were four 1-week treatment periods with a 1-week washout period: placebo, salbutamol 200 micrograms, 400 micrograms and 800 micrograms per day. After each treatment, we assessed FEV1, bronchodilation 10 minutes after administration of 200 micrograms of salbutamol, methacholine PC20, methacholine dose-shift after administration of 200 micrograms of salbutamol, and allergen PC20.
Results:
There was no significant difference in baseline FEV1, bronchodilation, or methacholine PC20. The methacholine dose shift was maximum after the placebo (3.4 +/- 0.22 doubling doses) and was significantly greater (p < 0.01) than all salbutamol regimens (2.2 to 2.6), which were not significantly different from each other (p > 0.05). Allergen PC20 was significantly lower (p < 0.02) after salbutamol 800 micrograms/day (geometric mean = 288 protein nitrogen units [PNU]/ml) than each of the other treatments (447 to 550 PNU/ml), which were not significantly different from each other (p > 0.05).
Conclusion:
Significant increase in airway responsiveness to allergen occurred only with the largest dose of inhaled salbutamol (800 micrograms/d); however, tolerance to the acute bronchoprotective effect of salbutamol was observed with all the three salbutamol regimens, even 200 micrograms/day. This suggests different mechanisms may be operative in producing these two effects.

Related Concept Videos
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce...
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes: