Related Experiment Video
Updated: Oct 2, 2026


Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
Corticosteroid-binding globulin in preterm infants in an intensive care unit
1Department of Pediatrics, Children's Hospital of New Mexico, University of New Mexico School of Medicine, Albuquerque 87123-5311, USA.

Insights
Corticosteroid-binding globulin (CBG) levels in preterm infants increase with age. Lower CBG concentrations were observed in infants with pulmonary disease, suggesting a link to inflammation.
Area of Science:
- Neonatal Medicine
- Endocrinology
- Pediatric Pulmonology
Background:
- Corticosteroid-binding globulin (CBG) plays a crucial role in regulating corticosteroid bioavailability.
- Understanding CBG dynamics in preterm infants is essential for assessing physiological development and disease states.
Purpose of the Study:
- To investigate the changes in blood corticosteroid-binding globulin (CBG) concentrations in preterm infants during the first six weeks of life.
- To determine the correlation between CBG levels, gestational age, postnatal age, and the presence of pulmonary disease.
Main Methods:
- Blood samples were collected from 85 preterm infants (24-36 weeks gestational age) over the first 6 weeks of postnatal life.
- CBG concentrations were measured and analyzed in relation to gestational age and postnatal age.
- Statistical analysis was performed to compare CBG levels between infants with and without pulmonary disease.
Main Results:
- CBG concentrations showed a direct correlation with both gestational age and postnatal age within the first week of life.
- A significant increase in mean CBG values was observed from weeks 1-2 to weeks 4-6.
- Infants experiencing pulmonary disease in the first week exhibited significantly lower postnatal CBG values (p = 0.001).
Conclusions:
- CBG levels in preterm infants are influenced by both gestational and postnatal age.
- Lower CBG concentrations in infants with pulmonary disease may indicate an inflammatory response.
- These findings highlight the potential of CBG as a biomarker in neonatal critical care.
Abstract:
Blood concentration of corticosteroid-binding globulin (CBG) was measured in 85 preterm (24-36 weeks of gestational age) infants over the first 6 weeks of postnatal life. CBG concentrations directly correlated to gestational age and postnatal age in the first week of life. There was a significant increase in CBG values over the first 6 weeks such that mean values at weeks 4 through 6 were significantly greater than values at weeks 1 and 2. Postnatal CBG values were significantly lower in infants who had pulmonary disease during week 1 (p = 0.001). In summary, CBG values were directly correlated to gestational and postnatal age, and negatively correlated to acute illness. We speculate that the lower CBG values with lung disease may reflect an ongoing inflammatory response.


Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:21
Drug Distribution: Tissue Binding
For...
 01:29
Drug Distribution: Plasma Protein Binding
 01:30
Drug Binding to Blood Components
HSA is the most abundant plasma protein and is vital in drug binding. It contains distinct drug-binding sites, with different drugs exhibiting affinity for specific sites. There are three main drug-binding domains for HSA: sites I, II, and III. These domains are further...
 01:09
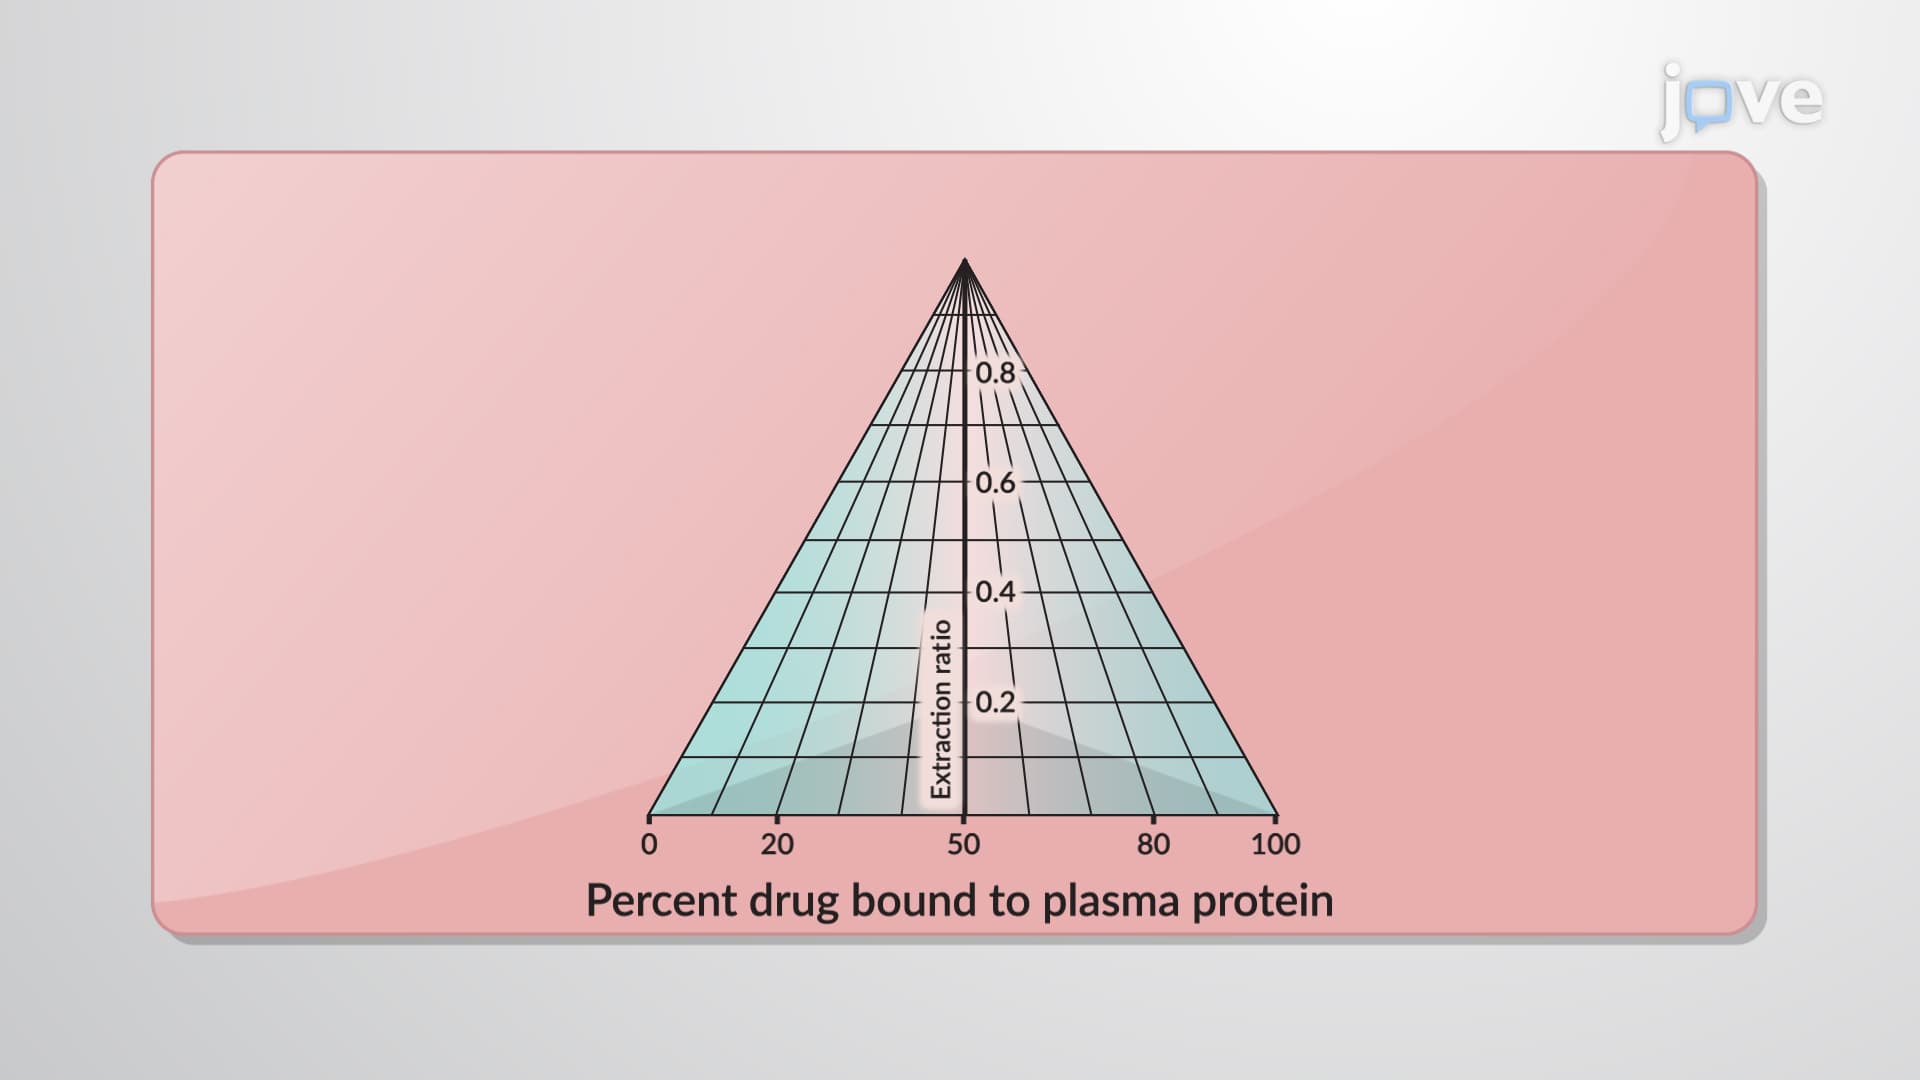
Hepatic Drug Clearance: Effect of Protein Binding
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
 01:29
Drug Dosing: Infants and Children