Related Experiment Video
Updated: Aug 12, 2026

Bronchial Thermoplasty: A Novel Therapeutic Approach to Severe Asthma
Published on: November 4, 2010
[The influence of misoprostol on post-aspirin bronchoconstriction in patients with aspirin sensitive asthma]

Abstract:
It is believed that aspirin (ASA) and other nonsteroidal antiinflammatory drugs elicit dysponea in ASA sensitive asthmatics by blocking the cyclooxygenase. It is unclear whether this bronchospasm is due to shunting of arachidonic acid into the lipooxygenase pathway or removal of cyclooxygenase product which prevent bronchospasm. Diminished tissue concentration of PGE may cause bronchoconstriction. PGE play also modulatory function to mast call decreasing the release of mediators of anaphylaxis. There are some evidences concerning the mast cell degranulation in postaspirin reaction in ASA sensitive asthmatics. The authors investigated the influence of synthetic analogue of PGE1--misoprostol (Cototec, Searle) on the postaspirin bronchoconstriction in seven ASA sensitive asthmatics aged 33-62. Aspirin threshold doses ranged from 10 to 150 mg. Postaspirin bronchoconstriction begun usually within 1-2 hrs after digestion of ASA and 200 micrograms were additionally given 2 h later. Seven days later misoprostol (400 micrograms) was administered together with previously determined dose of ASA. One the other day the bronchodilating effect of misoprostol alone was examined. In all but one patients we observed the protective influence of misoprostol on ASA induced bronchoconstriction. Max. fall in FEV1 in % after ASA in each of the patients was 40, 25, 24, 33, 47 and 54, and after ASA with misoprostol, respectively 10, 9, 4, (+8), 10, (+2) and 45. Misoprostol given together with ASA attenuated aspirin-induced bronchoconstriction reaching statistical significance at 3 and 3.5 h, and also diminished extrapulmonary symptoms. The authors discuss the possible mechanism of protective influence of misoprostol.
Related Concept Videos
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by anesthetizing...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:20
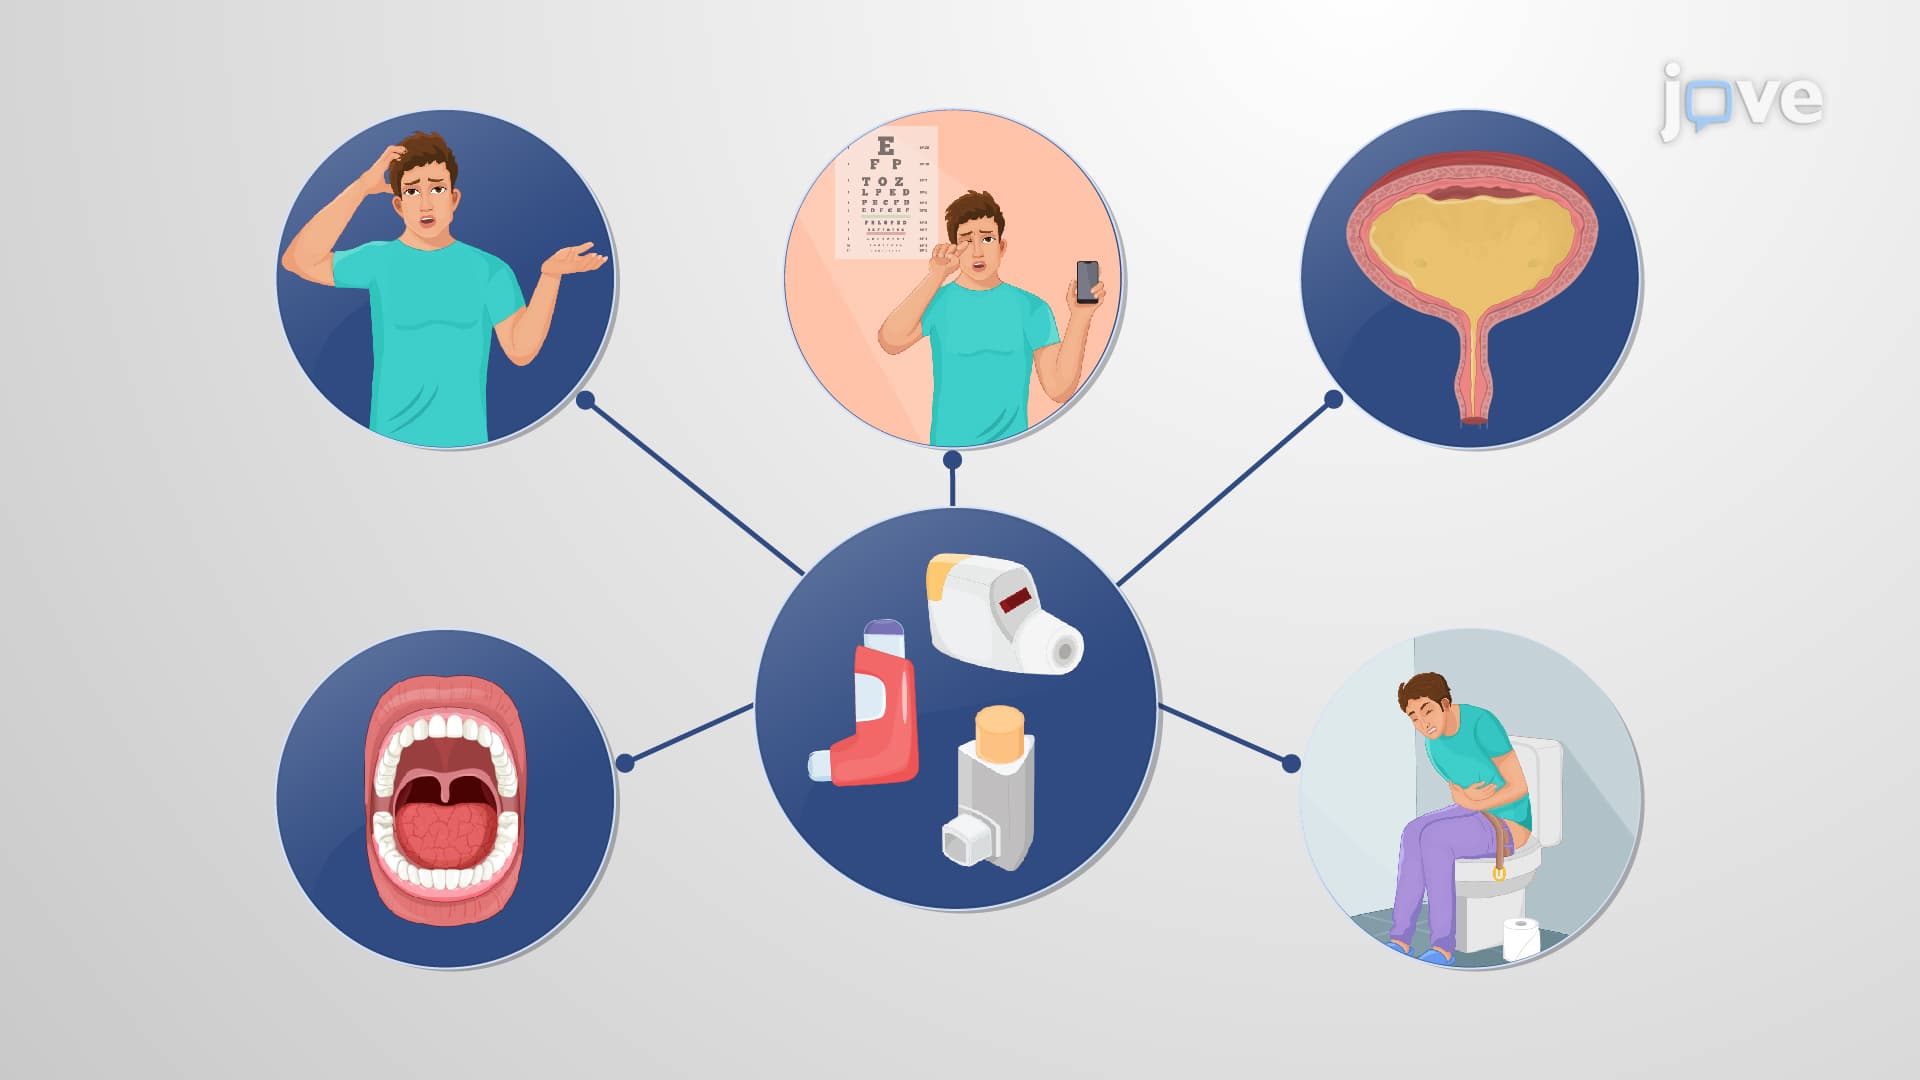
Antiasthma Drugs: Muscarinic Receptor Antagonists
Antimuscarinic agents compete with ACh for the same binding site on the muscarinic receptors. By binding to these receptors, they inhibit the downstream effects of ACh and block the parasympathetic...
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...