Acute effect of inorganic iodide after 131I therapy for hyperthyroidism
Related Experiment Video
Updated: Oct 24, 2026

Generation of a Mouse Spontaneous Autoimmune Thyroiditis Model
Published on: March 17, 2023

Patients treated with inorganic iodide weeks to years following 131I therapy for hyperthyroidism do not adapt to its antithyroid effect. To determine whether such adaptation occurs soon after 131I therapy, serum thyroxine (T4) and triiodothyronine (T3) concentrations were measured daily for 9-14 days following 131I therapy in seventeen hyperthyroid patients. Nine patients received 150 mg KI daily starting 48 h after 131I administration; eight received only 131I. Serum T4 and T3 concentrations did not change significantly in the patients who received only 131I. In the patients who received 131I and KI, serum T4 and T3 concentrations fell promptly, reaching nadir values 2-10 days after initiation of iodide, and then increased despite continuation of KI therapy. The mean maximal fall in serum T4 was 34% and in serum T3 42%. These results show that "escape" from the acute anti-thyroid effect of iodide occurs when it is given immediately after 131I therapy, thus limiting the utility of iodide as a therapeutic agent at this time.
Patients treated with inorganic iodide weeks to years following 131I therapy for hyperthyroidism do not adapt to its antithyroid effect. To determine whether such adaptation occurs soon after 131I therapy, serum thyroxine (T4) and triiodothyronine (T3) concentrations were measured daily for 9-14 days following 131I therapy in seventeen hyperthyroid patients. Nine patients received 150 mg KI daily starting 48 h after 131I administration; eight received only 131I. Serum T4 and T3 concentrations did not change significantly in the patients who received only 131I. In the patients who received 131I and KI, serum T4 and T3 concentrations fell promptly, reaching nadir values 2-10 days after initiation of iodide, and then increased despite continuation of KI therapy. The mean maximal fall in serum T4 was 34% and in serum T3 42%. These results show that "escape" from the acute anti-thyroid effect of iodide occurs when it is given immediately after 131I therapy, thus limiting the utility of iodide as a therapeutic agent at this time.
Related Concept Videos
 01:20
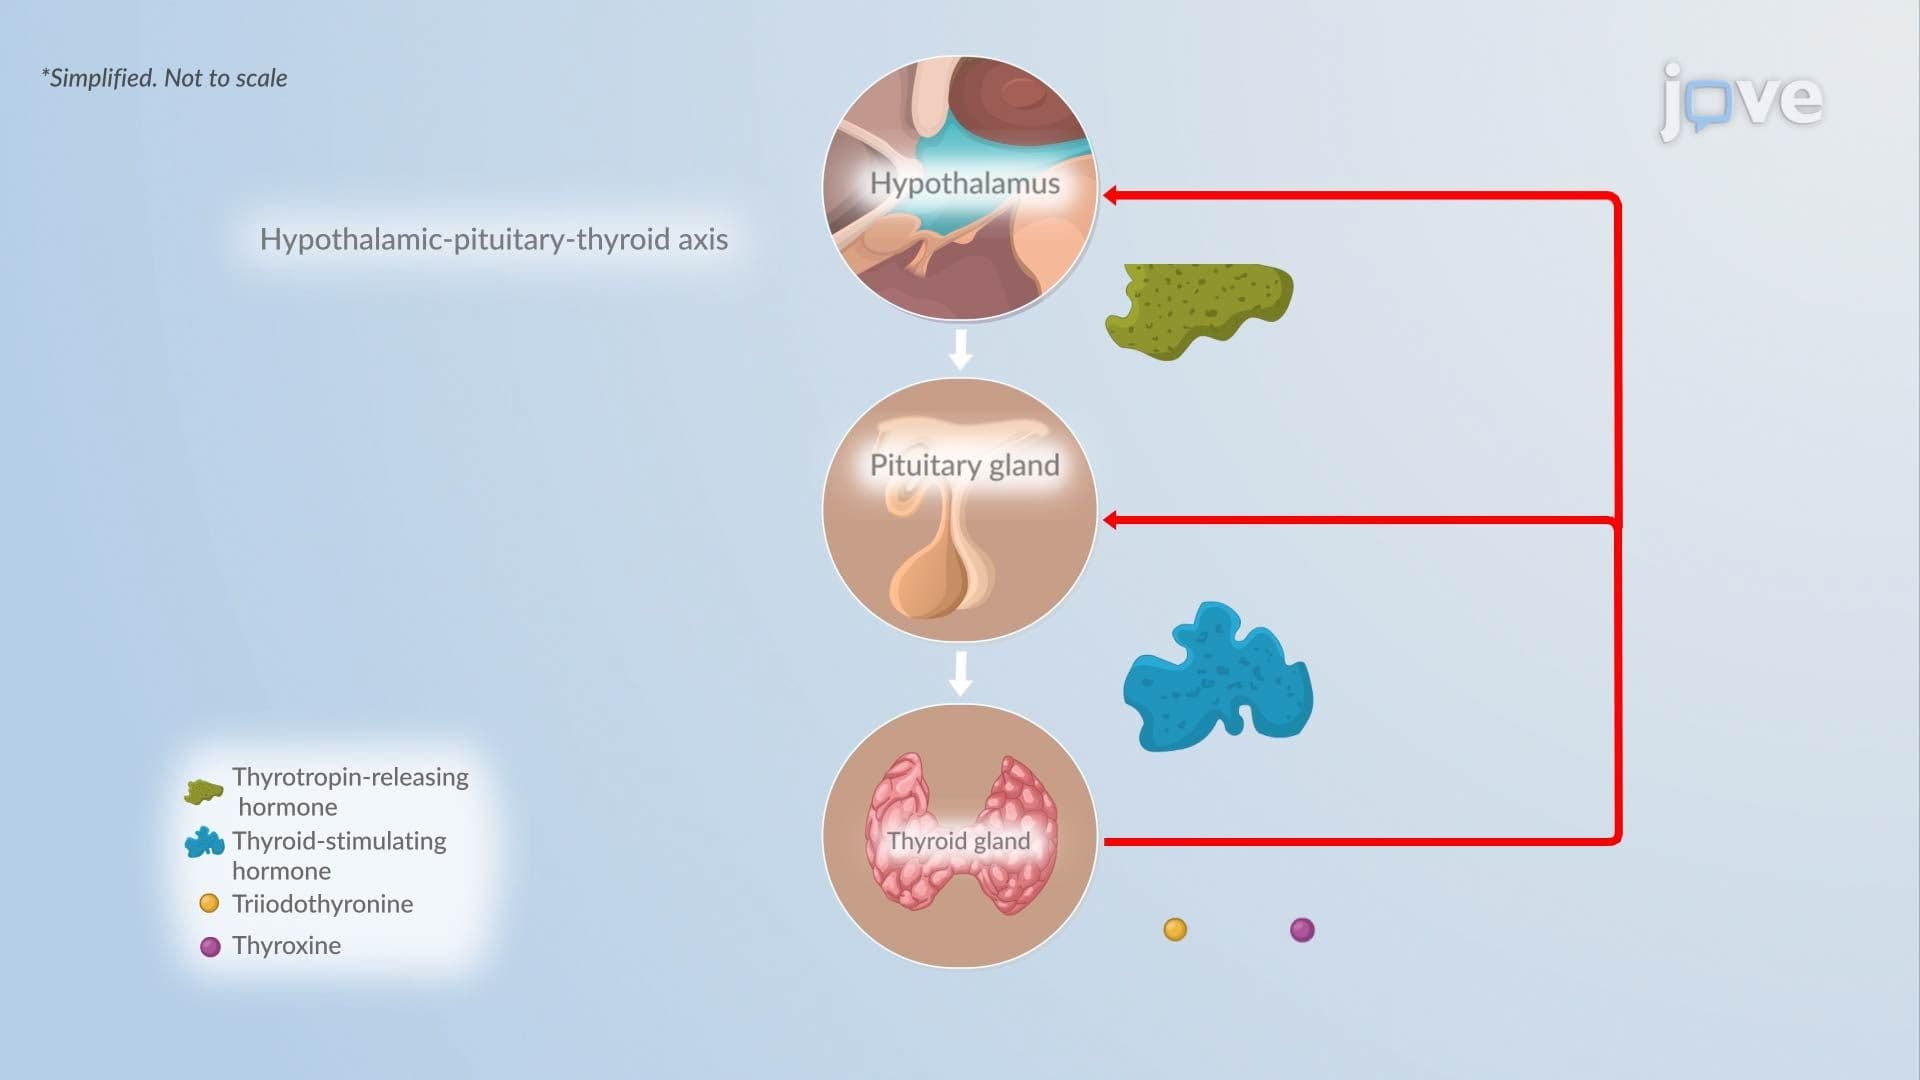
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:28
Graves' Disease I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:27
Goiter