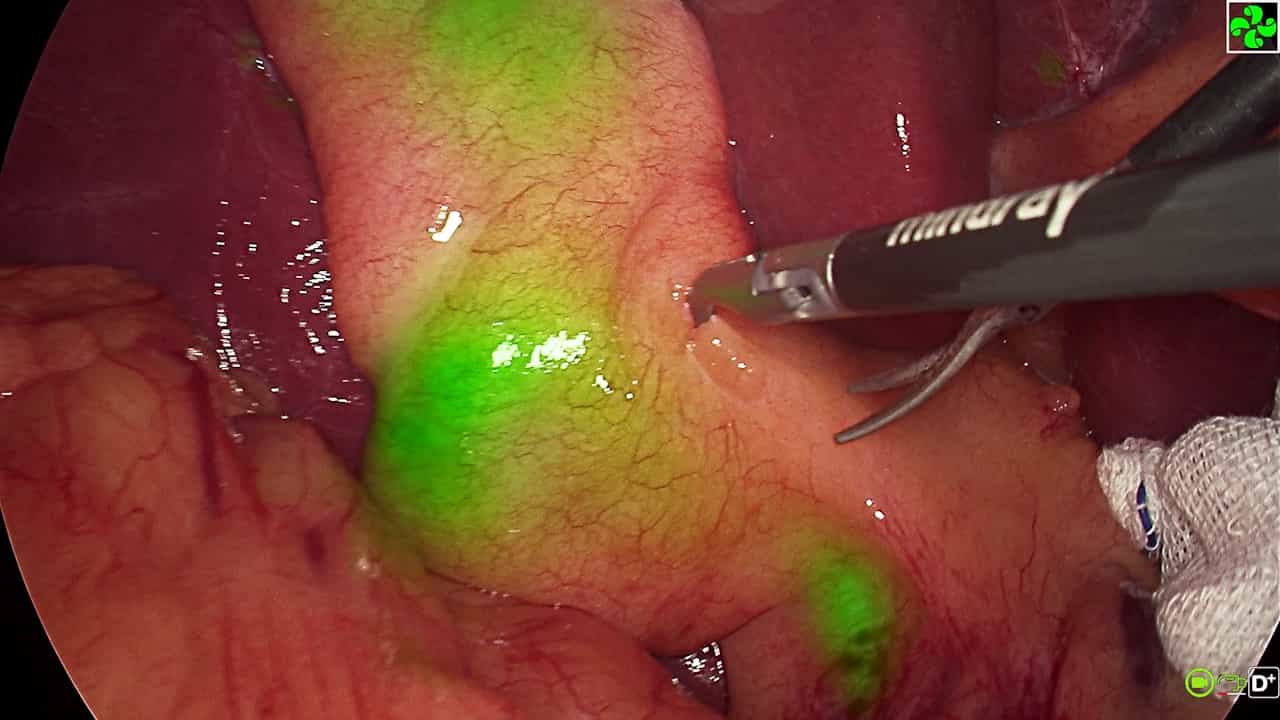
Laparoscopic cholecystostomy for acute acalculous cholecystitis
Related Experiment Video
Updated: Aug 9, 2026
Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
1Institute for Minimally Invasive Surgery, St. Agnes Hospital, 303 North Street, Suite 103, White Plains, NY 10605, USA.

Abstract:
Acute acalculous cholecystitis (AAC) can occur in up to 18% of severely injured patients. Diagnosis is made by positive ultrasound findings of gallbladder sludge, hydrox, and wall thickening. There may also be recent-onset jaundice, positive ultrasound induced Murphy's sign, and unexplained sepsis. Mortality can be as high as 50%. Laparoscopic confirmation was obtained in six ICU trauma patients when omentum was drawn up over a distended gallbladder. Laparoscopic cholecystectomy (LC) was done by first directly decompressing the gallbladder through the fundus. This trocar was replaced by a 16 French Foley catheter passed through an Endoloop into the gallbladder and secured by tightening the loop around a cuff of gallbladder. Sepsis resolved in all cases. Only one required subsequent laparoscopic cholecystectomy. LC has a low morbidity and may be life saving during the early stages of AAC. It is not indicated in gangrene or perforation of the gallbladder.