Reduction in the shivering threshold is proportional to spinal block height
Related Experiment Video
Updated: Sep 30, 2026
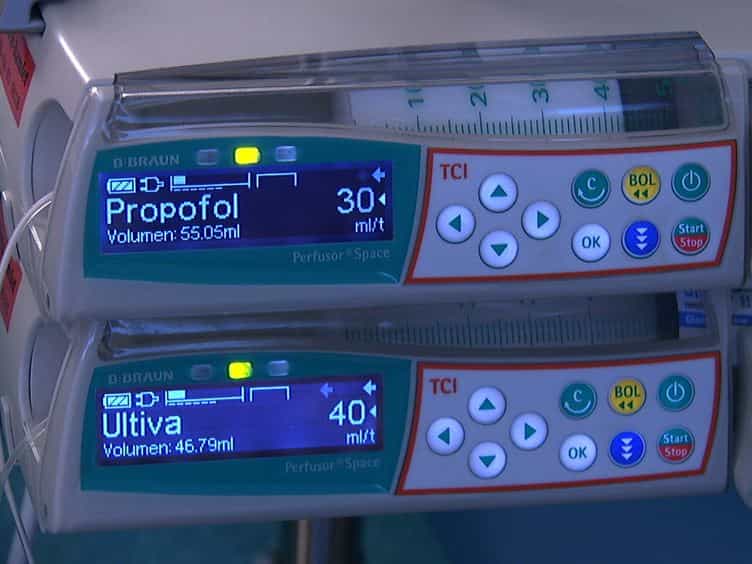
Deep Neuromuscular Blockade Leads to a Larger Intraabdominal Volume During Laparoscopy
Published on: June 25, 2013
1Department of Anaesthesia, Royal Melbourne Hospital, Parkville, Victoria, Australia.

Background:
Hypothermia is nearly as common, and may be as severe, during spinal and epidural anesthesia as during general anesthesia. The authors have proposed that thermoregulatory failure results when regional anesthesia increases apparent leg skin temperature to a level far exceeding actual leg skin temperature. Extensive dermatomal blocks will alter thermal input to the hypothalamus from a greater skin-surface area more than less extensive ones and thus might be expected to impair central thermoregulatory control more. Accordingly, they tested the hypothesis that reduction in the shivering threshold is directly related to the number of dermatomes blocked during spinal anesthesia.
Methods:
Eleven men, aged 62 +/- 6 yr (mean +/- SD), undergoing urologic surgery were studied. Ice-cold lactated Ringer's solution was administered intravenously before spinal blockade and the shivering threshold (triggering core temperature) was established. Spinal anesthesia then was induced using a randomly assigned dose of 0.5% bupivacaine (2-4 ml). Again, sufficient cold lactated Ringer's solution was given to induce shivering. Tympanic membrane, ambient and skin temperatures were measured, and extent of block was defined by loss of temperature discrimination. Presence of shivering was evaluated by a blinded observer. Mean upper-body skin and ambient temperatures, cooling rates and intravenous fluid volumes at the two thresholds were compared using paired, two-tailed t tests (P < 0.05). Linear regression defined the relationship between reduction in shivering threshold and the number of dermatomes blocked.
Results:
There were no significant differences between mean upper-body skin and ambient temperatures, cooling rates or intravenous fluid volumes at the control and spinal shivering thresholds. Spinal anesthesia reduced the shivering threshold in direct relation to the number of dermatomes blocked: delta threshold = 0.74 - 0.06 (dermatomes blocked); r2 = 0.58, P < 0.006.
Conclusions:
Extensive spinal blockade impairs central thermoregulatory control more than less extensive blockade. Clinicians can thus anticipate more core hypothermia during extensive than during restricted spinal blockade.


Related Concept Videos
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:17
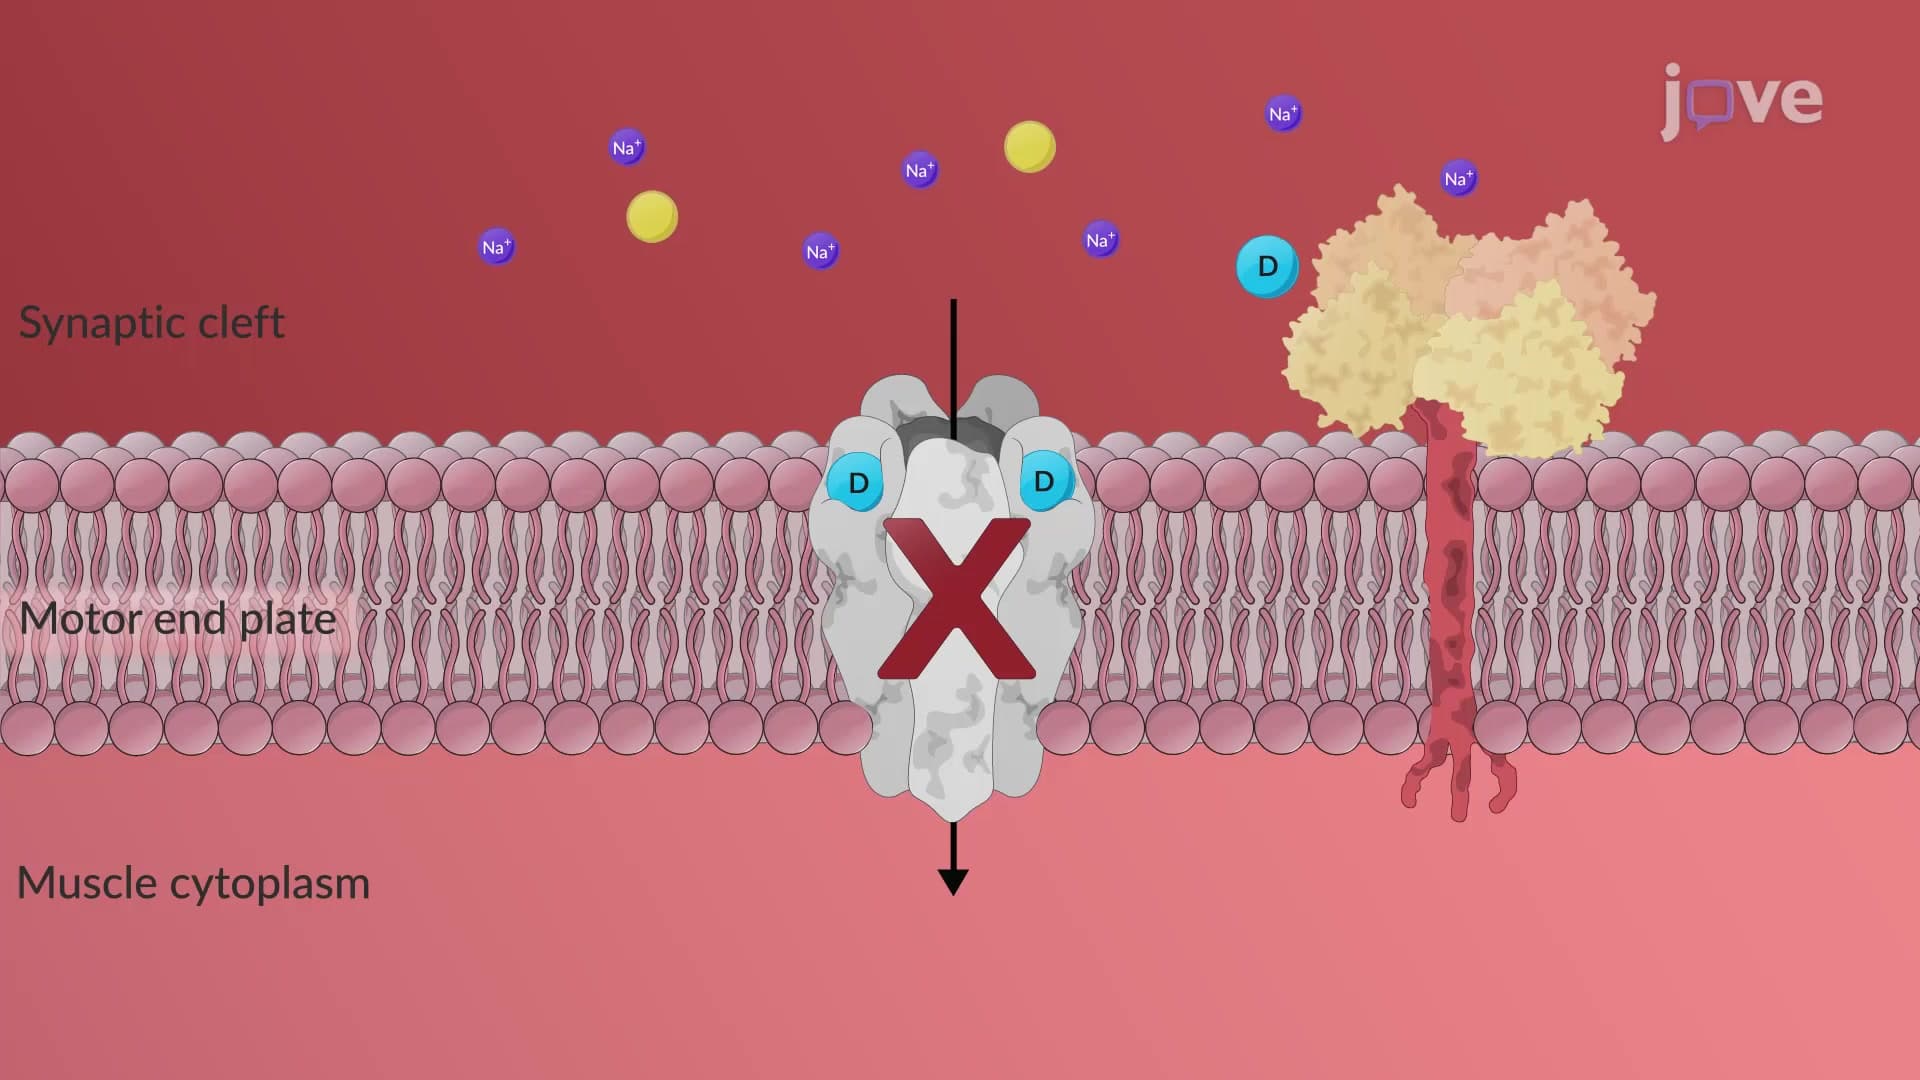
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:28
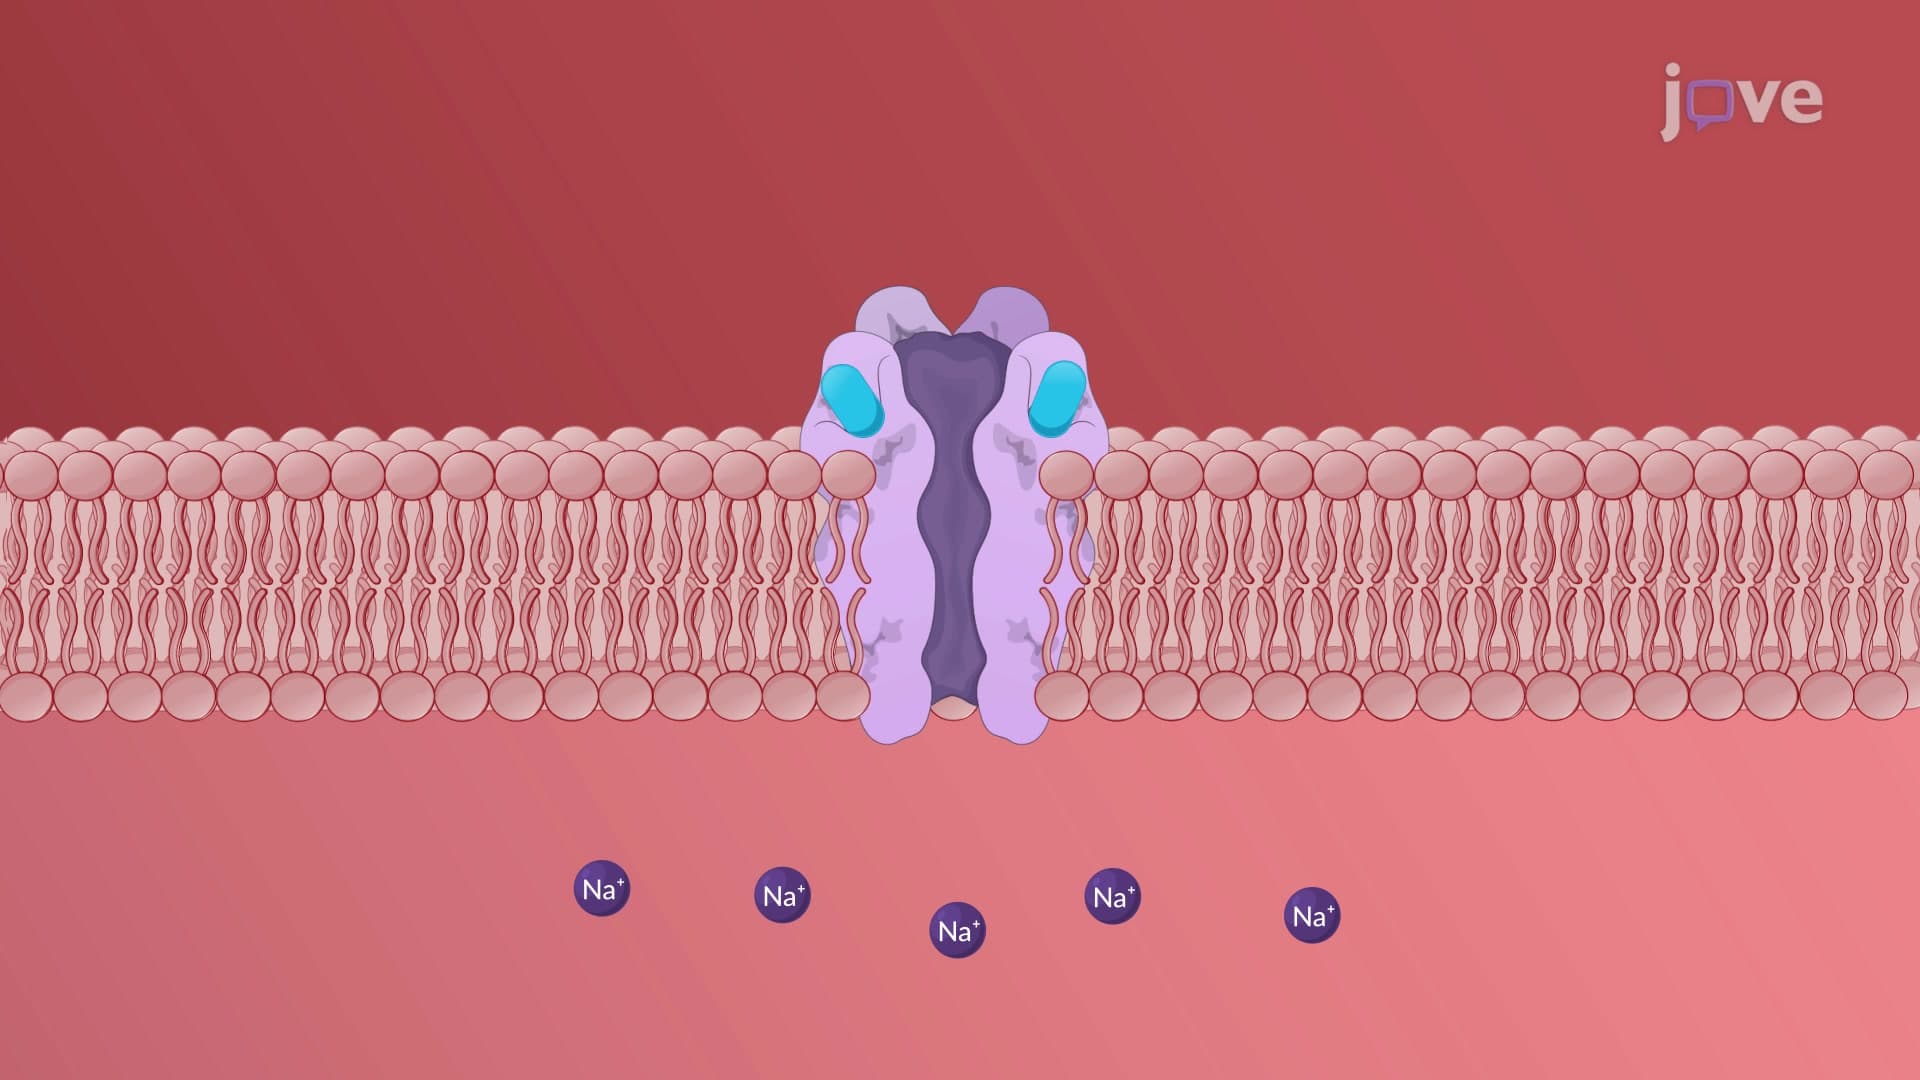
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia