Labour analgesia. A risk-benefit analysis
Related Experiment Videos
1Department of Anesthesiology, Albany Medical College, New York, USA.

The pain associated with labour can be severe. The ideal labour analgesic does not exist and systemic opioids provide little relief. Nausea, vomiting and sedation are common adverse effects of systemic opioids. Paracervical block can relieve only the pain of the first stage of labour. The duration of analgesia obtained using paracervical block is limited and repeat blocks increase the risk of direct fetal injection. Epidural analgesia effectively relieves labour pain. The insertion of an epidural catheter can provide continuous analgesia throughout labour. In addition, the catheter can be used to provide surgical anaesthesia, should operative delivery be required. Epidural local anaesthetics commonly produce maternal hypotension and motor blockade. However, opioids potentiate the effect of epidural local anaesthetics. Thus, concomitant epidural opioid injection allows the use of lower concentrations of local anaesthetics, decreasing the frequency and severity of hypotension and motor blockade. Epidural analgesia has other, potentially catastrophic, adverse effects but, with safe clinical practice, these problems are extremely rare. Intrathecal injection of opioids or local anaesthetics also effective labour analgesia. However, no single intrathecal drug or drug combination reliably provides analgesia for the duration of labour. Many clinicians use both intrathecal and epidural analgesia as a combined spinal-epidural technique. This approach provides the rapid onset of intrathecal drugs and the flexibility of continuous epidural block. Fetal heart rate decelerations occasionally follow the use of any of the above labour analgesic techniques. Most studies of the aetiology of fetal heart rate decelerations have focused on factors unique to each analgesic technique. However, the similar timing and appearance of fetal bradycardia suggests a common cause. Induction of maternal analgesia may transiently alter the balance between factors encouraging and inhibiting uterine contraction. A temporary increase in the uterotonic effects of endogenous or exogenous oxytocin may then produce a tetanic uterine contraction with subsequent decrease fetal oxygen delivery and resultant fetal bradycardia. Regardless of aetiology, these bradycardias are transient and should not produce maternal or fetal morbidity. Much controversy surrounds the effects of analgesia, especially epidural block, on the course and outcome of labour. Various studies have reported that epidural analgesia slows labour, increases the incidence of malposition of the fetal head, increases the need for forceps delivery and increases the risk of caesarean delivery. Most of the studies reporting these effects are retrospective and nonrandomised. More careful studies suggest that specific anaesthetic techniques (i.e. local anaesthetic-opioid mixtures) or obstetrical management can limit or eliminate these 'risks' of epidural labour analgesia.
The pain associated with labour can be severe. The ideal labour analgesic does not exist and systemic opioids provide little relief. Nausea, vomiting and sedation are common adverse effects of systemic opioids. Paracervical block can relieve only the pain of the first stage of labour. The duration of analgesia obtained using paracervical block is limited and repeat blocks increase the risk of direct fetal injection. Epidural analgesia effectively relieves labour pain. The insertion of an epidural catheter can provide continuous analgesia throughout labour. In addition, the catheter can be used to provide surgical anaesthesia, should operative delivery be required. Epidural local anaesthetics commonly produce maternal hypotension and motor blockade. However, opioids potentiate the effect of epidural local anaesthetics. Thus, concomitant epidural opioid injection allows the use of lower concentrations of local anaesthetics, decreasing the frequency and severity of hypotension and motor blockade. Epidural analgesia has other, potentially catastrophic, adverse effects but, with safe clinical practice, these problems are extremely rare. Intrathecal injection of opioids or local anaesthetics also effective labour analgesia. However, no single intrathecal drug or drug combination reliably provides analgesia for the duration of labour. Many clinicians use both intrathecal and epidural analgesia as a combined spinal-epidural technique. This approach provides the rapid onset of intrathecal drugs and the flexibility of continuous epidural block. Fetal heart rate decelerations occasionally follow the use of any of the above labour analgesic techniques. Most studies of the aetiology of fetal heart rate decelerations have focused on factors unique to each analgesic technique. However, the similar timing and appearance of fetal bradycardia suggests a common cause. Induction of maternal analgesia may transiently alter the balance between factors encouraging and inhibiting uterine contraction. A temporary increase in the uterotonic effects of endogenous or exogenous oxytocin may then produce a tetanic uterine contraction with subsequent decrease fetal oxygen delivery and resultant fetal bradycardia. Regardless of aetiology, these bradycardias are transient and should not produce maternal or fetal morbidity. Much controversy surrounds the effects of analgesia, especially epidural block, on the course and outcome of labour. Various studies have reported that epidural analgesia slows labour, increases the incidence of malposition of the fetal head, increases the need for forceps delivery and increases the risk of caesarean delivery. Most of the studies reporting these effects are retrospective and nonrandomised. More careful studies suggest that specific anaesthetic techniques (i.e. local anaesthetic-opioid mixtures) or obstetrical management can limit or eliminate these 'risks' of epidural labour analgesia.
Related Concept Videos
 01:29
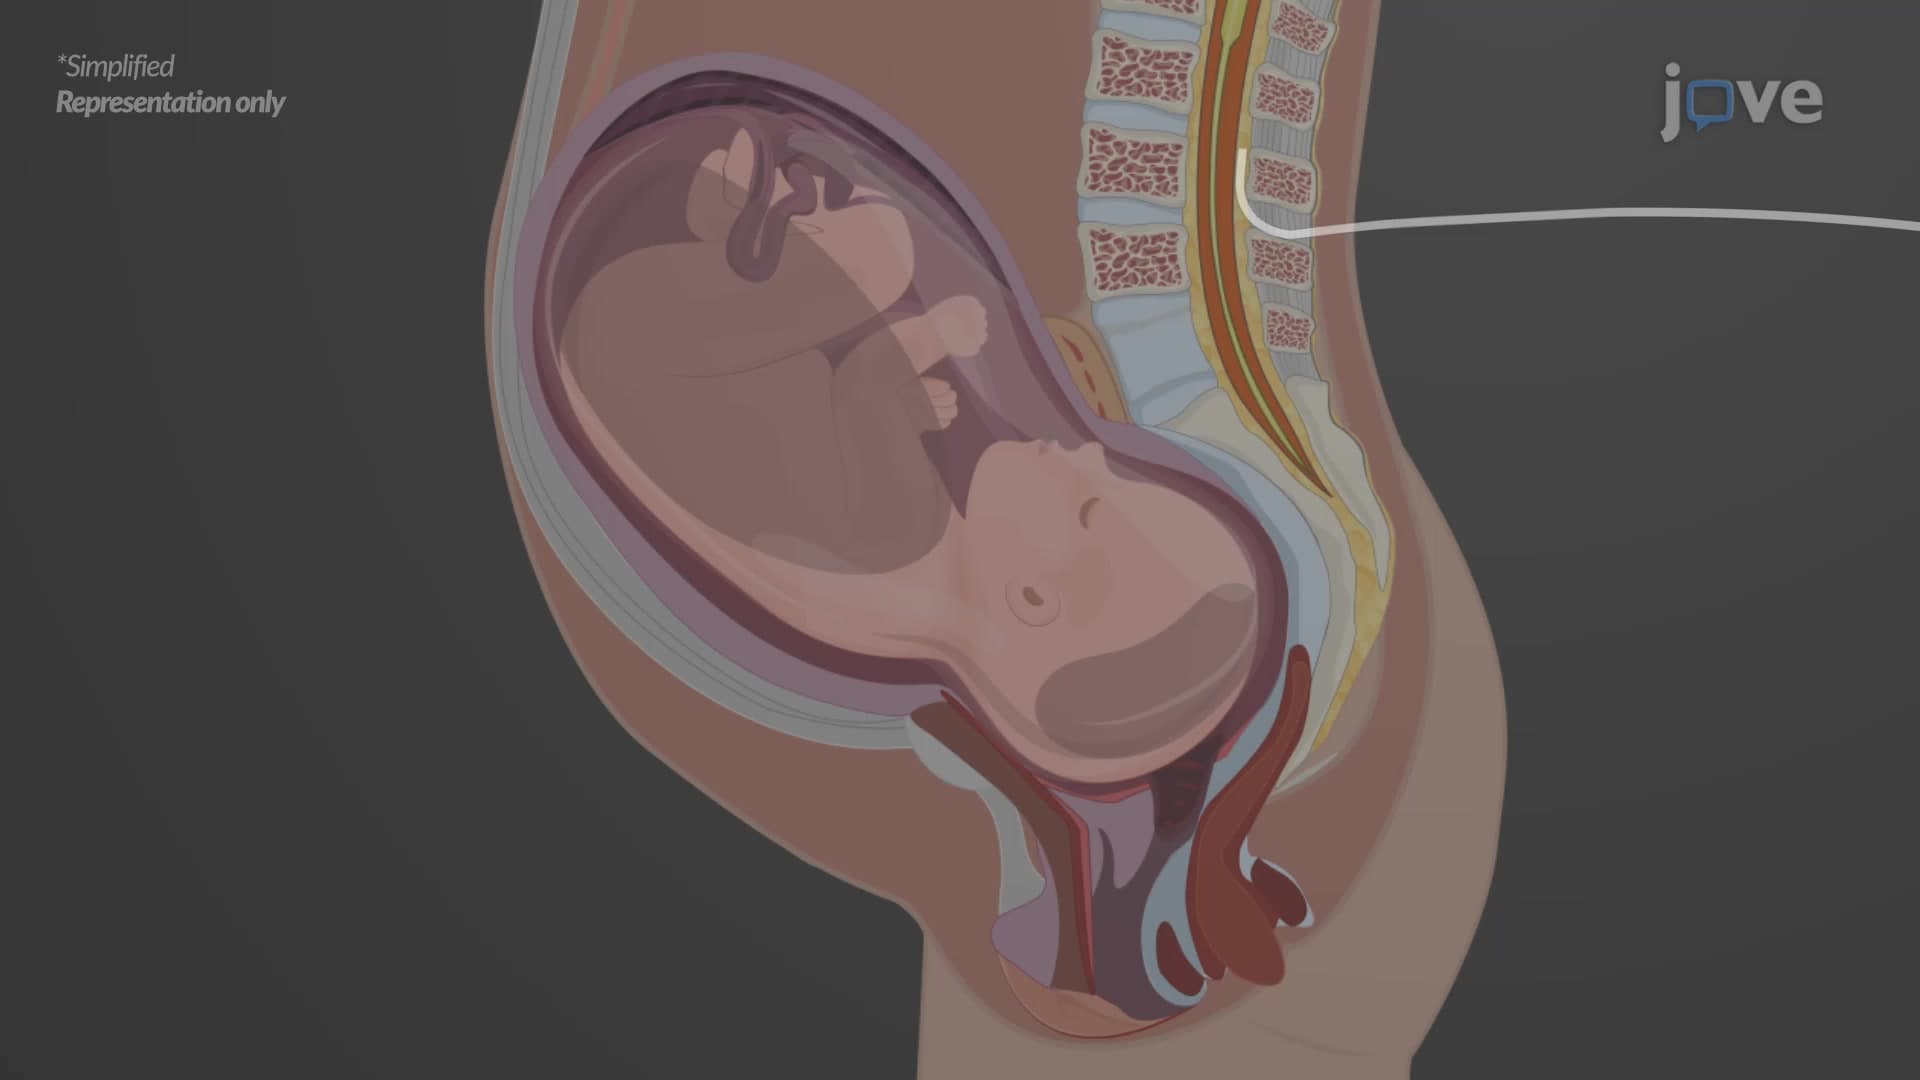
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:25
Analgesia and Pain Management
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:13
Local Anesthetics: Pharmacokinetics