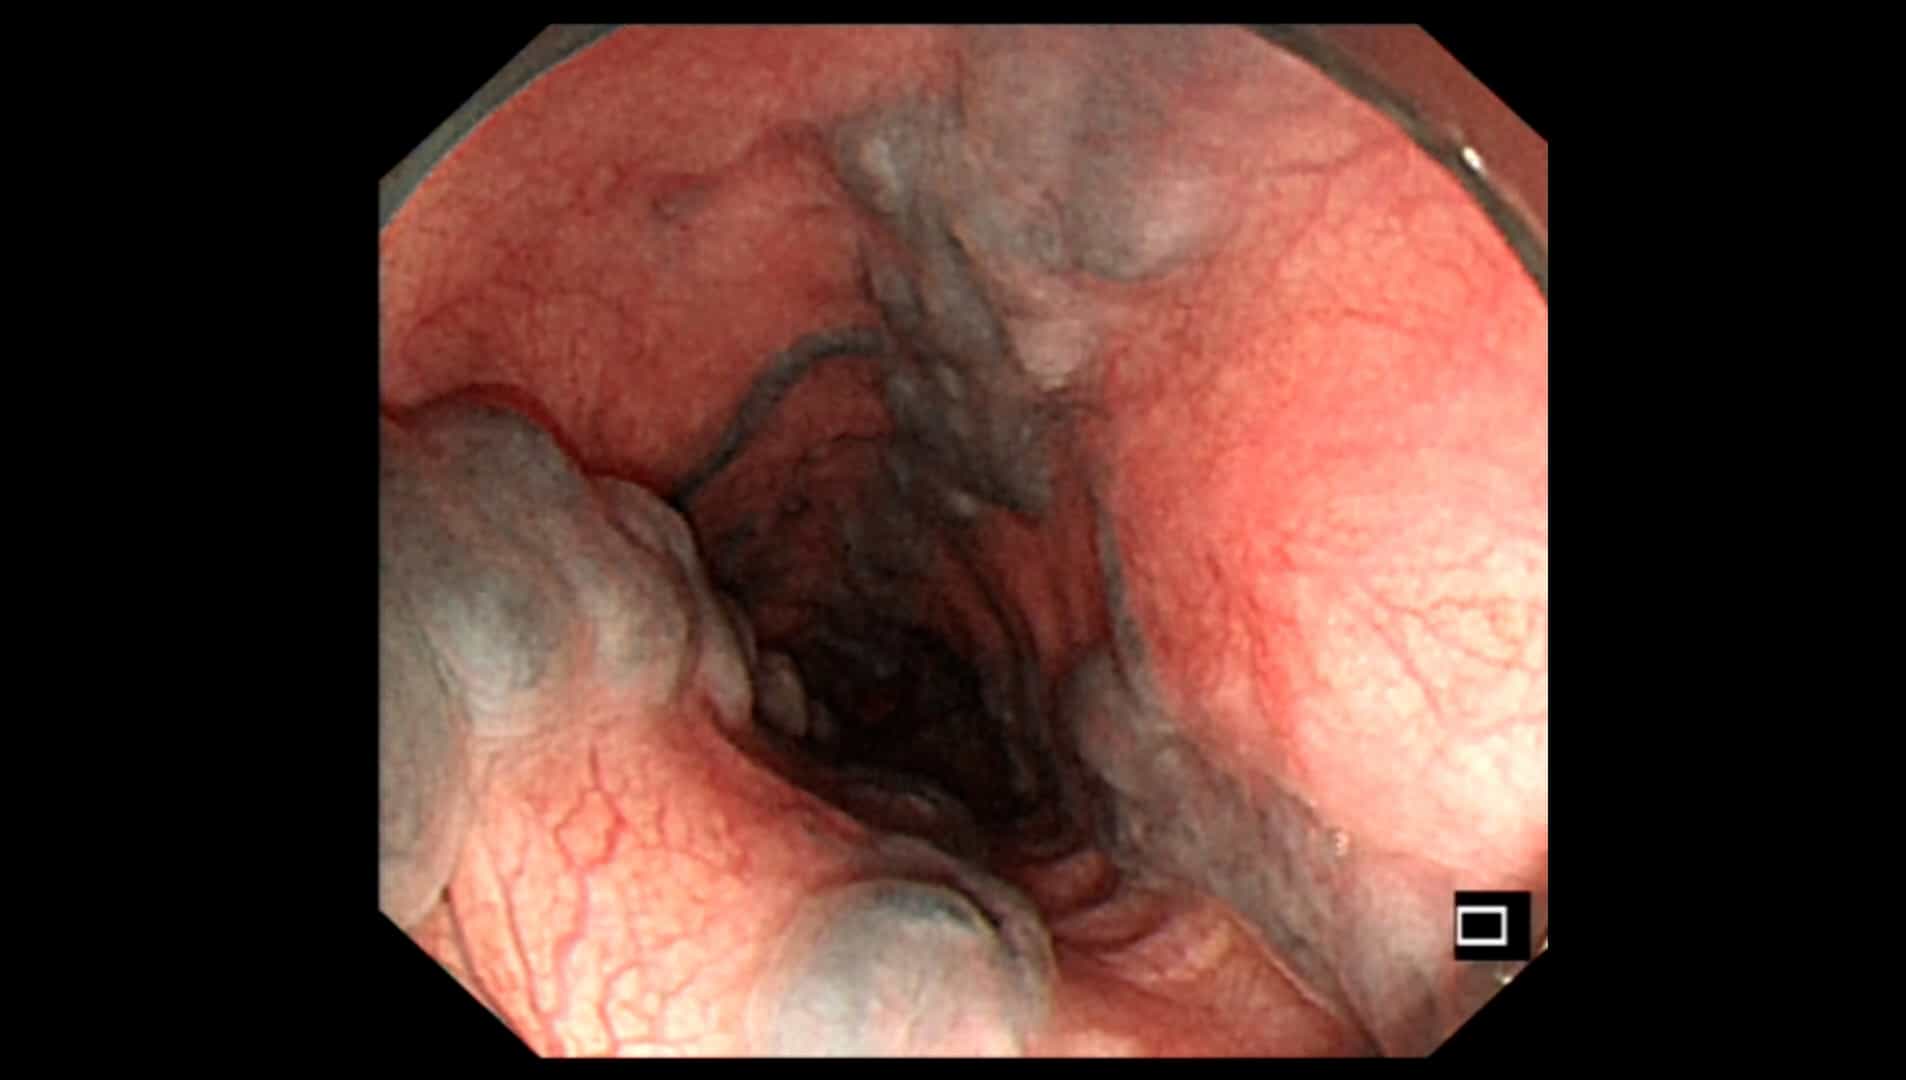
Control of colonic variceal haemorrhage with a somatostatin analogue

B J Chakravarty1, J W Riley

  • 1Department of Gastroenterology, Royal North Shore Hospital, Sydney, New South Wales, Australia.

Related Concept Videos

Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents01:20

Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents

The gastric mucosa produces prostaglandins E2 (PGE2) and prostacyclin (PGI2), crucial in maintaining gastric health. They exert cytoprotective effects, including increasing bicarbonate secretion, releasing protective mucin, reducing gastric acid output, and preventing harmful vasoconstriction. These effects are mediated through various receptors, such as EP1, EP2, EP3, and EP4.
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
Esophageal Varices-I: Introduction01:24

Esophageal Varices-I: Introduction

Esophageal varices are dilated, tortuous veins which are found mainly in the submucosa of the lower esophagus but which may also appear higher up or extend into the stomach. They develop due to increased pressure in the portal venous system, often as a result of liver cirrhosis. This condition scars and damages the liver, impeding normal blood flow through the portal vein. To compensate, blood seeks alternative pathways, forming fragile new vessels (varices) in the esophagus and stomach. These...
Esophageal Varices-II: Clinical Features and Management01:28

Esophageal Varices-II: Clinical Features and Management

Esophageal varices often manifest as gastrointestinal bleeding episodes, presenting symptoms like hematemesis (vomiting of blood), hematochezia (passing fresh blood via the rectum), and melena (black, tarry stools). Other signs can include weight loss, anorexia, abdominal discomfort, jaundice, pruritus, altered mental status, and muscle cramps.
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
Peptic Ulcer Disease IV: Management01:26

Peptic Ulcer Disease IV: Management

Medical treatment strategies for peptic ulcers encompass various methods. The primary goal of treatment is to diminish gastric acidity and strengthen mucosal defense mechanisms.
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
Inflammatory Bowel Disease IV: Pharmacological Management01:29

Inflammatory Bowel Disease IV: Pharmacological Management

Upon diagnosis, managing Inflammatory Bowel Disease (IBD) involves addressing several crucial aspects. The primary goals include resting the bowel, correcting malnutrition, and providing symptomatic relief. Resting the bowel may consist of medications to reduce inflammation and promote healing. Correcting malnutrition is essential, often requiring dietary adjustments and nutritional supplements. Symptomatic relief aims to ease pain, diarrhea, and other discomforts in IBD.
Pharmacologic...
Inflammatory Bowel Disease V: Surgical Management01:21

Inflammatory Bowel Disease V: Surgical Management

Surgical interventions for inflammatory bowel disease (IBD), which includes ulcerative colitis and Crohn's disease, are essential in managing symptoms and addressing complications. The selection of surgical procedures is contingent upon the specific conditions and complications that stem from these illnesses.
Here are some common surgical interventions for IBD: